💊 Which statin should you choose?
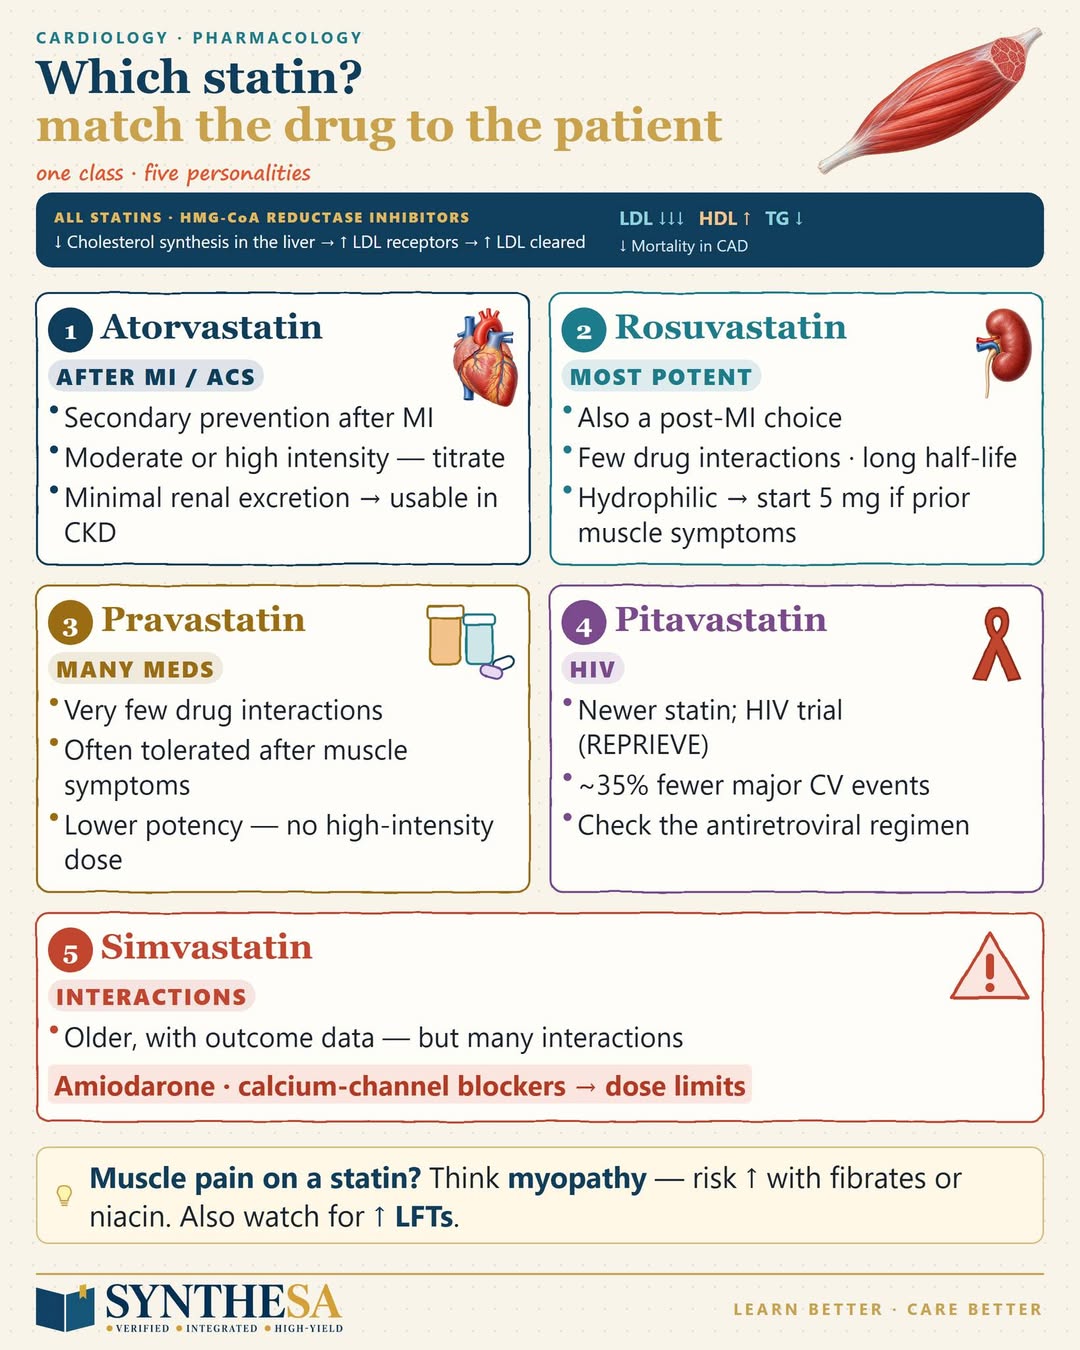
All statins block HMG-CoA reductase → the liver makes less cholesterol → more LDL receptors → more LDL cleared. LDL ↓↓↓ · HDL ↑ · TG ↓ — and they lower mortality in CAD.
The choice comes down to the patient 👇
🫀 ATORVASTATIN — after MI / ACS
Moderate or high intensity, easy to titrate. Minimal renal excretion, so it's usable in CKD.
💧 ROSUVASTATIN — the most potent
Also a post-MI choice. Few drug interactions, long half-life. Hydrophilic, so it's often better tolerated after muscle symptoms (not guaranteed) — start low, at 5 mg.
💊 PRAVASTATIN — many medications
Very few drug interactions and often tolerated after muscle symptoms. Lower potency: no high-intensity dose.
🎗️ PITAVASTATIN — HIV
In the REPRIEVE trial it cut major cardiovascular events by about 35% in adults with HIV. Always check the antiretroviral regimen.
⚠️ SIMVASTATIN — interactions
Older, with outcome data, but many interactions: amiodarone and some calcium-channel blockers need dose limits.
🧠 Exam point: muscle pain on a statin? Think myopathy — the risk rises with fibrates or niacin. Also watch for ↑ LFTs.
🔖 Save this for your next pharmacology review.
Synthesa — Learn better. Care better.
#Synthesa #statins #pharmacology #cardiologyeducation #USMLE #MedEd