Expert opinion is shifting towards LDL of below 30 as optimal, while this hasn't been definitively proven in clinical trials.
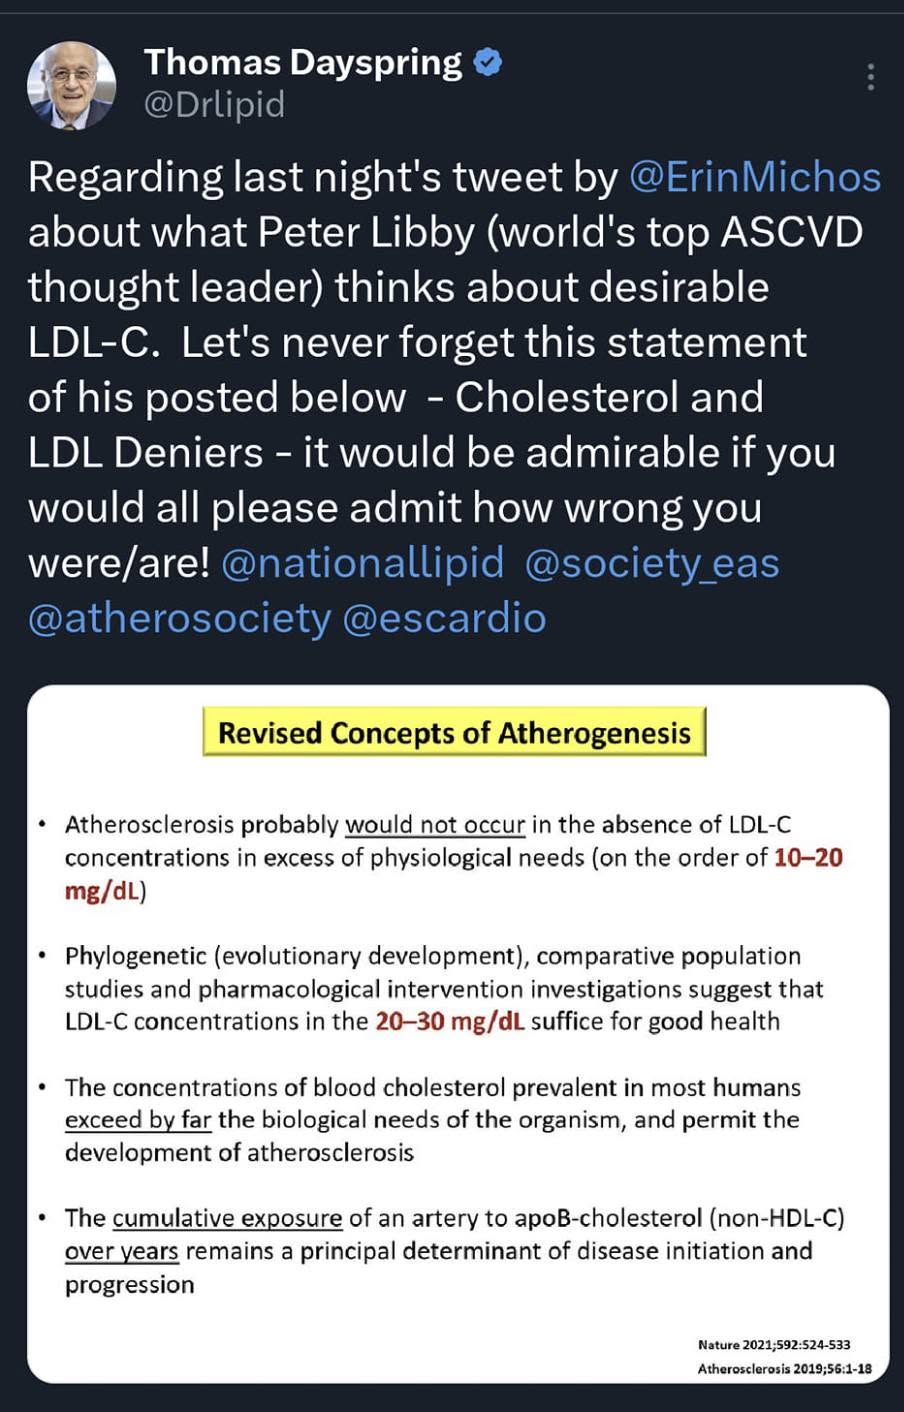
Gokhan notes that expert opinion increasingly favors an LDL below 30 as optimal, while this has not been definitively proven in clinical trials.
Expert opinion is shifting towards LDL of below 30 as optimal, while this hasn't been definitively proven in clinical trials.
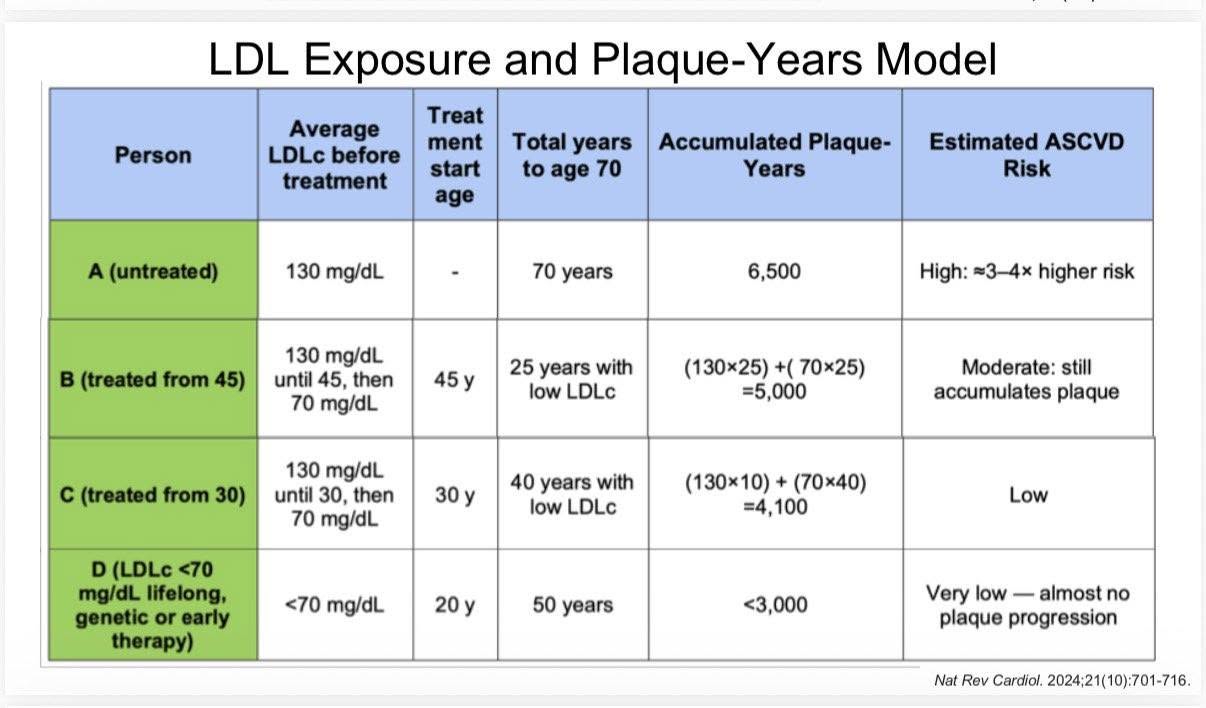
Reposts an infographic arguing that LDL-C should be seen as plaque-years: every year of elevated LDL adds arterial burden that cannot be undone, so starting treatment at 30 beats starting at 45, and early intervention may matter more than drug strength.
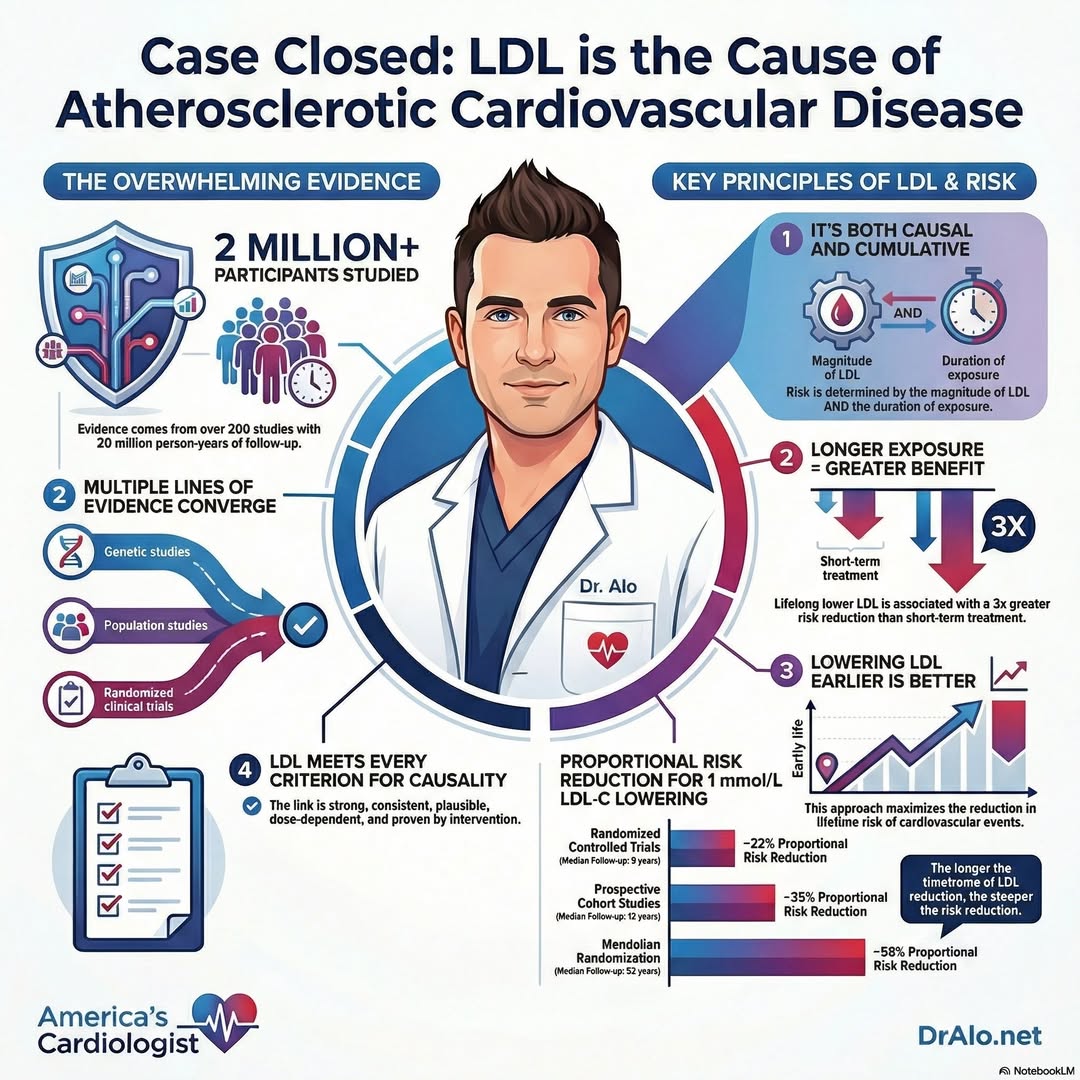
Shares a blog post from Dr Alo about LDL causing heart disease, with no further description.
Summarises a Circulation analysis of 5,200+ patients with prior ischemic stroke from FOURIER and its extension: lower achieved LDL-C meant fewer events. Versus LDL >=70 mg/dL, below 40 mg/dL had ~31% fewer major CV events and 27% fewer recurrent strokes, and even <20 mg/dL showed no excess hemorrhagic stroke.
Explains that cholesterol is essential, but too many ApoB-containing particles like LDL get trapped in artery walls and drive plaque, and high circulating cholesterol may push bone-marrow stem cells toward inflammatory myeloid lineages. Keeping ApoB/LDL low is described as a powerful lever for arterial health.
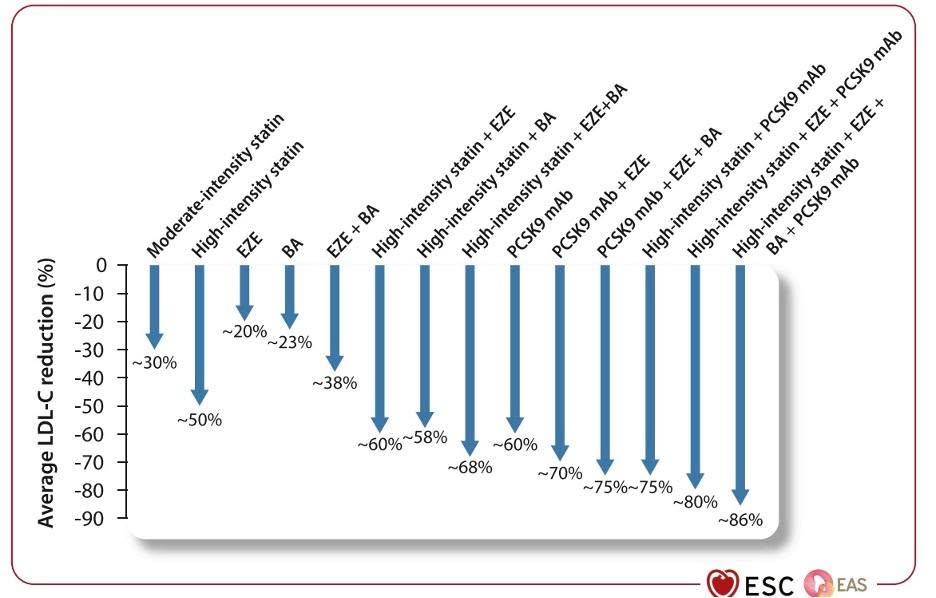
Shares an infographic giving a rough idea of LDL reduction from combining lipid-lowering drugs. The image's numbers are not in the post text.
Summarises a July 2025 review: guidelines now target LDL-C <55 mg/dL (<40 after a recurrent event), PCSK9 inhibitors add 59-62% LDL reduction, and evidence (FOURIER, CTT meta-analysis, PCSK9 genetics) supports benefit to very low levels. It says safety concerns such as hemorrhagic stroke, cognitive decline (EBBINGHAUS) and hormone disruption are unsupported, while fewer than one in four high-risk patients reach target.