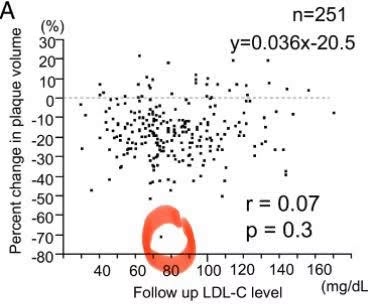
Every 1% reversal of plaque (PAV) is associated with a 20% reduction in major adverse cardiac events (MACE).
So even small reversals are a big deal.
Note that PAV is a measure of what percentage of the total volume of your vasculature is composed of plaque. A level of PAV of 15% is considered severe plaque. Just reducing this by 1% to a PAV of 14% is a big deal in terms of reducing risk.
The effects of lipid-lowering therapy on coronary plaque regression (2021)
The meta-analysis by Li et al. (2021) included 31 studies with 4,997 patients to assess if lipid lowering therapy causes coronary plaque regression.
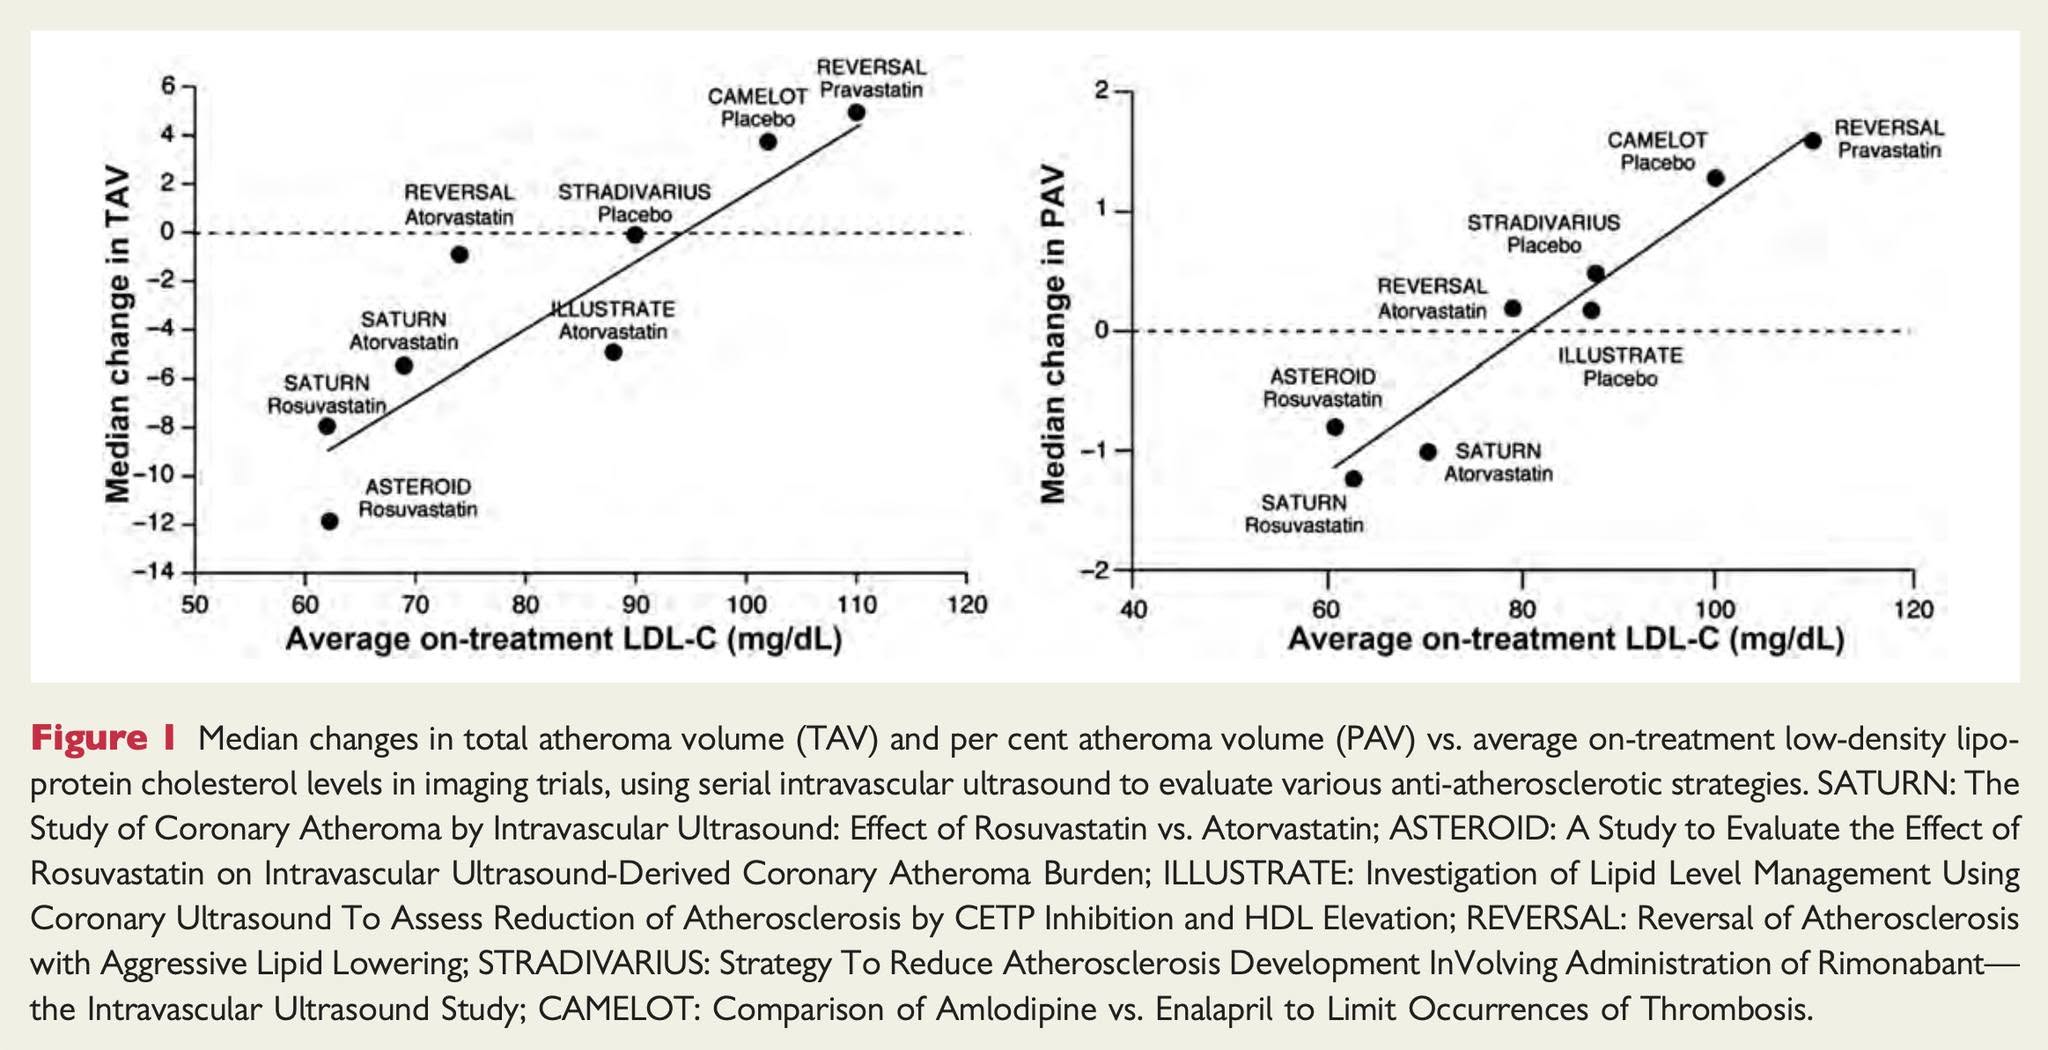
Intravascular ultrasound (IVUS) measured changes in total atheroma volume (TAV) and percent atheroma volume (PAV) before and after treatment. Across all studies, patients had significantly lower TAV and PAV on average, though individual responses varied.
- Targeting LDL <80 mg/dL and HDL >45 mg/dL was associated with maximal coronary plaque regression.
- More intensive lipid lowering than standard guidelines may be warranted.
- Every 1% reduction in PAV → 20% lower risk of major adverse cardiac events.
- Regressing plaque appears protective against future cardiovascular events.
Factors underlying regression of coronary atheroma with potent statin therapy (2014)
Puri et al. (2013) analyzed data from the SATURN trial to characterize factors associated with regression of different measures of coronary atherosclerosis volume (TAV and PAV) in patients treated with high-intensity statin therapy. The SATURN trial compared maximal doses of rosuvastatin (40mg) and atorvastatin (80mg) over 2 years in over 1000 patients using serial intravascular ultrasound (IVUS).
The main conclusions were:
- Both rosuvastatin and atorvastatin treatment led to significant reductions in TAV and PAV over 2 years. However, rosuvastatin treatment resulted in significantly greater reductions in TAV compared to atorvastatin (-26.4 vs -24.4 mm3, p=0.01), but similar reductions in PAV (-1.22 vs -0.99%, p=0.17).
- A greater percentage of patients treated with rosuvastatin showed TAV regression compared to atorvastatin (71.3% vs 64.7%, p=0.02). There was no difference between groups in percentage showing PAV regression.
- Higher baseline levels of TAV and PAV were consistently and independently associated with greater subsequent TAV and PAV regression with high-intensity statin treatment, regardless of whether TAV or PAV was assessed. Each standard deviation higher baseline TAV was associated with 0.25 standard deviations greater subsequent TAV regression (p<0.001). Similarly, each standard deviation higher baseline PAV was associated with 0.23 standard deviations greater PAV regression (p<0.001).
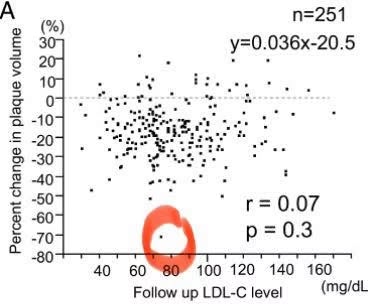
- Higher baseline LDL-C levels and average on-treatment non-HDL cholesterol levels were independently associated with atherosclerosis progression, measured by both TAV and PAV.
- Rosuvastatin treatment showed greater TAV regression compared to atorvastatin in patients with diabetes (-28.6 vs -20.9 mm3, p=0.01), with a significant treatment-diabetes interaction (p=0.05). This suggests rosuvastatin was more effective than atorvastatin in diabetics.
- Women treated with rosuvastatin showed greater PAV regression than women treated with atorvastatin (-1.76% vs -0.71%, p=0.01). There was also a significant treatment-sex interaction for PAV changes (p=0.03), suggesting a greater treatment effect for rosuvastatin vs atorvastatin in women.
- Patients with higher baseline LDL-C and HDL-C levels showed significantly greater PAV regression if treated with rosuvastatin compared to atorvastatin (significant interactions).
In summary, high-intensity statin therapy induces coronary atherosclerosis regression, particularly in higher risk patients and those with greater baseline disease burden. While rosuvastatin and atorvastatin had similar effects on PAV, rosuvastatin showed greater efficacy in reducing TAV. Significant differences in treatment effects between groups were also evident for specific higher risk patient subgroups. The findings highlight the variable factors influencing atherosclerotic plaque volume and arterial remodeling in response to maximal statin therapy.