The Japan-ACS trial was one of the most remarkable prevention trials conducted in cardiology:
Paper · Journal of the American College of Cardiology · 2009Effect of Intensive Statin Therapy on Regression of Coronary Atherosclerosis in Patients With Acute Coronary Syndromejacc.orgIt found that modest statin therapy significantly reversed arterial plaque, in patients who experienced acute coronary syndrome (ACS).
Acute coronary syndrome (ACS) occurs when major arterial blockages suddenly begin to starve the heart of oxygen: What Is Acute Coronary Syndrome? (Cleveland Clinic)
Over 300 patients at 33 different medical centers in Japan were randomized to receive either 4 mg/day of pitavastatin or 20 mg/day of atorvastatin.
After 8 to 12 months, both groups experienced a similar major regression in non-culprit coronary plaque volume, with a mean percentage change of -16.9% for 4mg pitavastatin and -18.1% for 20mg atorvastatin.
(“Non-culprit” means excluding the acute blockages that actually caused the ACS. The acute blockages— the “culprits”— contain thrombus and vasospasm which cannot be accurately differentiated from true plaque, so they need to be excluded if the goal is to measure true plaque reversal.)
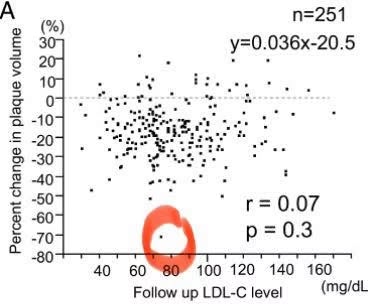
Patients one standard deviation above the mean experienced regressions of 30.8% and 32.3%, on pitavastatin and atorvastatin respectively.
One patient experienced a regression greater than 70% !
Average LDL decreased from 130-135mg/dL to 80-85mg/dL in both statin groups. As the results show, this was enough to cause major plaque reversal in blockages in both groups.
The measurements were all done with IVUS, which is the gold standard for imaging plaque inside arteries. An IVUS camera was directly inserted into arteries to capture before-and-after images of the blockages.
This trial is one of the major reasons why statin therapy remains standard of care in patients with acute coronary syndrome due to significant blockages of arteries.
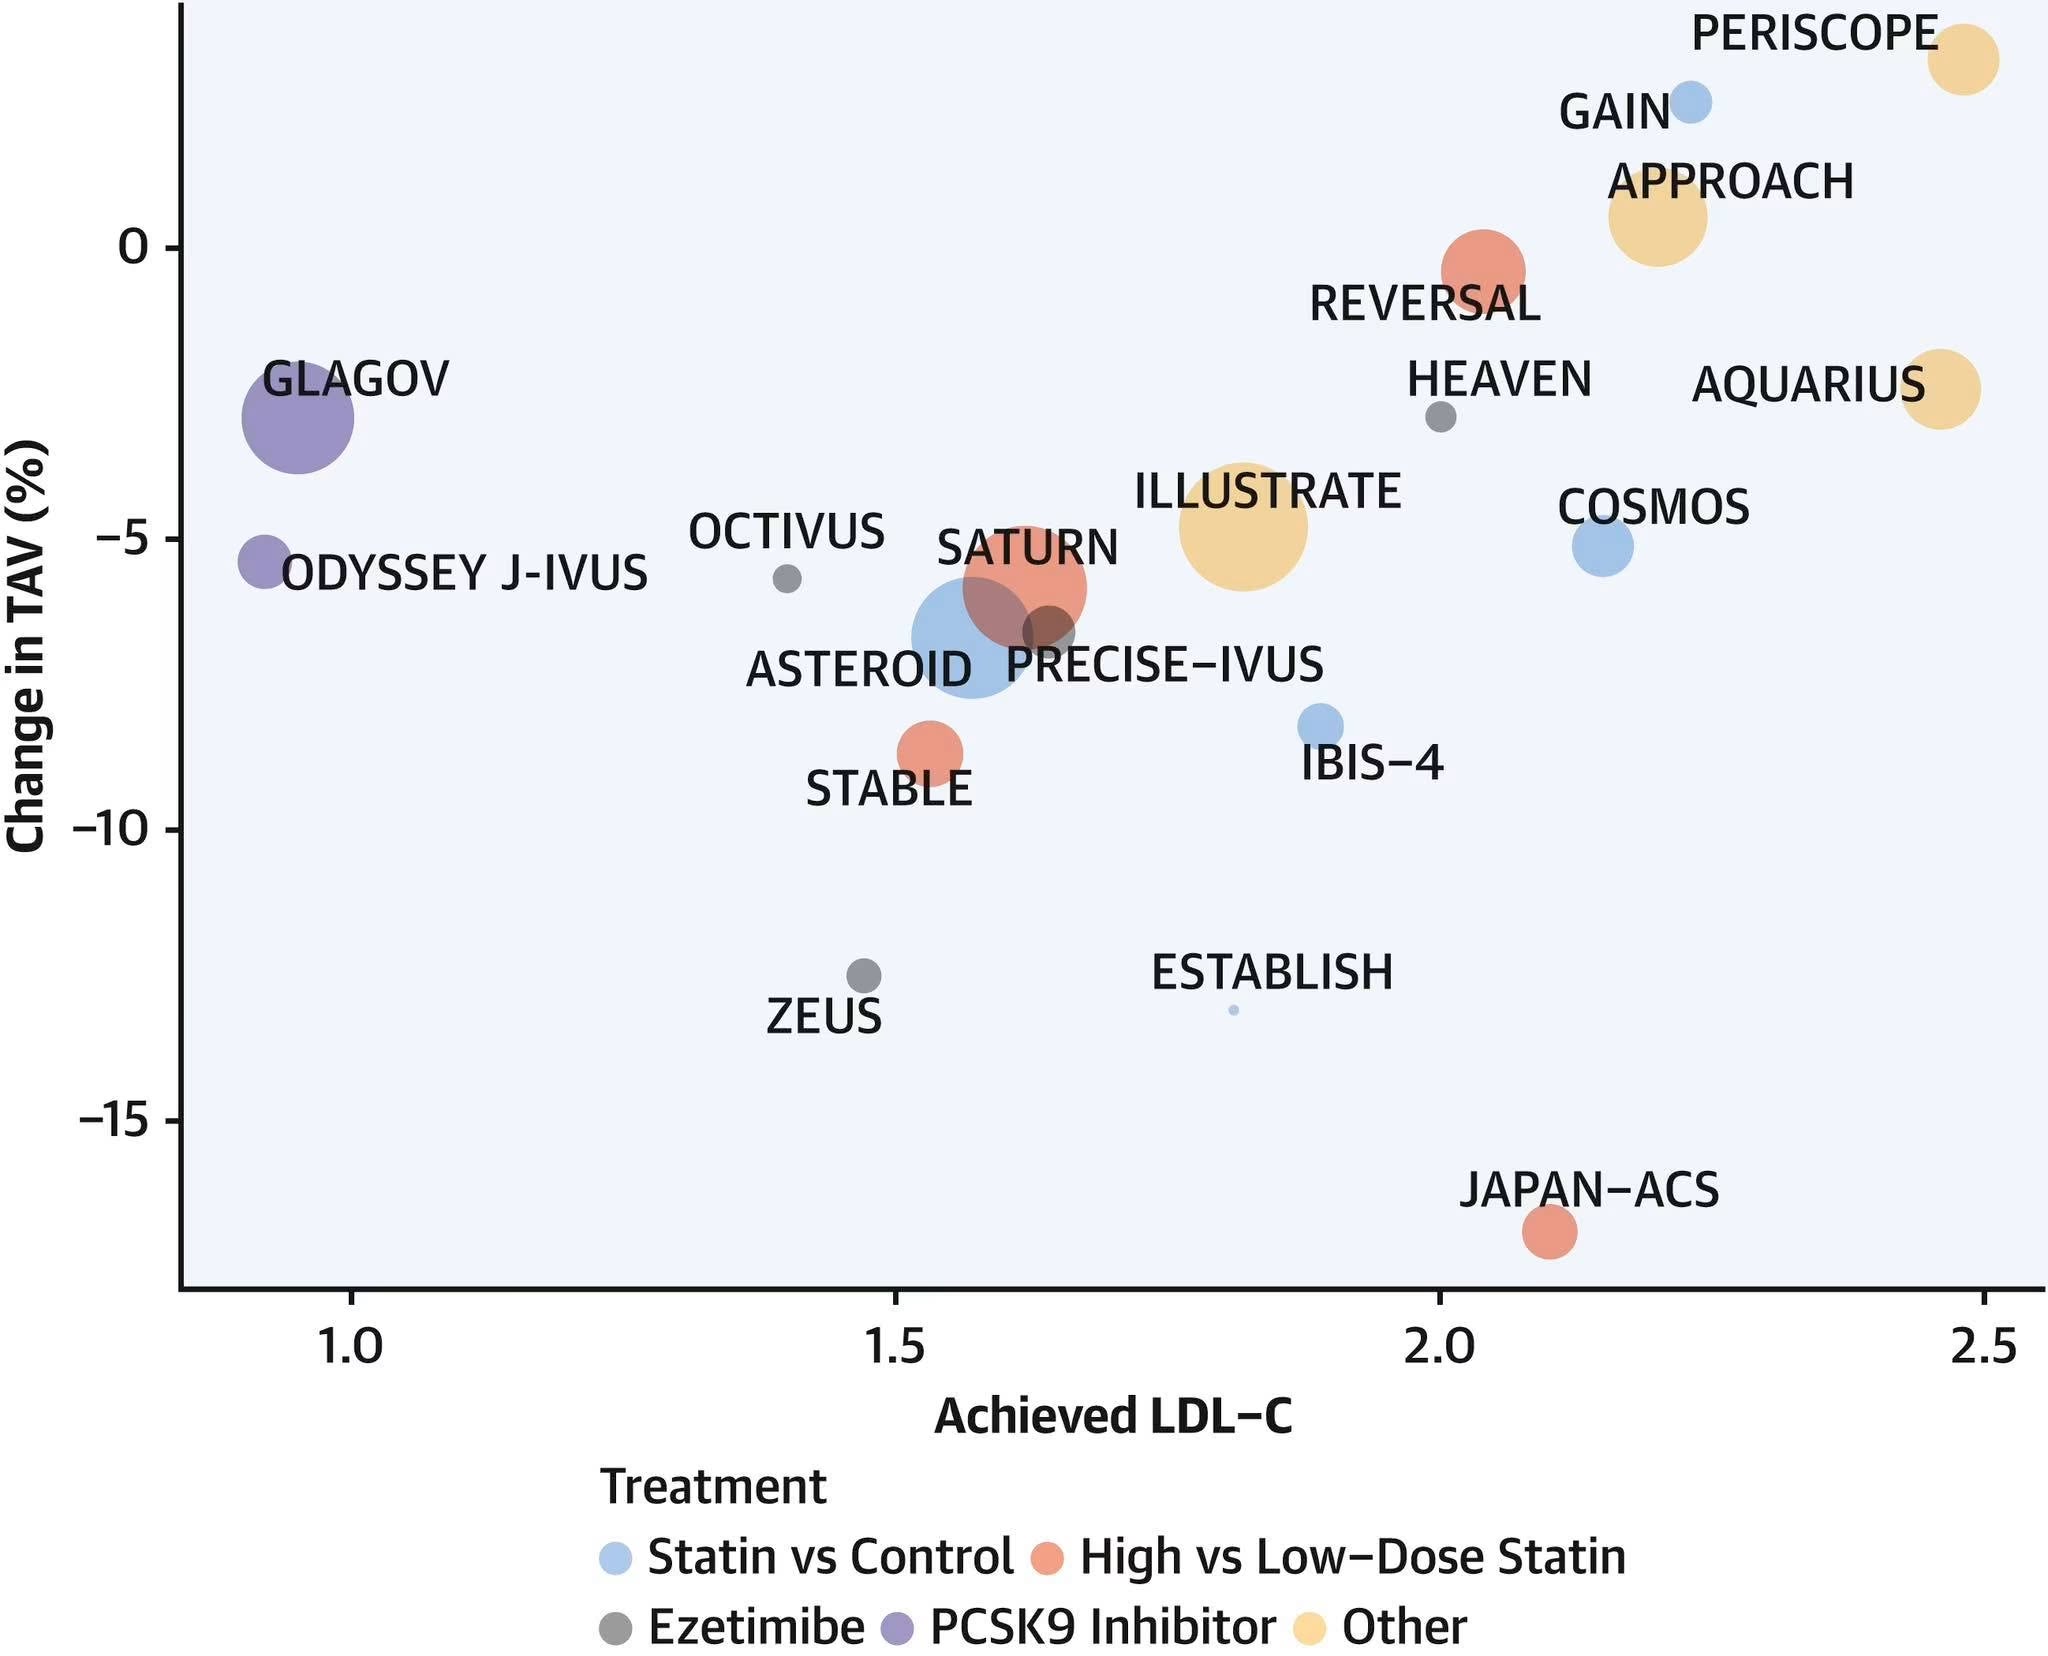
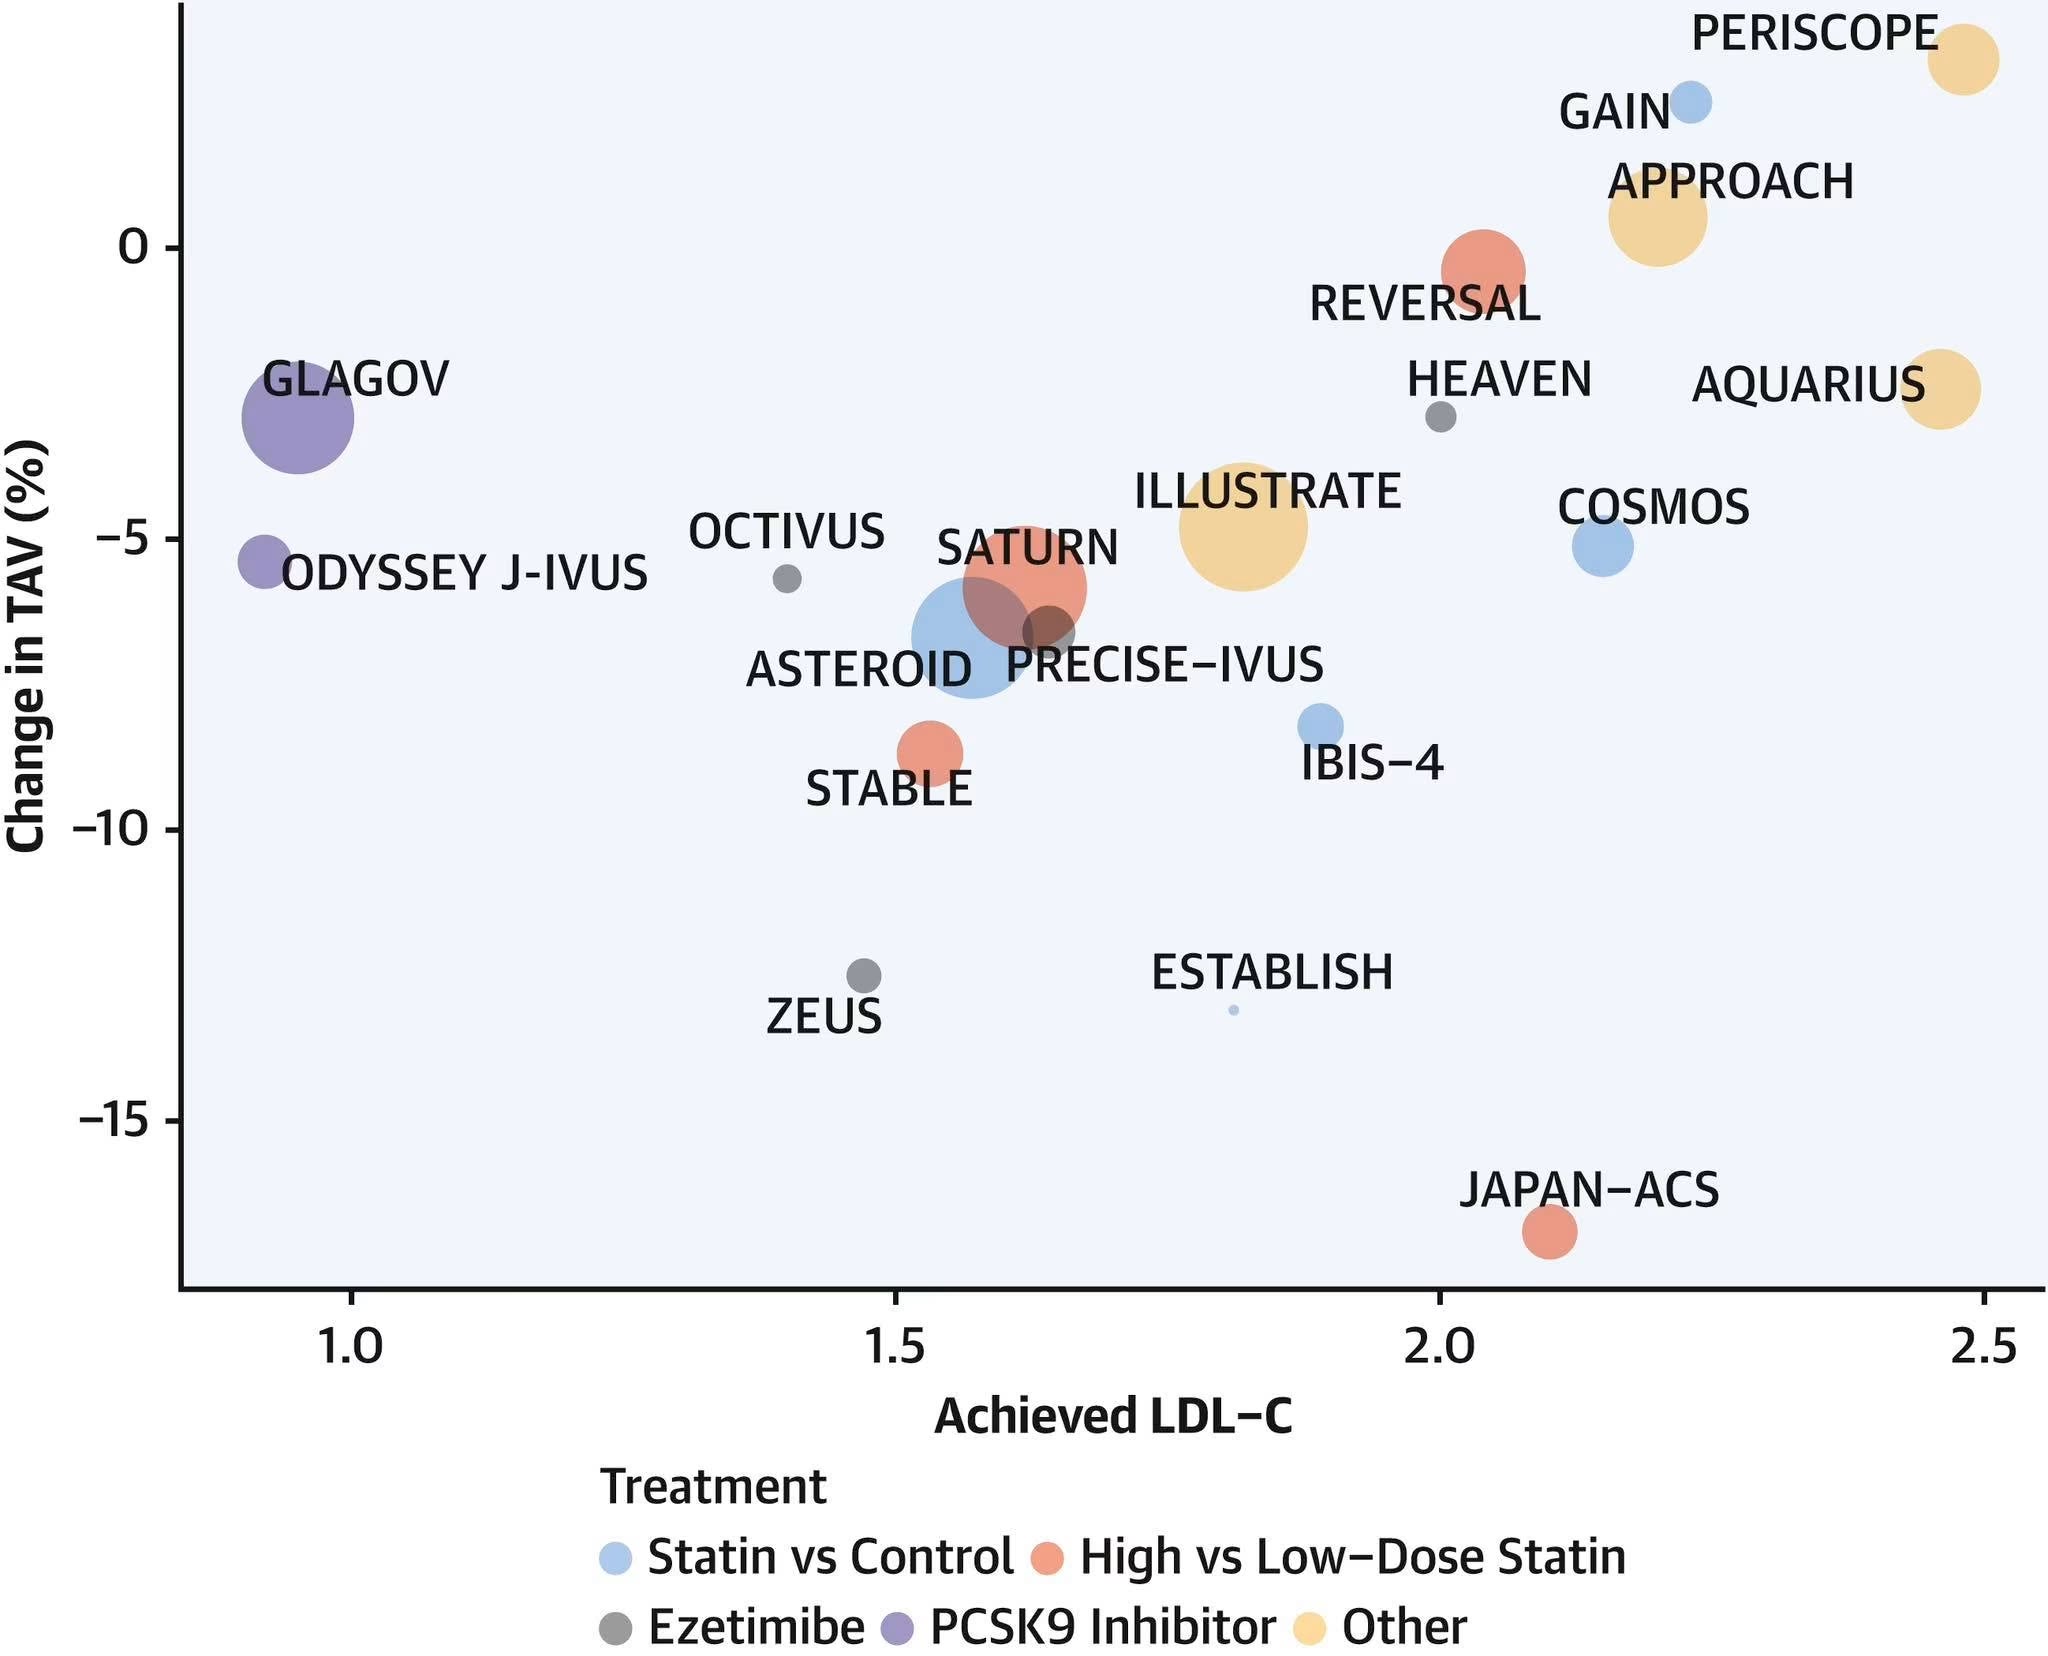
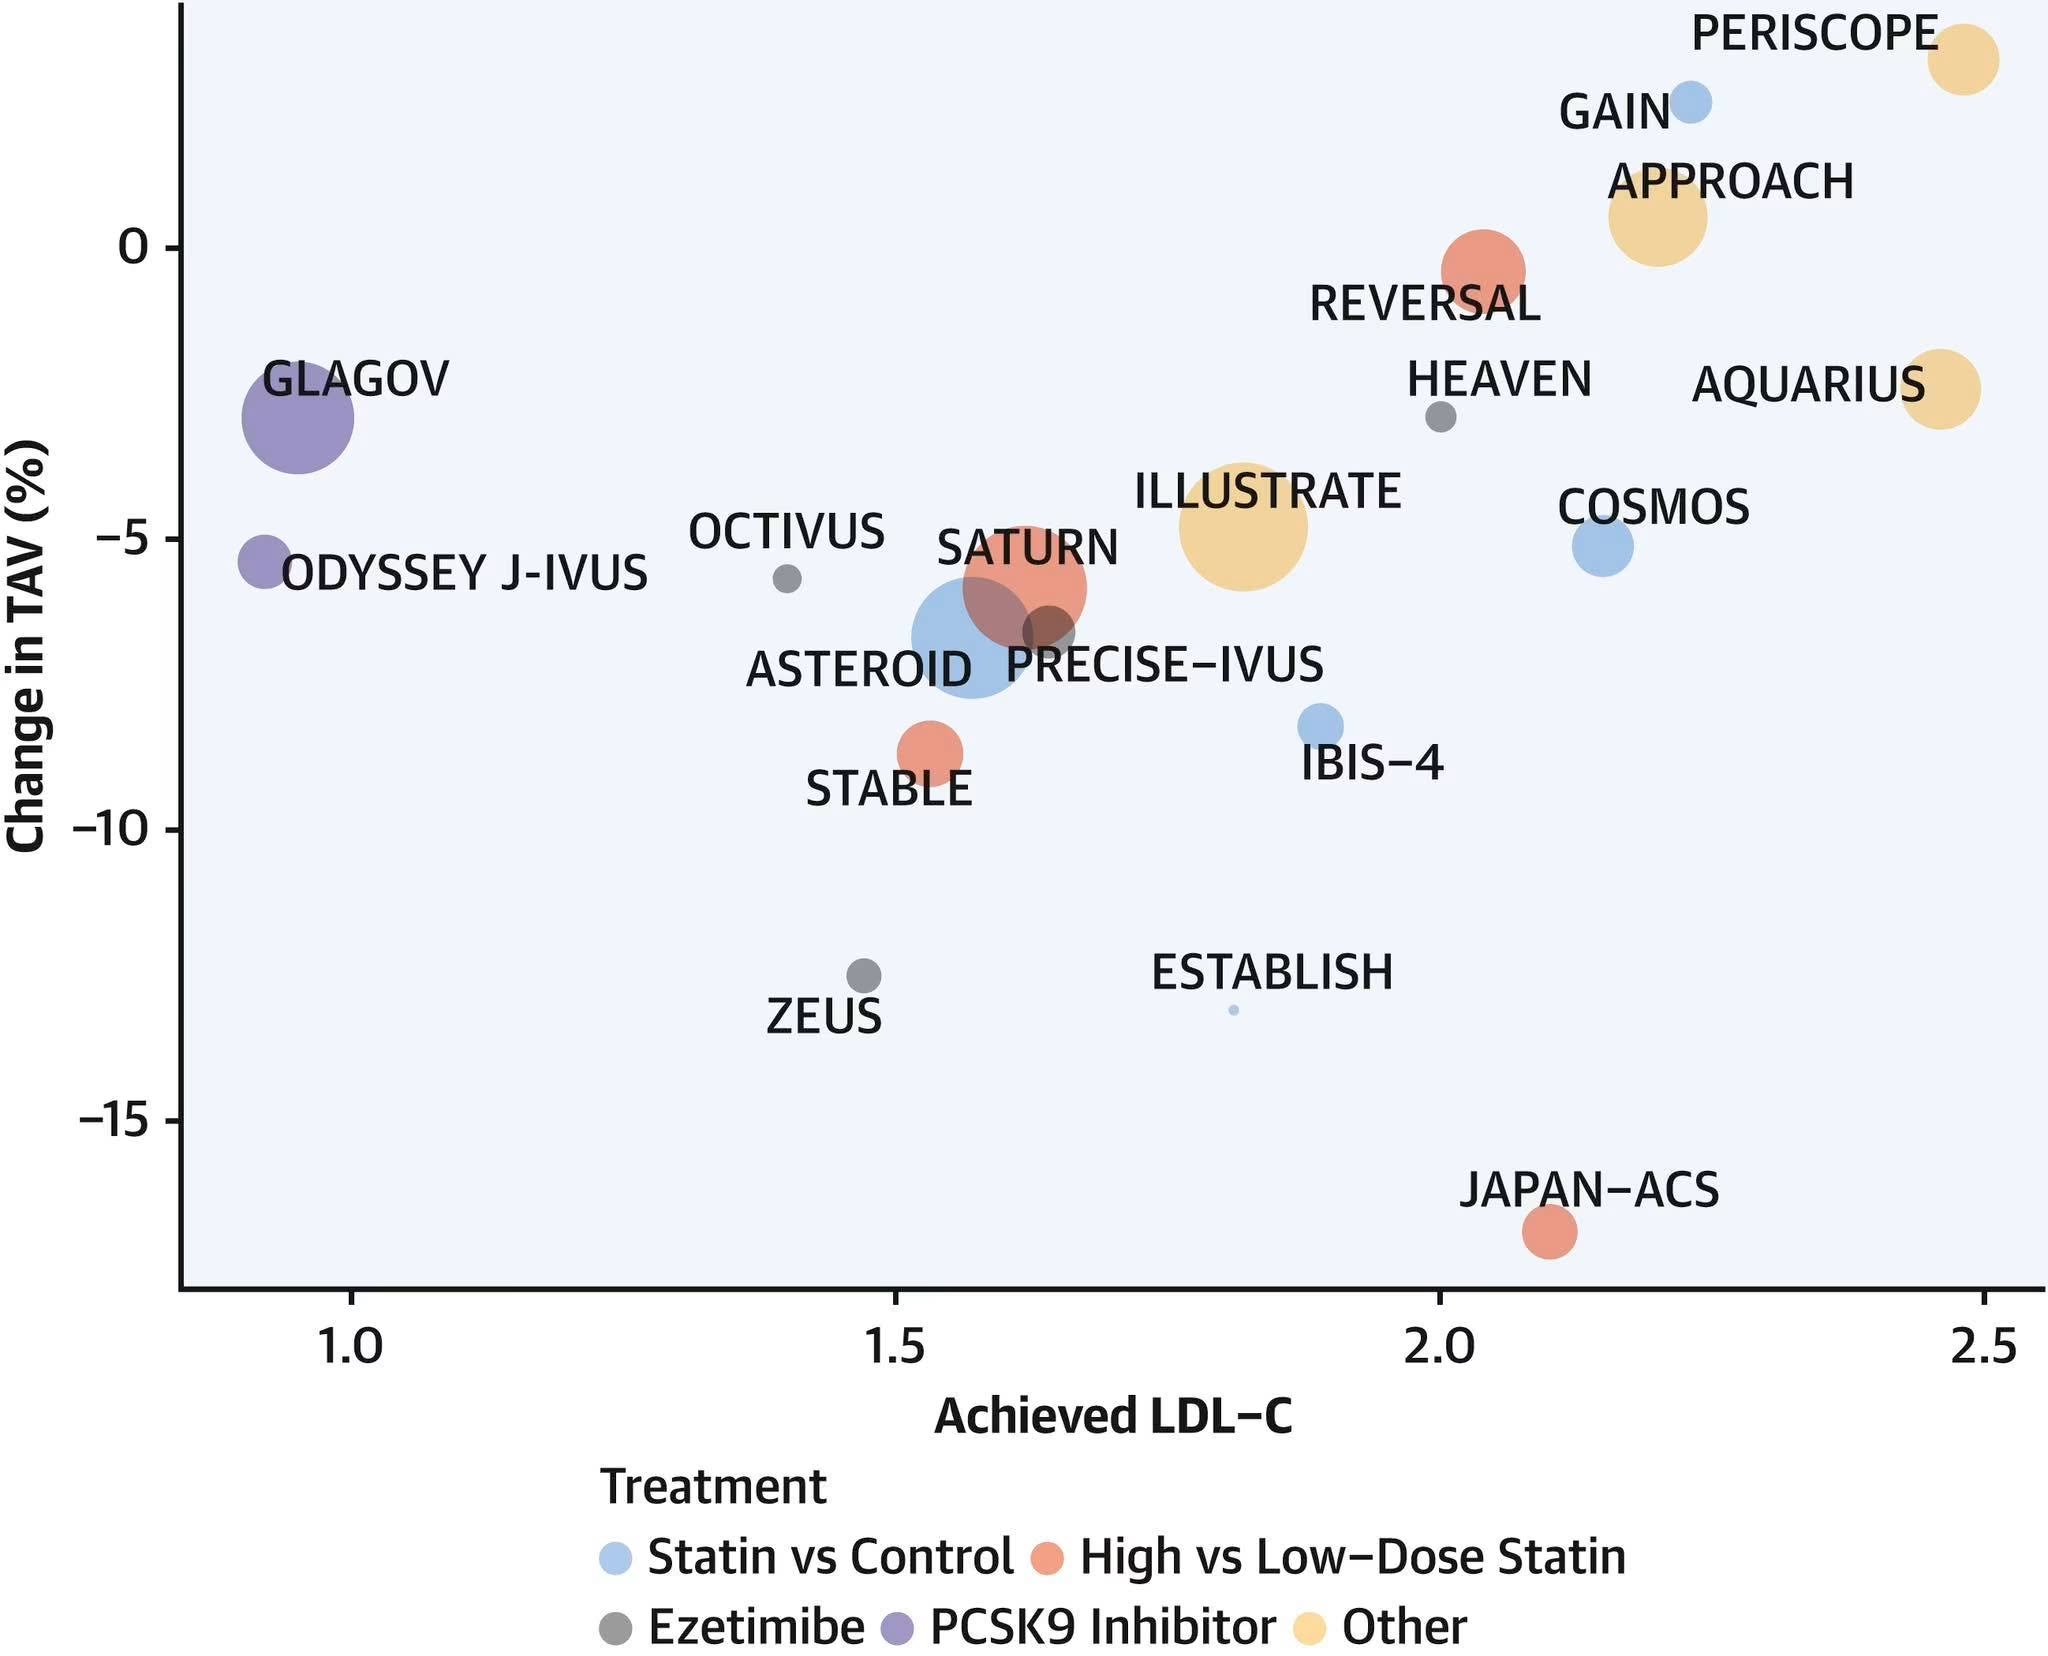
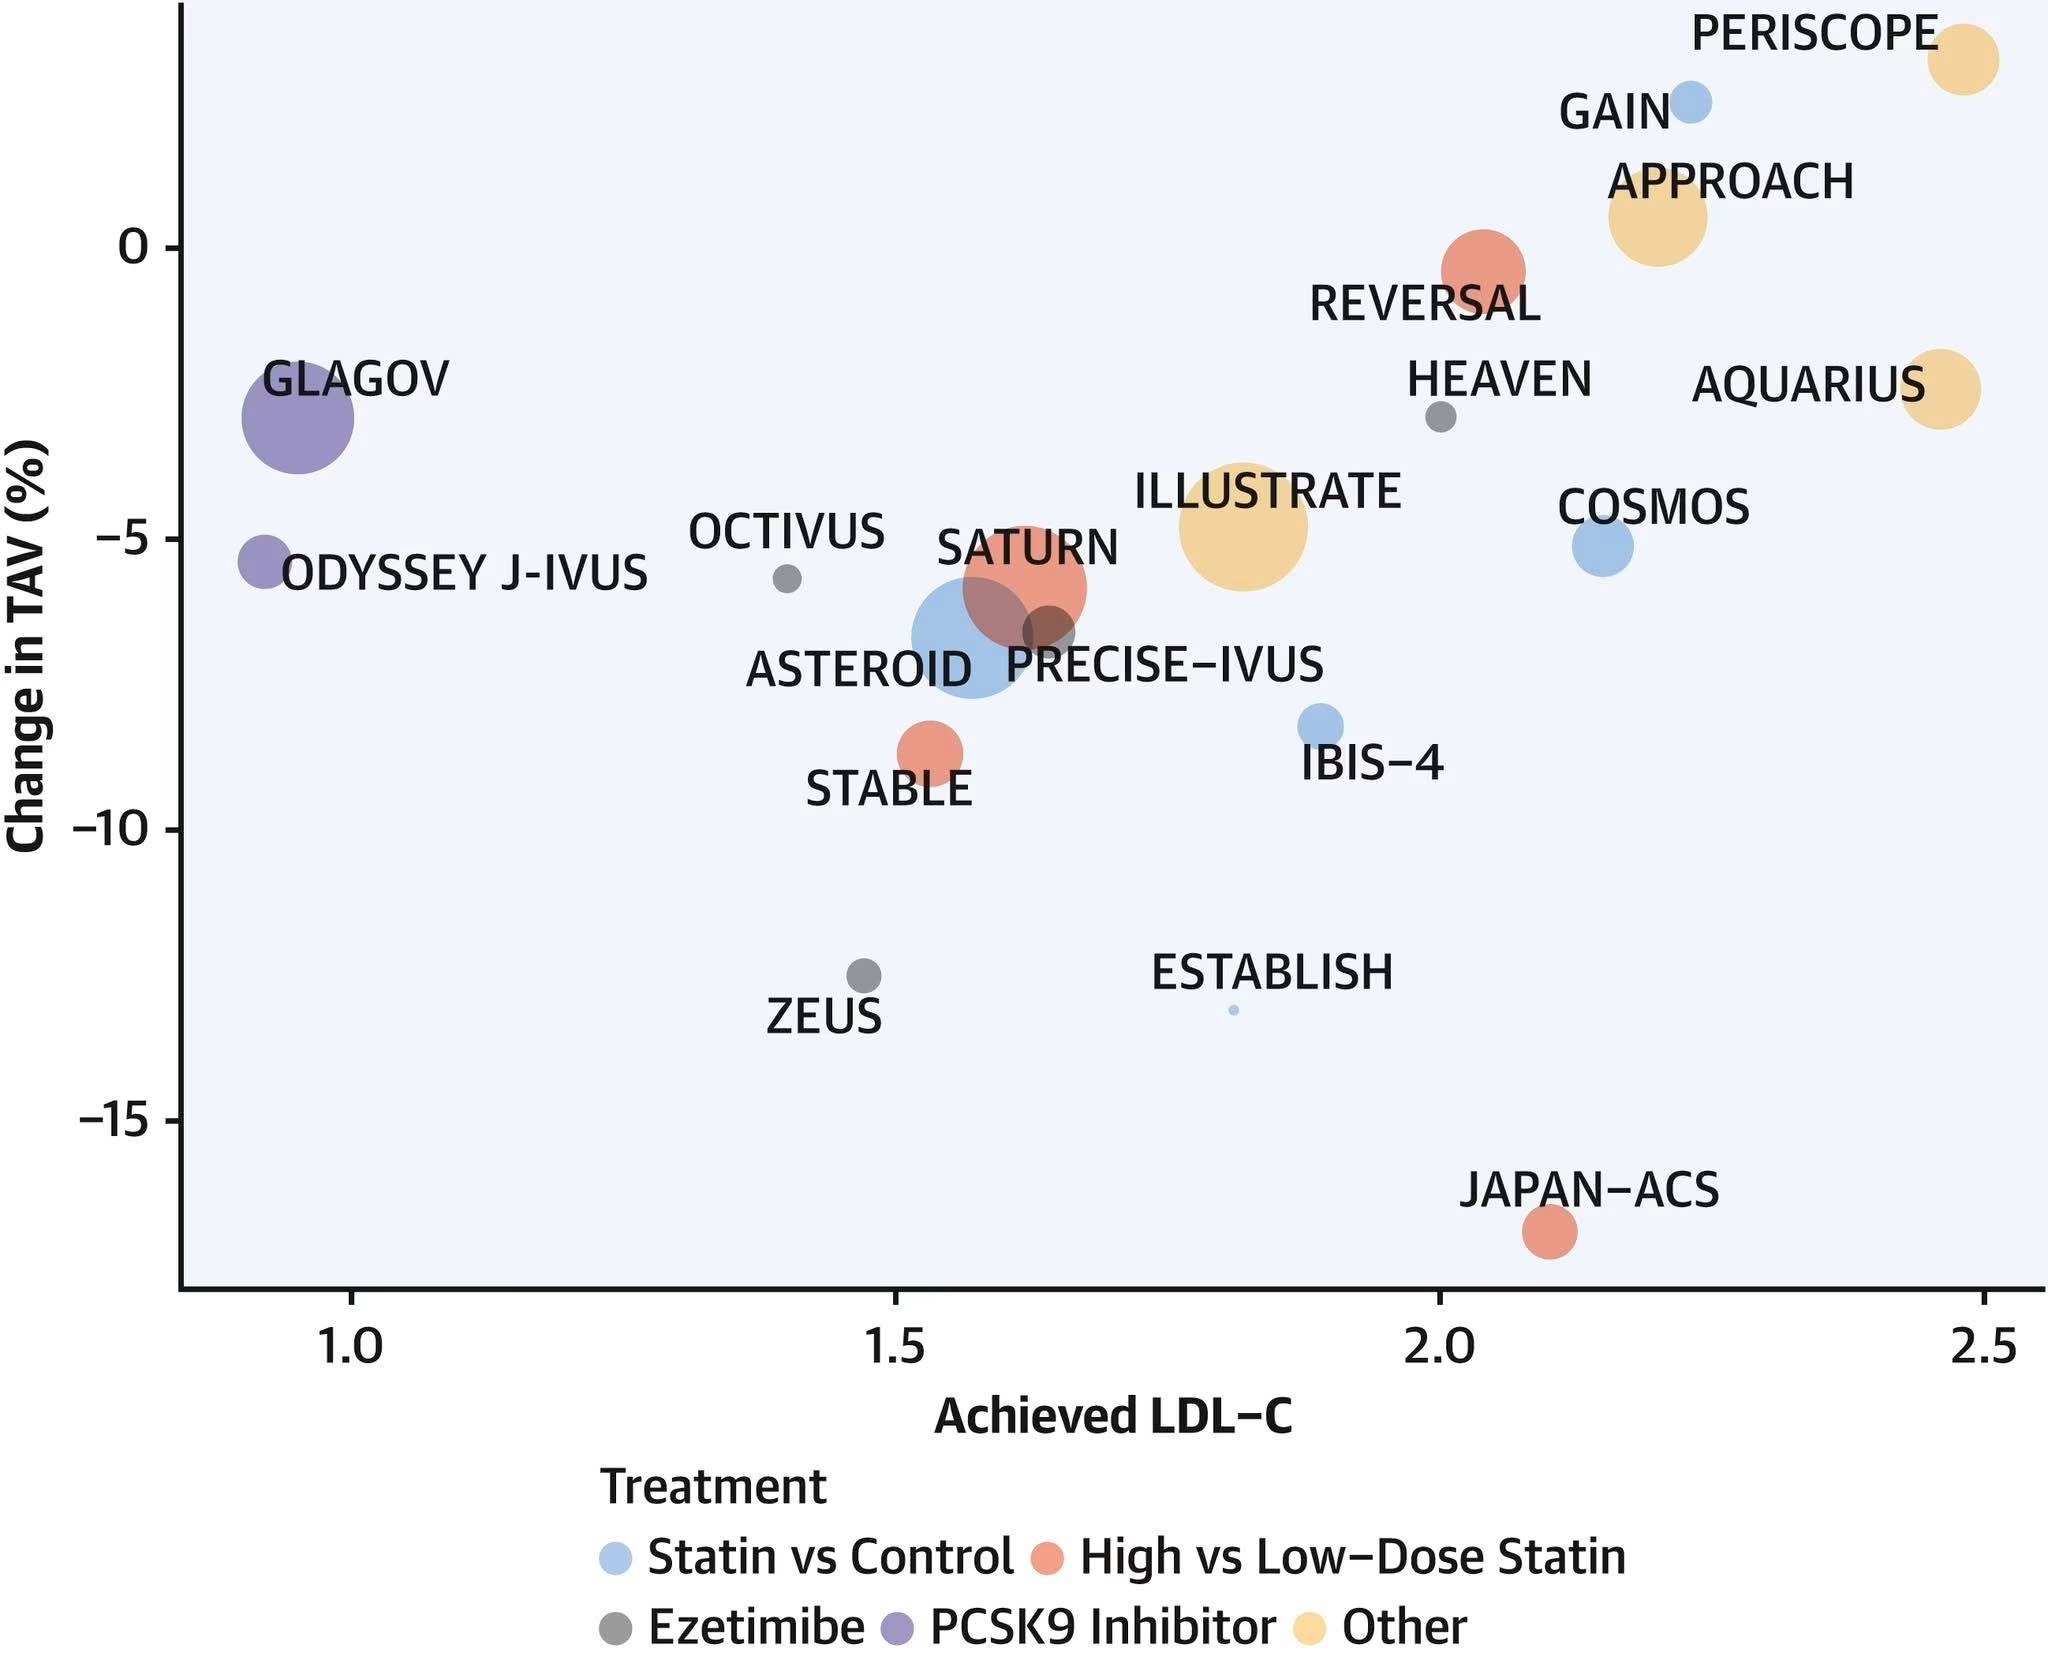
This previous post compares the plaque reversal in Japan-ACS using statins with other trials using ezetimibe, PCSK9 inhibitors, statins, and other drugs: ↪ Plaque volume begins to regress once LDL-C falls below about 90 mg/dL across RCTs
Quoted:
“The JAPAN-ACS (Japan Assessment of Pitavastatin and Atorvastatin in Acute Coronary Syndrome) study was a prospective, randomized, open-label, parallel group study with blind end point evaluation conducted at 33 centers in Japan. A total of 307 patients with ACS undergoing IVUS-guided percutaneous coronary intervention were randomized, and 252 patients had evaluable IVUS examinations at baseline and 8 to 12 months' follow-up. Patients were randomly assigned to receive either 4 mg/day of pitavastatin or 20 mg/day of atorvastatin. The primary end point was the percentage change in nonculprit coronary PV.”
“The mean percentage change in PV was −16.9 ± 13.9% and −18.1 ± 14.2% (p = 0.5) in the pitavastatin and atorvastatin groups, respectively, which was associated with negative vessel remodeling.”
“The administration of pitavastatin or atorvastatin in patients with ACS equivalently resulted in significant regression of coronary PV (Japan Assessment of Pitavastatin and Atorvastatin in Acute Coronary Syndrome; NCT00242944).”
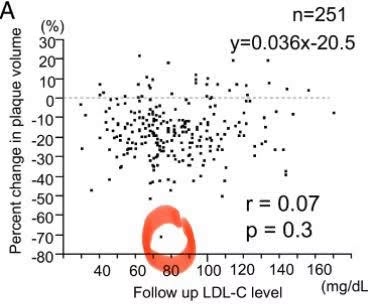
“We found that LDL-C decreased from 130.9 ± 33.3 mg/dl (3.39 ± 0.86 mmol/l) at baseline to 81.1 ± 23.4 mg/dl (2.10 ± 0.61 mmol/l) at 8 to 12 months' follow-up (p < 0.001) in the pitavastatin group and from 133.8 ± 31.4 mg/dl (3.47 ± 0.81 mmol/l) to 84.1 ± 27.4 mg/dl (2.18 ± 0.71 mmol/l; p < 0.001) in the atorvastatin group (Table 2).We found that high-density lipoprotein cholesterol (HDL-C) as well as triglycerides showed comparable increase between the 2 groups. The inflammatory markers, high-sensitivity C-reactive protein, pentraxin3, and white blood cell counts were markedly increased at baseline and were not different between the 2 groups in terms of percent change.”
#reverseHD #statinsHD #statinreverseHD #japanacsHD #atorvastatinHD #pitavastatinHD #tavHD #ivusHD #statinrctsHD #acsHD