Use of statins in patients with chronic kidney disease.
Atorvastatin is usually preferred.
#statinsHD #ckdHD #atorvastatinHD #rosuvastatinHD #ezetimibeHD
Louis shares an MRCP UK explainer on statins in CKD: atorvastatin needs no renal dose adjustment (under 2% renal excretion), while rosuvastatin is 30% renally excreted, needs dose reduction at low eGFR and can cause reversible proteinuria at high doses. KDIGO advises a statin with or without ezetimibe in CKD stages 3-5 not on dialysis.
Use of statins in patients with chronic kidney disease.
Atorvastatin is usually preferred.
#statinsHD #ckdHD #atorvastatinHD #rosuvastatinHD #ezetimibeHD
Atorvastatin vs Rosuvastatin in CKD
Core Concept
Statins in CKD are used for CV risk reduction.
Renal benefits are modest, not primary endpoints.Atorvastatin is generally preferred in moderate–advanced CKD due to:
- Less renal clearance (safe in low eGFR)
- No dose adjustment
- Lower incidence of statin-associated proteinuria
- Some evidence of reduced proteinuria + slower eGFR decline
Rosuvastatin is very potent but requires dose reduction in CKD and high doses may cause proteinuria/hematuria.
Atorvastatin
- Hepatic clearance
- <2% renal excretion
- No dose modification for CKD stages 1–5 (non-dialysis)
Rosuvastatin
- 30% renal excretion
- Requires dose reduction in eGFR <30
- Maximum recommended dose often ≤10 mg/day in severe CKD
- High doses associated with tubular proteinuria (reversible)
Renal Effects of statins
Atorvastatin
- Shown to reduce proteinuria modestly
- May slow eGFR decline
- No significant renal toxicity reports
Rosuvastatin
- Dose-dependent proteinuria + microscopic hematuria
- Mechanism: proximal tubular dysfunction
- Usually reversible with dose reduction or cessation
Guideline-Based (KDIGO)
KDIGO Recommendations:
- Use statin ± ezetimibe in CKD stages 3–5 (not on dialysis)
- Avoid high-dose rosuvastatin in advanced CKD
- Atorvastatin commonly preferred because of pharmacokinetics
Which Statin to Start in CKD?
Preferred First-Line in CKD (Moderate–Advanced):Atorvastatin (10–40 mg/day)
Why?
- Safe in low eGFR
- No dose limits
- Less proteinuria risk
- Good LDL reduction
When to Use Rosuvastatin
- Need stronger LDL lowering
- Patient has early CKD (Stage 1–2)
- Start low dose (5–10 mg) if eGFR <30
Exam clue: Severe CKD + high ASCVD risk → Atorvastatin preferred to avoid rosuvastatin-induced proteinuria.
Louis explains rare dose-related proteinuria, hematuria or AKI with rosuvastatin, especially 40 mg or with CKD. PLANET I and II found rosuvastatin 40 mg lowered eGFR whereas atorvastatin 80 mg reduced proteinuria and preserved function.
Louis explains the blood-brain barrier and cholesterol: the brain makes its own cholesterol separately from blood, so non-statin LDL drugs and hydrophilic statins like rosuvastatin have little brain effect. Lipophilic statins do enter the brain, with promising observational data against Alzheimer's, and a 20,000-person atorvastatin trial is under way. Two prior trials showed statins do not worsen existing Alzheimer's, and midlife high LDL is a leading modifiable dementia risk (2024 Lancet Commission, about 7% of US cases per Louis).
Louis shares a teaching card that atorvastatin is the preferred statin in chronic kidney disease, citing the PLANET trial comparing it with rosuvastatin. His later edit says the original text had a typo: the correct statement is that atorvastatin improved proteinuria but had no effect on eGFR.
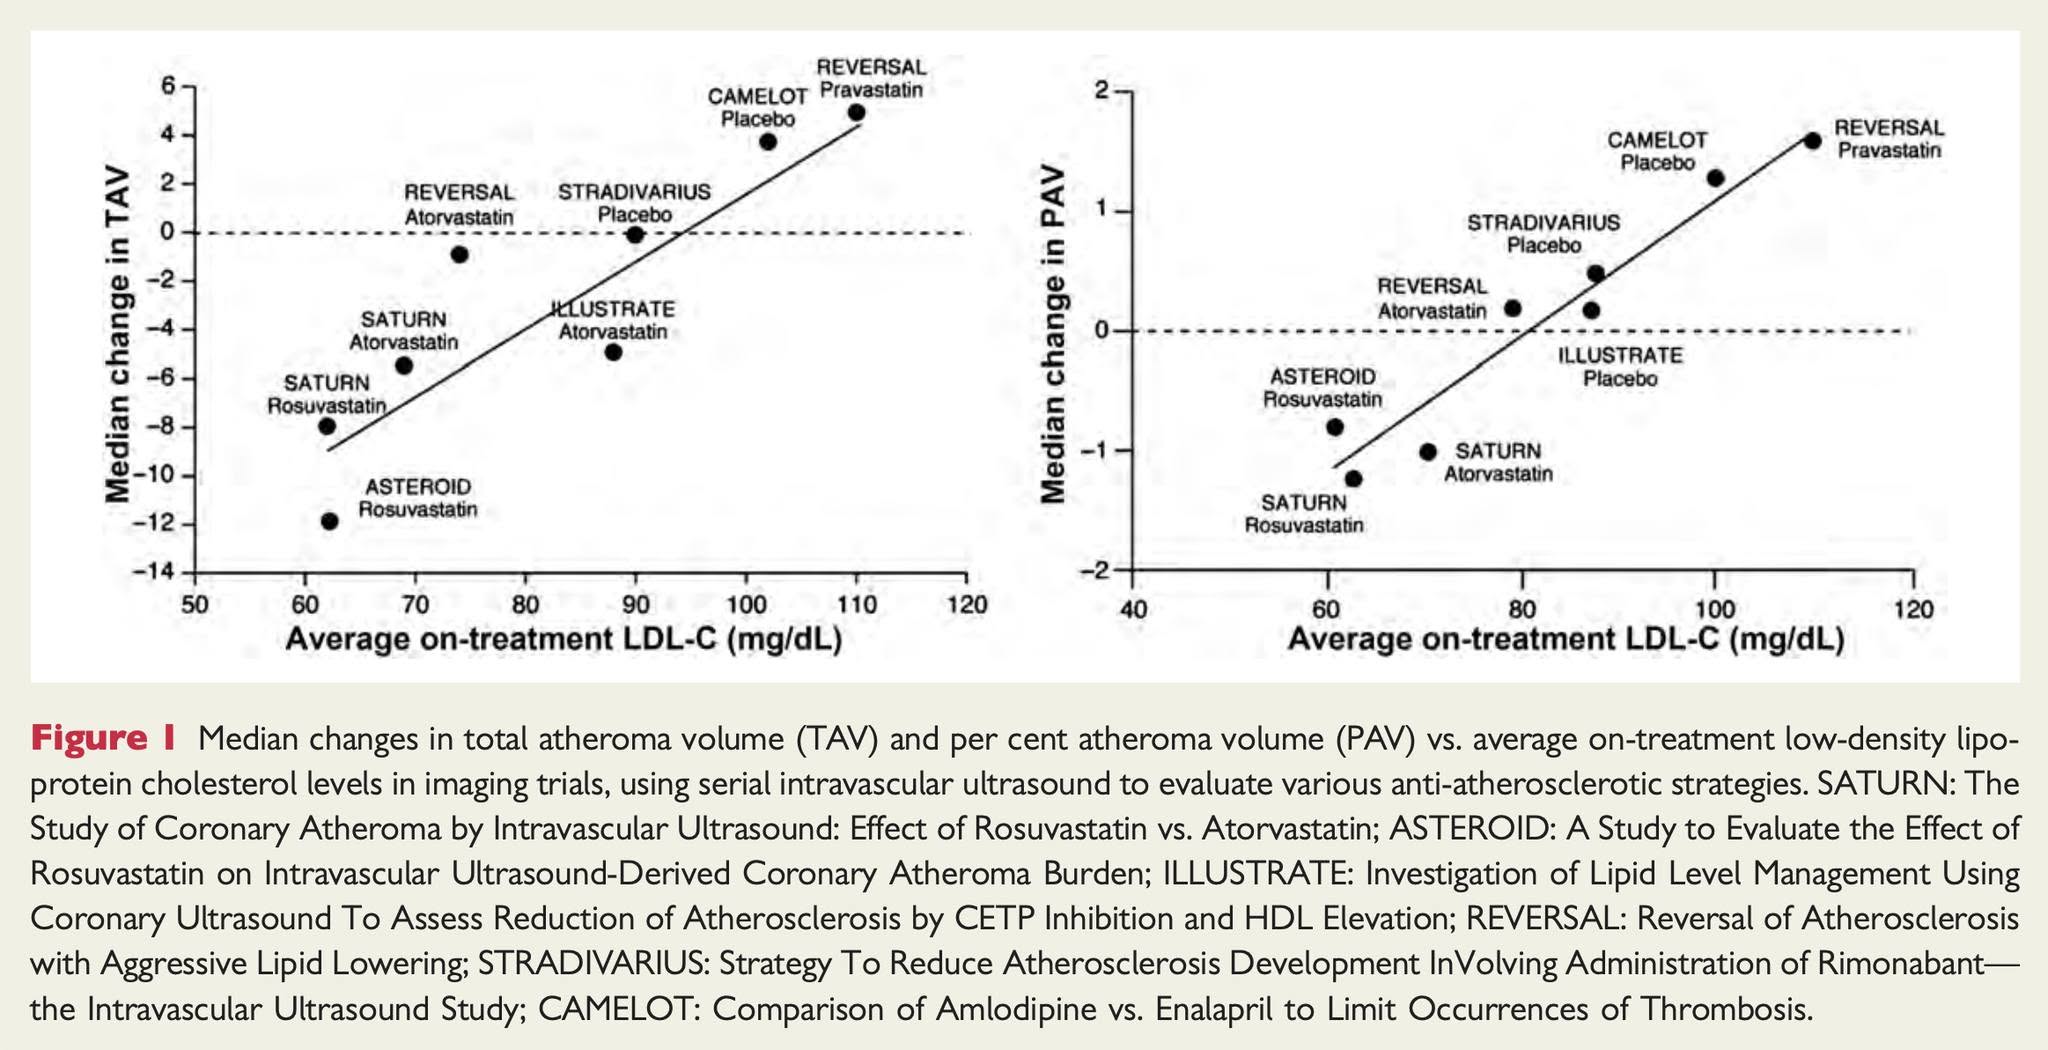
Summarizes Li et al. 2021, a meta-analysis of 31 IVUS studies (4,997 patients) showing lipid-lowering therapy lowers atheroma volume, with maximal regression at LDL below 80 and HDL above 45 mg/dL. It also covers the SATURN analysis, where rosuvastatin 40 mg regressed plaque more than atorvastatin 80 mg.
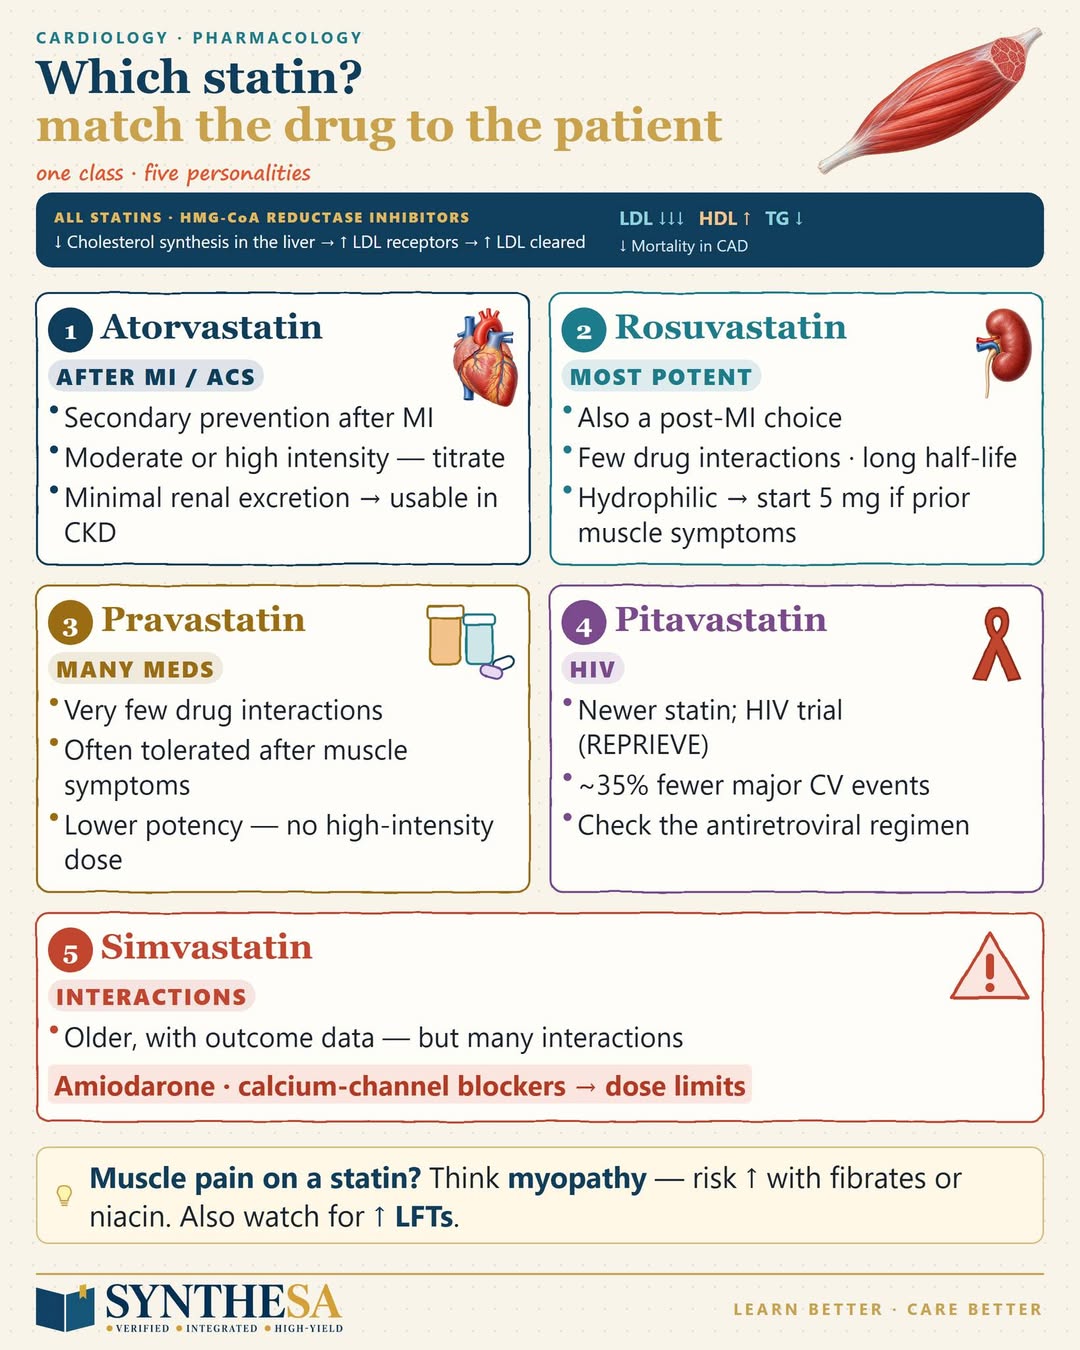
A shared infographic summarizes how statins work and how the choice varies by patient: atorvastatin after MI/ACS and usable in CKD, rosuvastatin as the most potent with few interactions. General reference without study data.
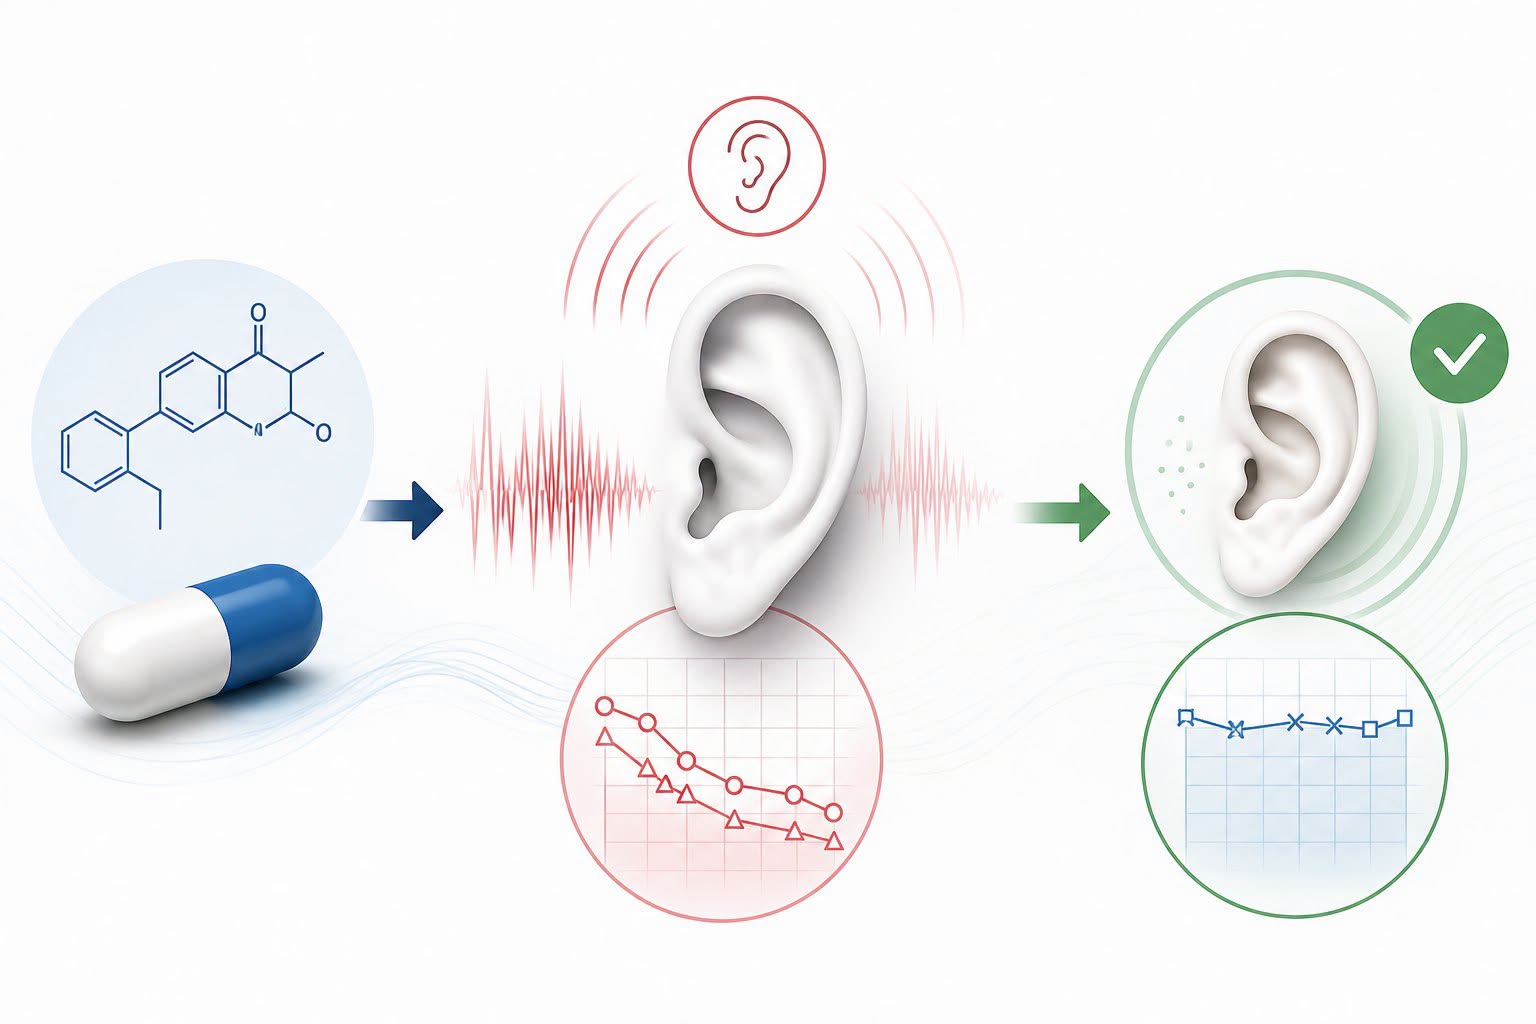
Louis shares a Journal of Medical Case Reports case of atorvastatin-associated sensorineural hearing loss that resolved completely after stopping the drug. She was then switched to rosuvastatin without problems. It is a single rare case and not evidence of common risk.