There is currently no strong evidence from randomized trials that hormone replacement therapy (HRT) reduces risk for dementia.
But there are theoretical reasons why it might help in some cases.
However, there could be specific risks for APOE4 carriers who already have MCI or dementia.
This post discusses the indications for which the evidence for benefits of HRT is strongest (like bone protection and symptomatic relief from menopause).
It also discusses which groups of people are likely to experience more risk than benefit from HRT.
In addition, the post does a very good job of summarizing the evidence for HRT when it comes to cardiovascular disease, both positive and negative. It’s impossible to talk about dementia without also talking about CVD, since both are so strongly linked.
#hrtHD #dementiaHD #apoe4HD #alzheimersHD #estrogenHD #cvdHD
 yassinelab.orgHormone Replacement Therapy, Brain Health, and APOE4Understanding the benefits, risks, and unanswered questions surrounding hormone therapy and cognitive aging.yassinelab.org
Hussein Yassine, M.D., Director of the Center for Personalized Brain Health at the Keck School of Medicine at USC and researcher on APOE 4, recently posted straightforward questions raised by a 63 year old woman with ApoE 4/4 and very mild subjective memory complaints:
➤ Is hormone therapy safe for the brain?
➤ Can it prevent dementia?
➤ How long should I stay on it?
These questions are becoming increasingly common as more women remain on hormone therapy longer and awareness of Alzheimer’s disease grows.
But answering them leads to a careful discussion on benefit versus risk and involves cardiology as much as neurology. Dr. Yassine reviewed the woman's case with Dr. Howard Hodis, Director of the Atherosclerosis Research Unit at USC.
Dr. Hodis has spent decades studying how estrogen interacts with vascular aging, particularly how the timing of hormone therapy relative to menopause may determine whether it helps or harms the cardiovascular system.
Dr. Yassine's Substack is at the link above and is excerpted below, with light editing for clarity.
🔹 What we know about benefits:
Hormone therapy was originally developed to treat symptoms of menopause. Among available treatments, estrogen therapy remains the most effective therapy for vasomotor symptoms.
Hormone therapy also plays an important role in bone health. Randomized trials show estrogen therapy reduces fractures by 30–50% in postmenopausal women.
❤️ For symptom relief and bone protection, the benefits of hormone therapy are well established.
🔹 The controversy arises when hormone therapy is discussed as a preventive therapy for chronic diseases, particularly cardiovascular disease and dementia.
🔹Hormone therapy is often discussed as if it were a single treatment with a single risk profile. Biologically, it is not. The effects of estrogen depend on several factors:
➤ when therapy begins
➤ the health of the vascular system
➤ the hormone formulation
➤ the biology of the individual patient
❤️ Who Should Not Take Hormone Therapy
Although hormone therapy is highly effective for menopausal symptoms, it is not appropriate for everyone. Most clinical guidelines recommend avoiding systemic estrogen therapy in women with certain conditions where risks may outweigh benefits.
These include:
➤ Estrogen-dependent cancers, particularly breast cancer
➤ A history of blood clots such as deep vein thrombosis or pulmonary embolism
➤ Stroke or significant cardiovascular disease
➤ Active liver disease
➤ Unexplained vaginal bleeding
The concern in these situations is that estrogen can influence coagulation pathways, hormone-sensitive tissues, and vascular biology, potentially increasing the risk of recurrent disease.
🔹 Importantly, these recommendations apply primarily to systemic hormone therapy. In some cases, local vaginal estrogen preparations may still be considered because systemic absorption is minimal. As with many areas of menopause care, decisions often require individualized risk assessment and shared decision-making between patient and clinician.
❤️ The Timing Hypothesis
The timing hypothesis proposes that estrogen’s effects depend on the stage of vascular—and possibly other organ—health when therapy begins.
Early after menopause, when arteries are relatively healthy, estrogen appears to support vascular function through:
➤ improved endothelial function
➤ reduced LDL oxidation
➤ improved vasodilation
➤ reduced inflammation
🔹 But once atherosclerosis is established, estrogen may behave differently and increase enzymes involved in plaque instability
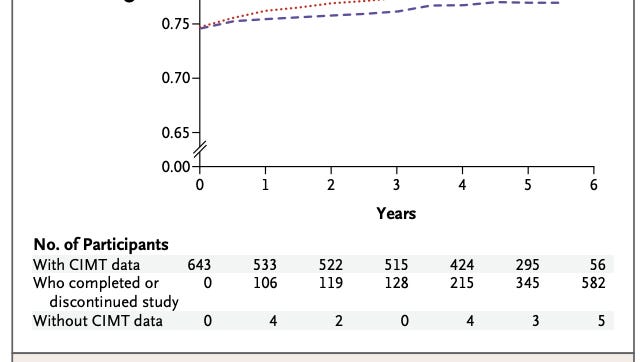
The ELITE trial (Early vs Late Intervention Trial with Estradiol) directly tested this "timing" hypothesis. Women were randomized to estradiol or placebo and stratified according to time since menopause.
➤ Women who began estradiol within six years of menopause showed slower progression of carotid atherosclerosis (carotid artery plaques).
➤ Women who began estradiol therapy more than ten years after menopause showed no benefit over placebo on carotid artery plaques.
Looking at actual cardiac events in studies that both looked at women who had used or not used HRT, and a randomized Danish trial that followed recently menopausal women for up to 16 years, the conclusions were similar:
🔹 Among women who started hormone therapy before age 60, or within 10 years of menopause, studies show approximately:
➤ 30–40% reduction in coronary heart disease events
➤ ~30% reduction in all-cause mortality
➤ A Danish randomized trial similarly found reduced cardiovascular events in recently postmenopausal women receiving hormone therapy for up to 16 years.
🧠 What About Our Brains and Hormone Therapy?
Seems like a "no-brainer" that hormone therapy after menopause would help our cognition.
Estrogen influences several biological processes relevant to cognition:
➤ synaptic plasticity
➤ mitochondrial function
➤ cerebral blood flow
➤ inflammation
➤ neuronal metabolism
This biological rationale led many researchers to believe hormone therapy might help prevent Alzheimer’s disease.
🔹However, clinical trials have not confirmed that expectation. Studies suggest that hormone therapy begun earlier in life does not increase dementia risk, but it also has not convincingly reduced it.
🔹 At present, there is no strong randomized evidence that hormone therapy prevents dementia.
❤️ BUT: The ApoE4 Female Brain May Be Different
The picture becomes more complex when genetics are considered. The APOE4 allele is the strongest common genetic risk factor for Alzheimer’s disease.
🔹APOE4 carriers often show:
➤ earlier amyloid deposition
➤ greater vascular dysfunction
➤ increased blood–brain barrier fragility
🔹Importantly, not all APOE4 carriers are the same. A cognitively normal APOE4 carrier may still have significant neurological reserve.
🔹 But once someone develops mild cognitive impairment or dementia, the brain becomes far less resilient. And because estrogen signaling can influence the activity of the enzyme MMP-9, and over-activity of MMP-9 in a less resilient brain can increase the risk of:
➤ plaque rupture in cardiovascular disease
➤ blood–brain barrier breakdown
➤ neuroinflammation
❤️ Bottom Line:
We still lack trials that start hormone therapy near menopause, follow women long-term, and specifically evaluate cognitive outcomes in APOE4 carriers.
Studies using modern hormone formulations and neuroimaging or biomarker endpoints are also limited.
These gaps mean that the effects of hormone therapy on dementia risk, especially in genetically vulnerable populations, remain uncertain.
Taken together, these limitations mean that hormone therapy decisions still require clinical judgment rather than simple rules.
Ultimately, hormone therapy should not be viewed as either a miracle therapy or a dangerous drug.
Until the science becomes clearer, the most important step is not a universal rule, but careful conversations between patients and their physicians, weighing symptoms, risks, and individual goals.
🔹 P.S. For those wanting the answer to the patient's questions:
For that 63 year old woman, Dr. Yassine advised that hormone therapy likely helped her menopausal symptoms, and, given that she started treatment near menopause and has tolerated it well, it may still be reasonable to continue.
But when it comes to protecting the brain from dementia, science has not yet provided a definitive answer.
New memory concerns should prompt a formal cognitive assessment and a thoughtful discussion about whether continuing hormone therapy remains appropriate.