Everybody who tracks their CAC score should read this.
#cacHD #reverseHD #plaqueHD #statinreverseHD #cacreverseHD #calcifiedplaqueHD #calcificationparadoxHD #statinscacHD #pcsk9cacHD
Gokhan Can's explainer, shared by Louis, says the Agatston score has quirks. A rising score on statins and lifestyle may reflect plaque stabilization via denser calcium rather than worsening disease.
Everybody who tracks their CAC score should read this.
#cacHD #reverseHD #plaqueHD #statinreverseHD #cacreverseHD #calcifiedplaqueHD #calcificationparadoxHD #statinscacHD #pcsk9cacHD
The "Calcification Paradox": Why Your Calcium Score Can Rise Even as Your Heart Gets Healthier
#
The gold-standard Coronary Artery Calcium (CAC) scan has a mathematical quirk. Understanding how the score is calculated reveals why a higher number doesn't always mean significantly worse disease—especially for athletes and those on statins.
If you are proactive about heart health, you likely know your Agatston Score—the number you get from a Coronary Artery Calcium (CAC) scan.
For decades, the Agatston score has been our best tool for assessing initial cardiovascular risk. A score of zero is excellent; a score over 400 suggests significant risk. It’s a powerful wake-up call that has saved countless lives by identifying silent heart disease.
However, many members of this community run into a confusing and frightening scenario: You adopt a heart-healthy lifestyle, you start statin therapy, you exercise religiously, and a year or two later, you repeat the scan… and your score has gone up.
Does this mean your lifestyle changes failed? Does it mean you are rapidly getting worse?
Not necessarily. In fact, in many cases, a rising score in the context of aggressive treatment can actually be a sign of plaque stabilization.
To understand why, we have to look under the hood at the tricky math and image processing "shortcuts" used to calculate the Agatston score.
The Flaw in the Formula: It’s Not Just About VolumeThe biggest misconception about the CAC score is that it measures the exact total volume of calcium in your arteries. It does not.
The Agatston score, developed in the early 1990s based on older CT technology, uses a weighted formula that relies heavily on density thresholds.
The computer looks at slices of your heart. When it spots calcium, it measures the area, and then multiplies that area by a "density factor" of 1, 2, 3, or 4, based on how bright (dense) the calcium appears on the X-ray.
Here is the critical shortcut: The density multiplier is not a smooth curve; it’s a rigid step system.
- Factor 1: Low density plaque
- Factor 2: Medium density plaque
- Factor 3: High density plaque
- Factor 4: Very high density plaque
The Problem: Imagine a patch of plaque that is right on the borderline between "medium" and "high" density. If that plaque becomes just tiny bit denser over a year, the mathematical multiplier jumps from a 2 to a 3.
Suddenly, the score contribution from that single plaque increases by 50%, even though the actual size of the plaque barely changed.
The Statin Paradox: Turning "Jell-O" into "Concrete"
This density shortcut is why statin therapy often causes CAC scores to rise faster than expected.
We tend to think of all plaque as "bad," but cardiologists differentiate between two types:
- Soft Plaque (Lipid-Rich): This is dangerous. It’s like Jell-O inside the artery wall—inflamed, unstable, and prone to rupturing, which causes heart attacks. Soft plaque does not show up on a standard calcium scan.
- Hard Plaque (Calcified): This is essentially scar tissue. It is like concrete. While it narrows the artery, it is stable and much less likely to rupture abruptly.
How Statins Work: Statins aggressively lower LDL cholesterol and reduce inflammation. This process reduces the lipid core and inflammation. As the vessel wall heals, the plaque naturally calcifies—effectively turning unstable Jell-O into stable concrete.
Because the statin is making the plaque denser, it bumps the plaque into those higher Agatston multipliers (pushing a "2" to a "3" or a "4").
The Result: Your arteries are becoming safer because the rupture risk is dropping, but your score is rising because the math penalizes increased density.
The Athlete’s Heart and the "Blooming" ArtifactWe see a similar phenomenon in high-level endurance athletes, who often have surprisingly high CAC scores despite excellent functional health.
The mechanical stress of high-output exercise can cause minor wear and tear on arteries, which the body repairs with calcium—again, a stabilizing mechanism.
Furthermore, there is an image processing issue known as the "Blooming Artifact."
On a CT scan, very dense objects (like highly calcified plaque) tend to glow brightly and "bleed" into surrounding pixels. The computer perceives this glowing object as being physically larger than it actually is.
As an athlete or statin user develops denser, more stable plaque, the "blooming" effect makes the plaque look bigger to the computer, further inflating the score disproportionately to the actual disease burden.
The Takeaway: Don't Panic, Look at the Big PictureThe Agatston score remains excellent for determining your initial baseline risk. If you have a score of 500, you have coronary artery disease, regardless of the math flaws.
However, using the Agatston score to track progression over short periods (like 1–2 years) is fraught with difficulty, especially if you are on treatment.
What should you do if your score rises?
- Don't stop your meds: If you are on a statin and your score rises, it is very likely the medication doing its job—stabilizing dangerous plaque.
- Look at the company it keeps: A rising CAC score in isolation is different than a rising CAC score accompanied by high ApoB, high inflammation (hs-CRP), and poor metabolic health. If your other markers are improving, a rising CAC is less concerning.
- Talk about "Volume Score": Some modern CT reports now include a "Volume Score" or "Mass Score" alongside the Agatston score. These newer metrics try to measure the actual amount of calcium without the confusing density multipliers. They are often better for tracking progression over time.
This paradox is exactly why most major heart guidelines recommend against re-scanning your calcium score once you are already on treatment. The number becomes a confusing metric once statins are involved.
Conclusion:
A calcium score is a vital piece of data, but it is just one piece of the puzzle. Don't let the quirky math of a 30-year-old algorithm derail your confidence in your prevention plan. Work closely with a cardiologist who understands the nuances of plaque stabilization and looks beyond just the number.
Scientific References & Further Reading
- The "Density" Flaw: Proof that Denser is Safer
- Study: Criqui, M. H., et al. (2014). "Calcium Density of Coronary Artery Plaque and Risk of Incident Cardiovascular Events." JAMA, 311(3), 271–278.
- Key Takeaway: This landmark study from the MESA cohort proved that for any given volume of plaque, higher density is associated with lower cardiovascular risk. It highlights the fundamental flaw in the Agatston score, which mathematically penalizes patients as their plaque becomes denser and safer.
- The Statin Paradox: Plaque Shrinks, but Score Rises
- Study: Puri, R., et al. (2015). "Impact of Statins on Serial Coronary Calcification During Atheroma Progression and Regression." Journal of the American College of Cardiology, 65(15), 1537–1548.
- Key Takeaway: Using advanced imaging (IVUS), researchers showed that while statins successfully shrunk the total volume of dangerous plaque, they simultaneously caused calcium scores to rise. This confirms that a rising score on statins often reflects healing (calcification), not disease progression.
- High-Dose Statins and "Accelerated" Calcification
- Study: Henein, M. Y., et al. (2015). "High dose and long-term statin therapy accelerate coronary artery calcification." International Journal of Cardiology, 184, 581–586.
- Key Takeaway: This study explicitly links long-term, high-intensity statin use with accelerated calcification. It serves as a crucial reference for patients concerned that their medication is "making their score worse."
- The Athlete’s Heart: High Scores, Low Mortality
- Study: DeFina, L. F., ... Levine, B. D. (2019). "Association of All-Cause and Cardiovascular Mortality With High Levels of Physical Activity and Concurrent Coronary Artery Calcification." JAMA Cardiology, 4(2), 174–181.
- Key Takeaway: This study followed highly active athletes (averaging 35 miles of running/week). Although the athletes had much higher calcium scores than sedentary people, they did not have an increased risk of dying. This suggests their calcification is a stable, benign adaptation to exercise.
- The Technical Flaws: Why the Agatston Score needs an Update
- Study: Blaha, M. J., et al. (2017). "Coronary Artery Calcium Scoring: Is It Time for a Change in Methodology?" JACC: Cardiovascular Imaging, 10(8), 923–937.
- Key Takeaway: A comprehensive review explaining the technical limitations of the traditional score, including the "Blooming Artifact" (where bright calcium looks artificially large) and the stepwise density weighting. It argues for moving toward "Volume Scoring" or "Mass Scoring" for better accuracy.
Louis recommends a Gokhan Can article explaining how the Agatston score is calculated and why calcium can rise as soft plaque regresses on statins, especially in athletes.
Louis argues a high CAC score predicts risk mainly because calcified plaque reflects the amount of soft plaque, which is the dangerous part. He says to focus on reversing or stabilizing soft plaque rather than lowering CAC, and notes randomized outcome trials are needed.
The post says about 64% of heart attacks from acute thrombosis come from rupture of soft lipid-rich plaque and about 25% from erosion of soft plaque, while only about 5% involve calcified nodules. Because statins and other lipid-lowering drugs stabilize and reverse soft plaque, the poster argues they address the plaque type most responsible for heart attacks.
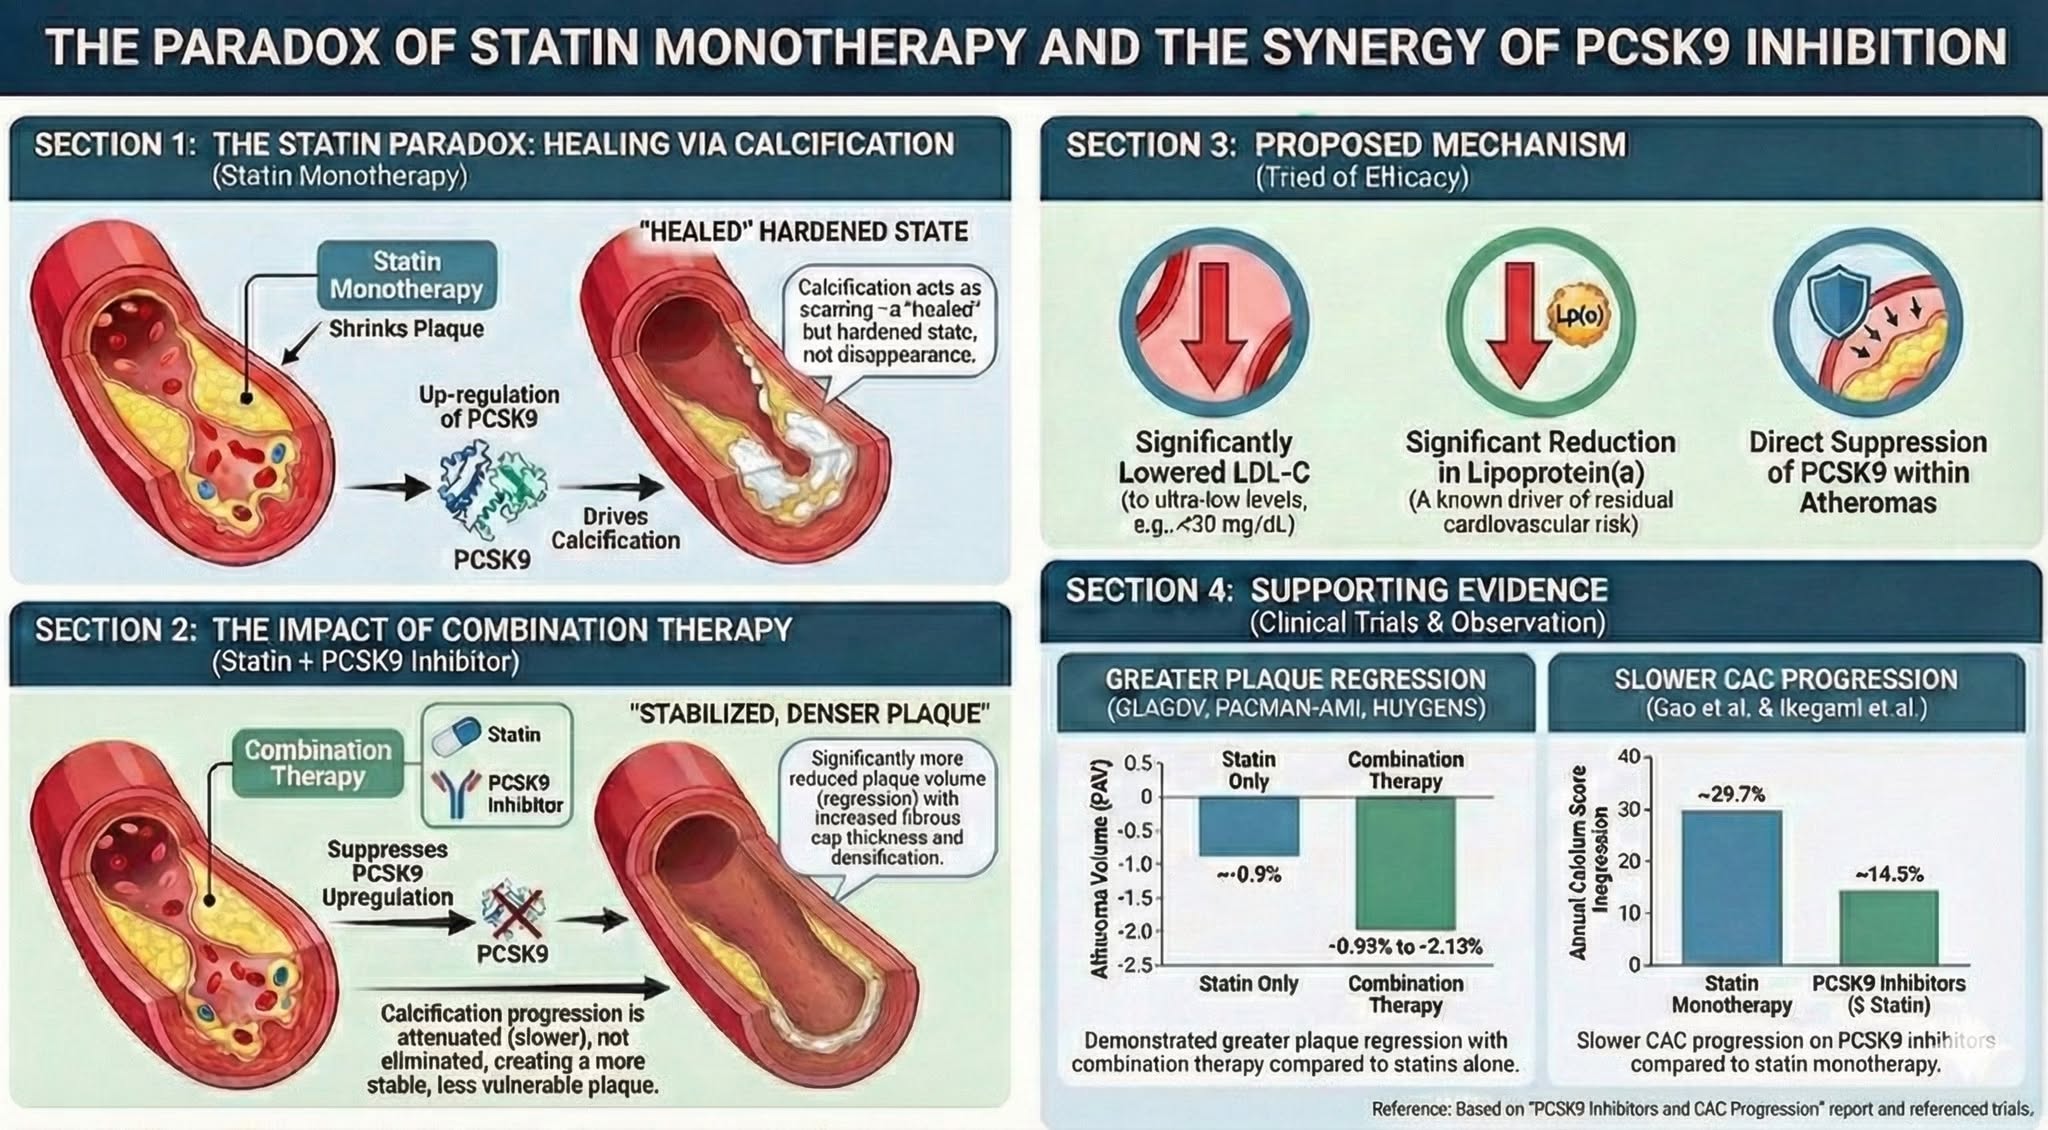
Louis highlights Gokhan Can's article on imaging evidence that PCSK9 inhibitors shrink plaque without the calcific increase often seen with statins. He cautions that no randomized outcome trials test PCSK9 inhibitors as monotherapy, though adding one to a statin attenuates statin-induced calcification and lowers events more than statins alone.
Louis shares serial coronary CTA results from the PARADIGM study showing statin use was associated with larger decreases in low-attenuation and fibro-fatty plaque and larger increases in dense calcified plaque. He notes at least six RCTs show statins reduce total plaque volume even while calcified plaque rises.
Louis tells group members with high CAC that the risk is high but manageable: about 30 lb weight loss clears liver and pancreas fat and can reverse soft plaque, LDL below 70 mg/dL often halts or reverses plaque, a Mediterranean diet has the most evidence, and exercise lowers risk at the same CAC.