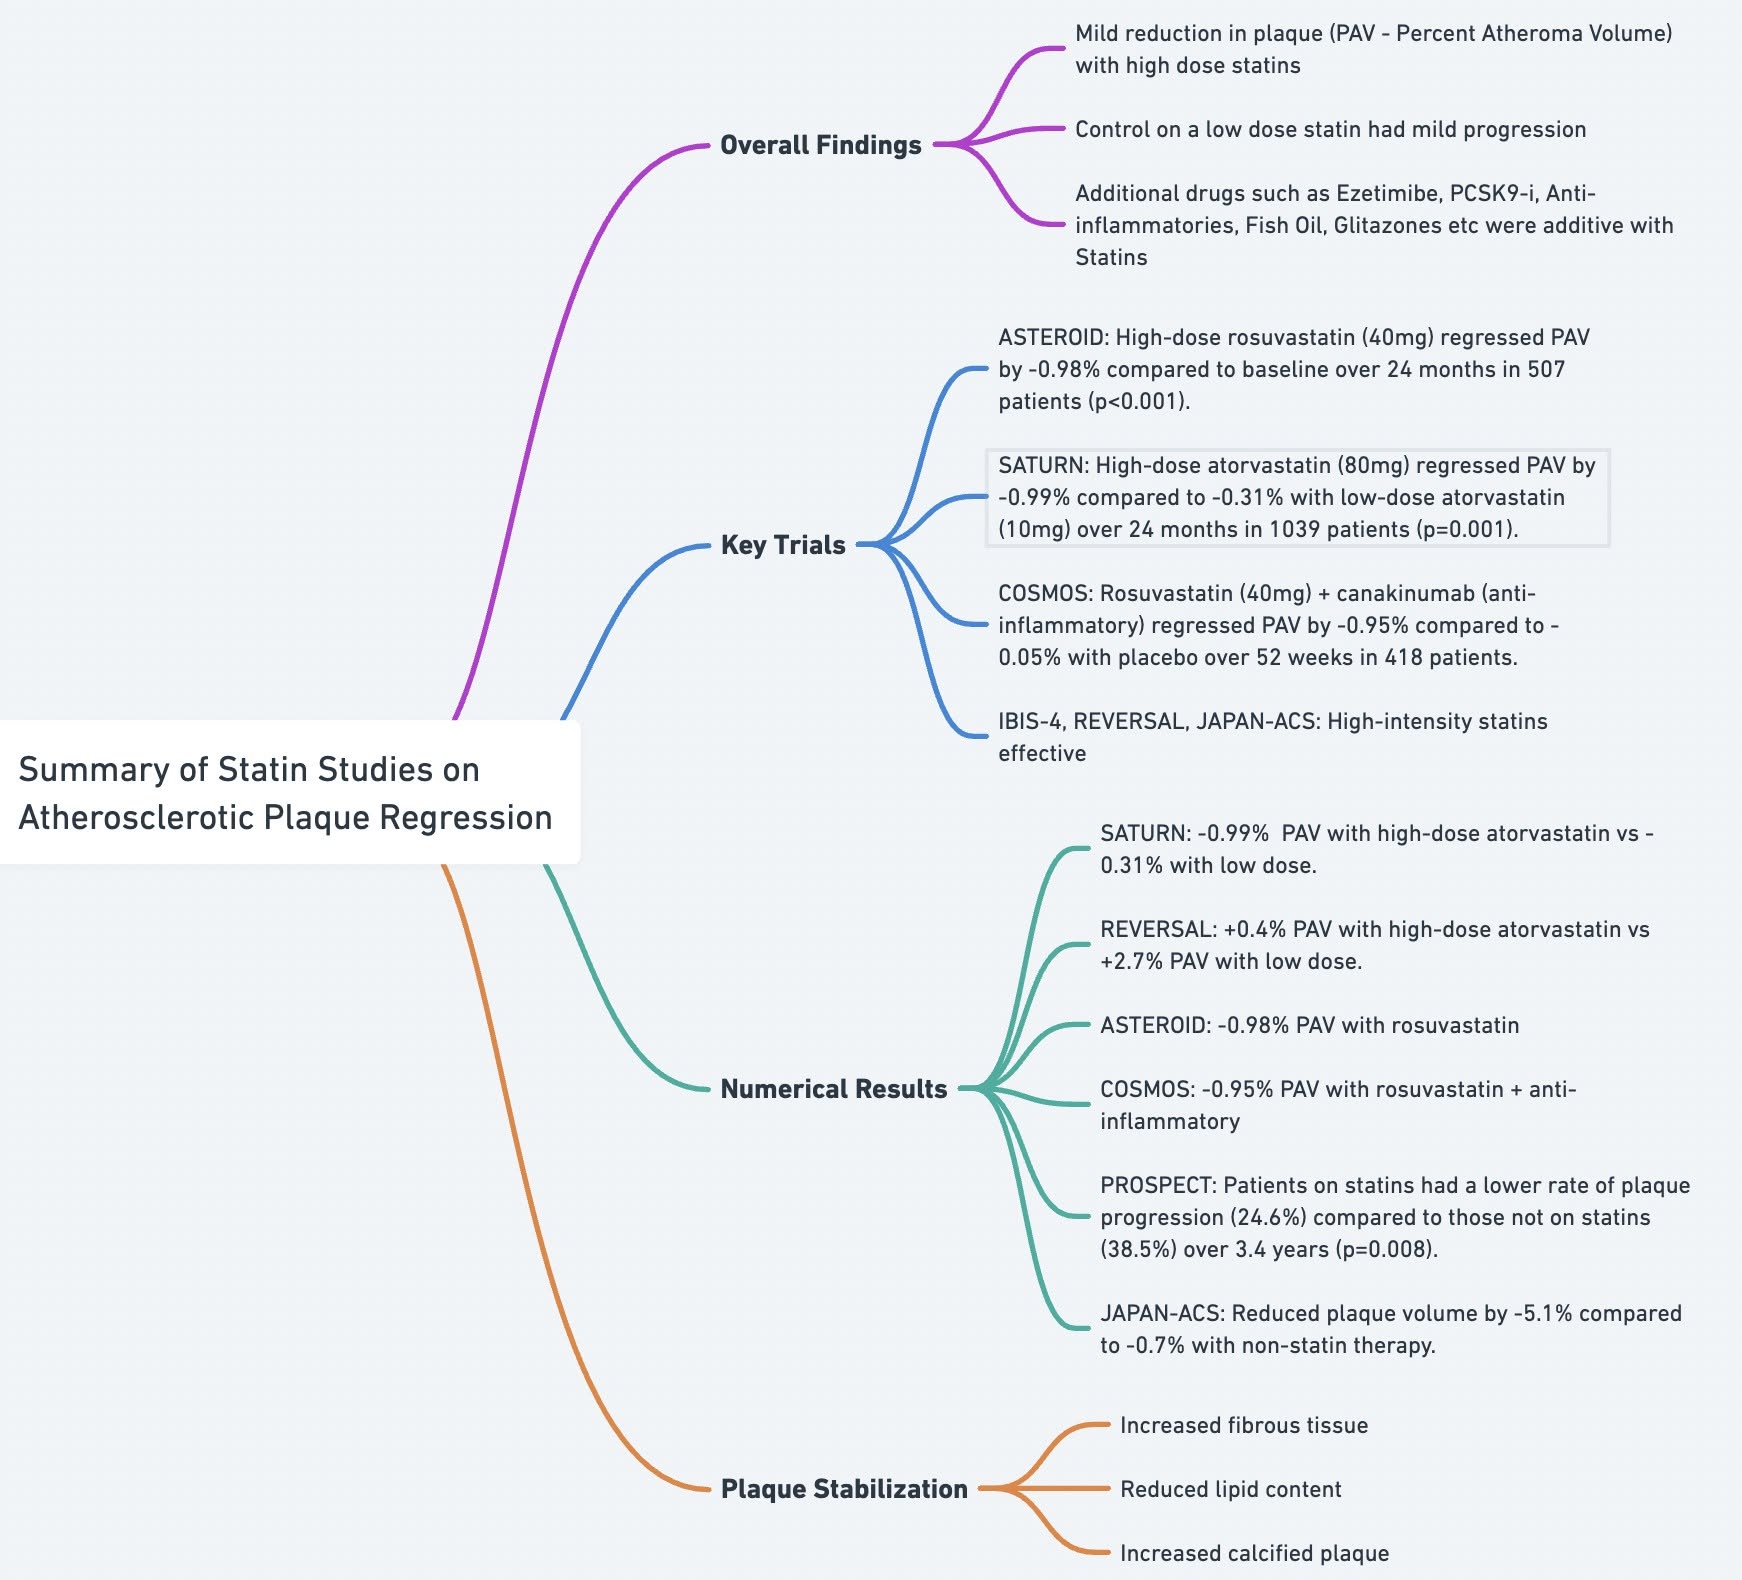
Short post pointing to the author's blog roundup of statin trials that showed plaque regression. The post itself has little text beyond the heading and link.
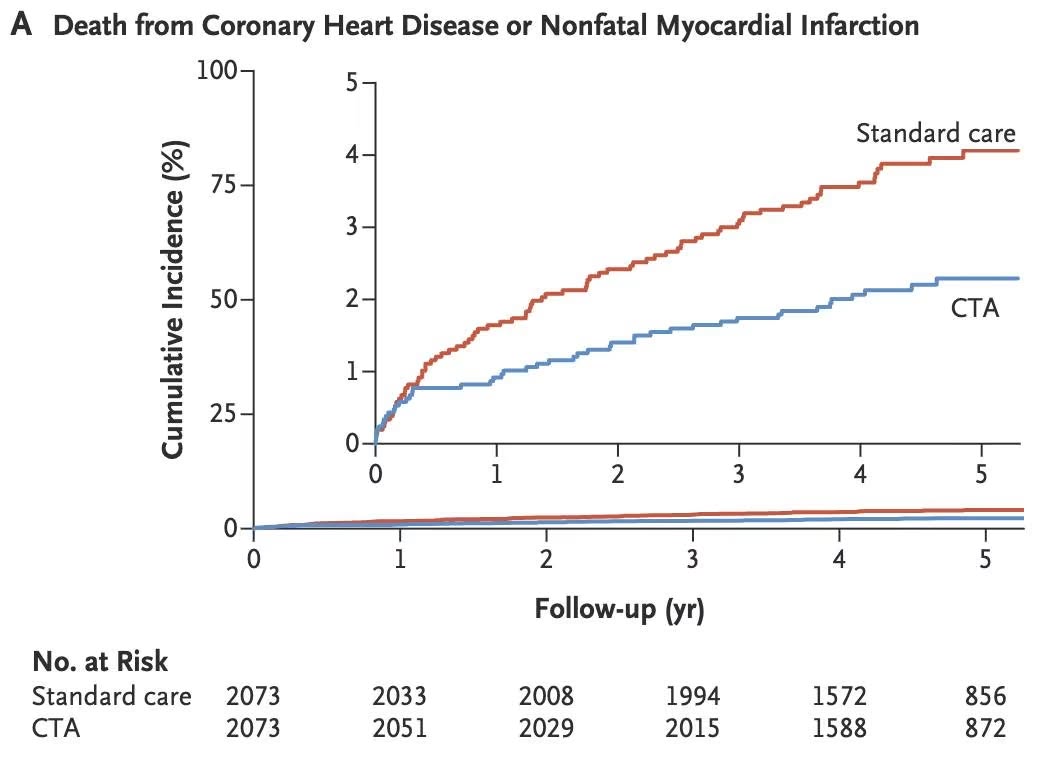
Summarises SCOT-HEART (4,146 patients with stable chest pain, standard care vs standard care plus coronary CTA). CTA guidance lowered coronary death or nonfatal MI to 2.3% from 3.9%, mainly by directing aspirin and statin use to patients with plaque. Total procedures were similar by year 5; results apply to chest-pain patients only.
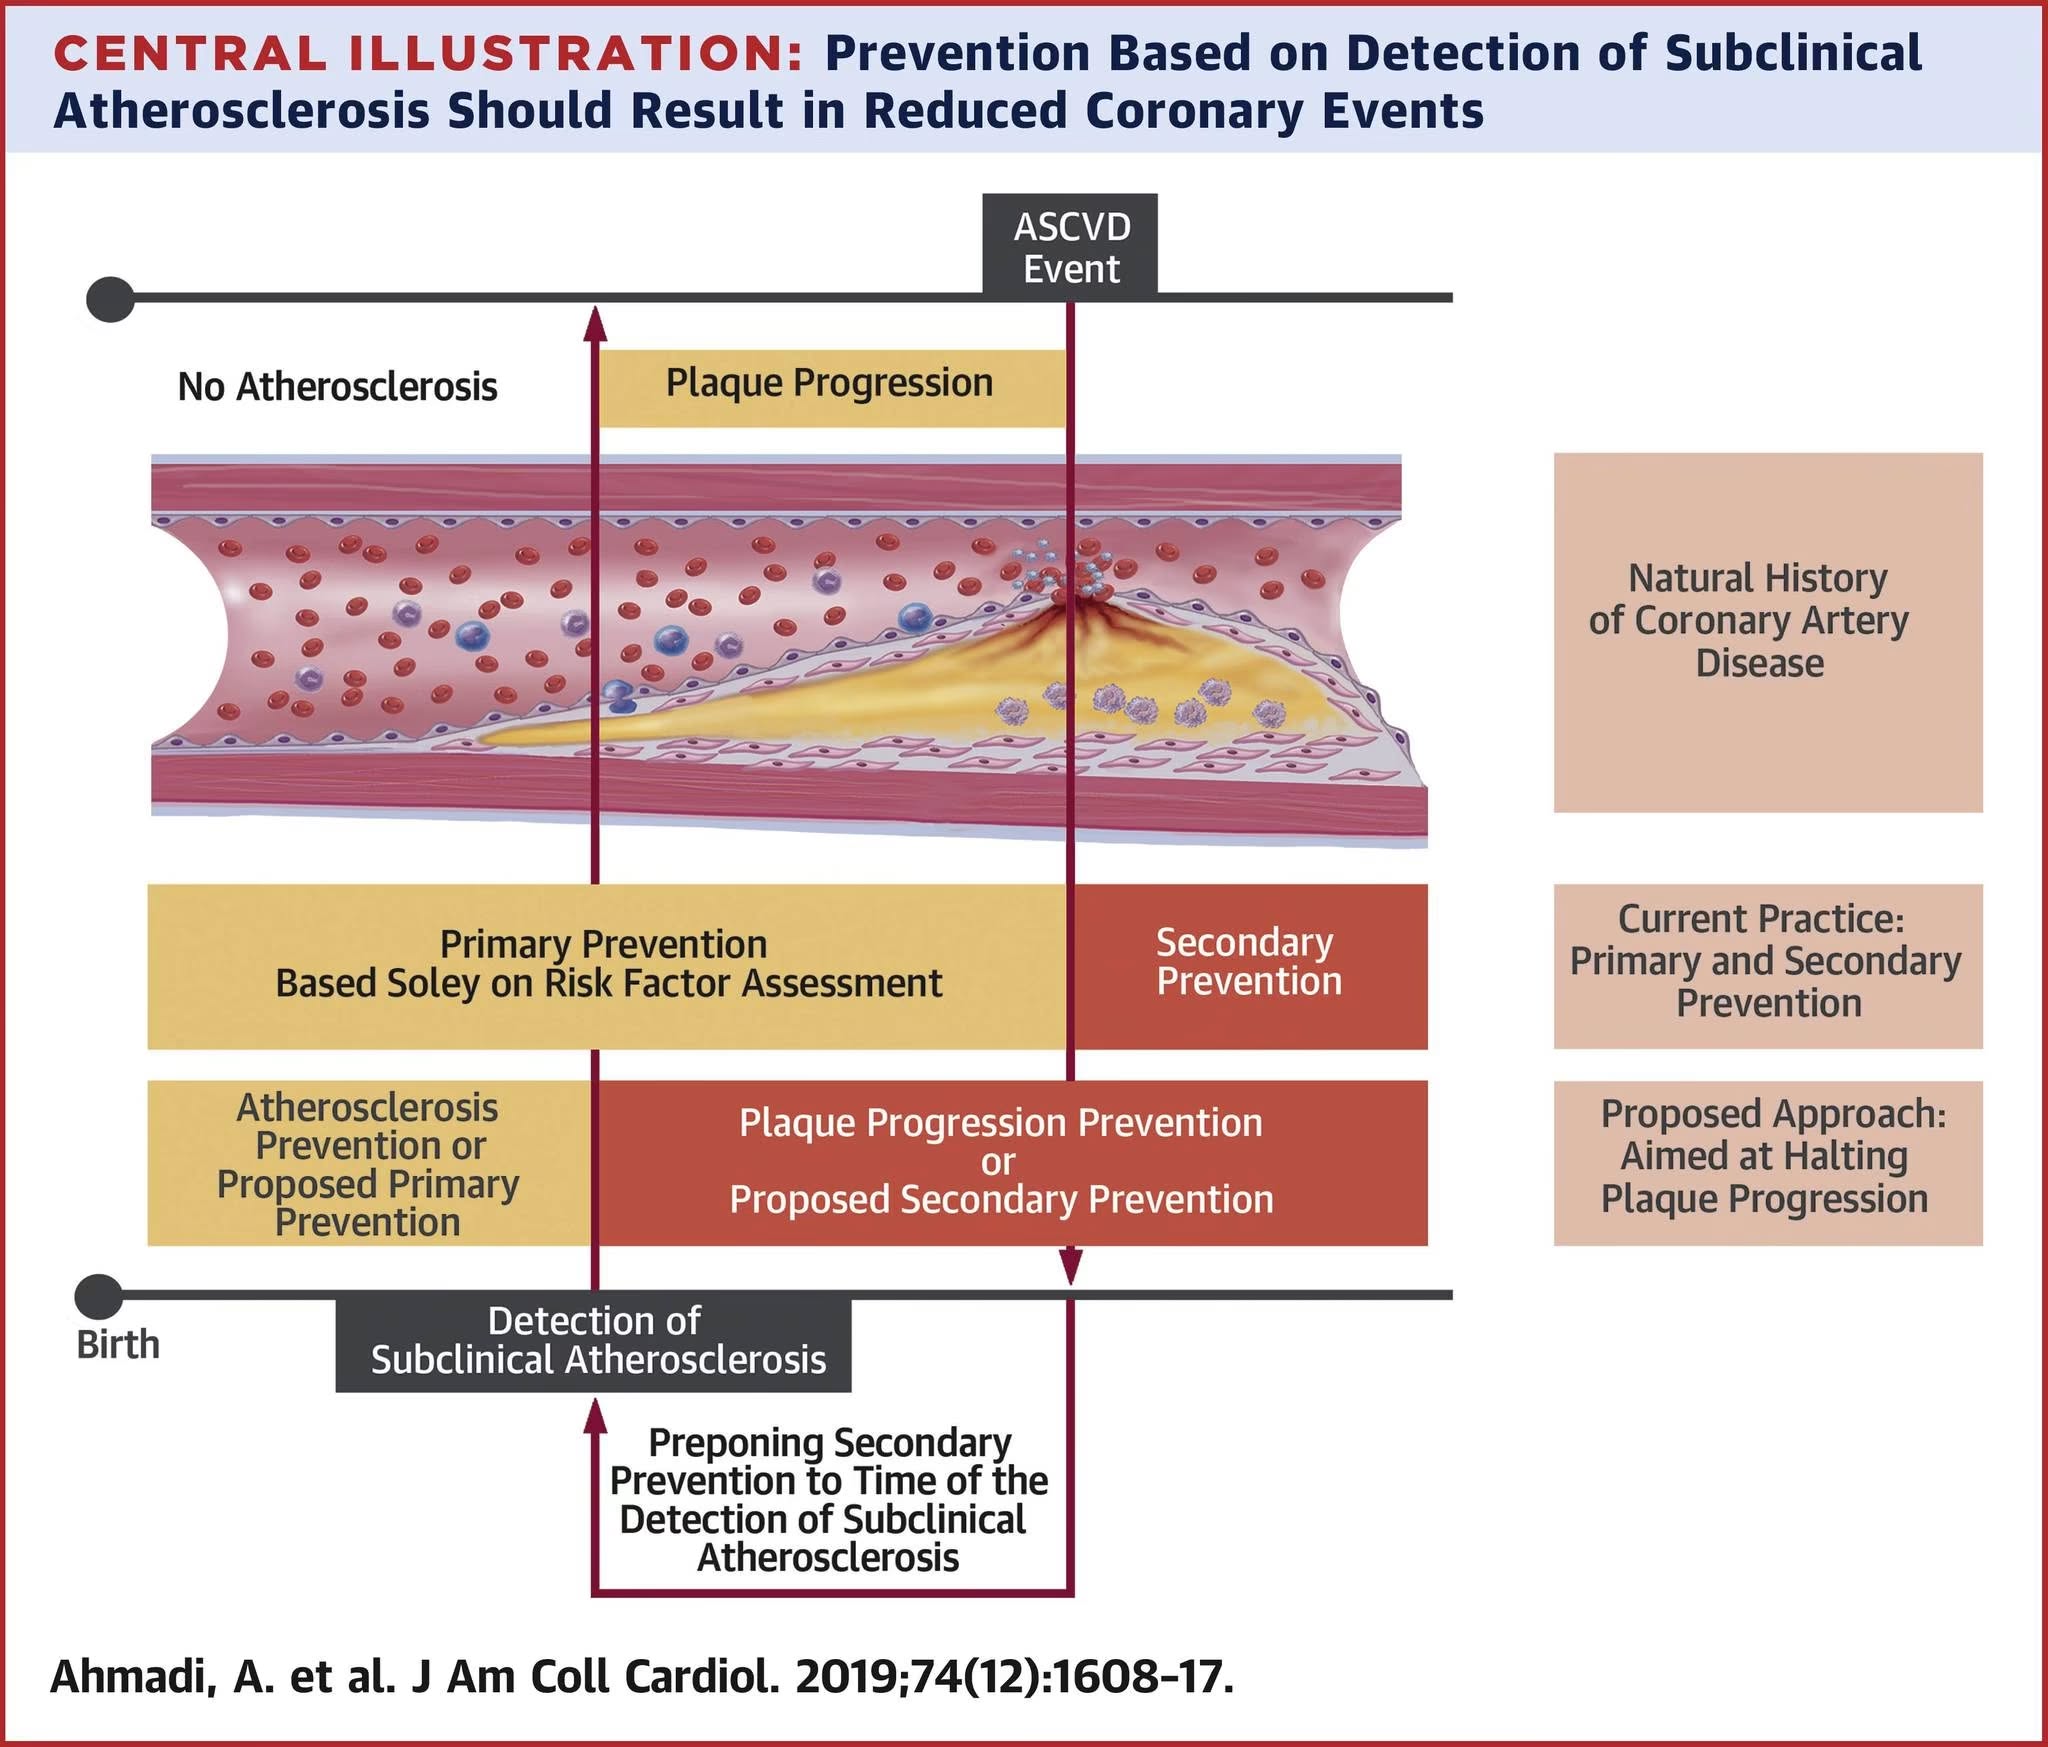
Summarises a 2019 JACC review arguing plaque progression is a necessary, modifiable step between subclinical atherosclerosis and MI, and that preventive strategy should shift toward imaging and aggressively treating subclinical disease. It reports data from PROSPECT, PARADIGM, GLAGOV and PESA showing progression stops at LDL <70 mg/dL and regression needs lower.
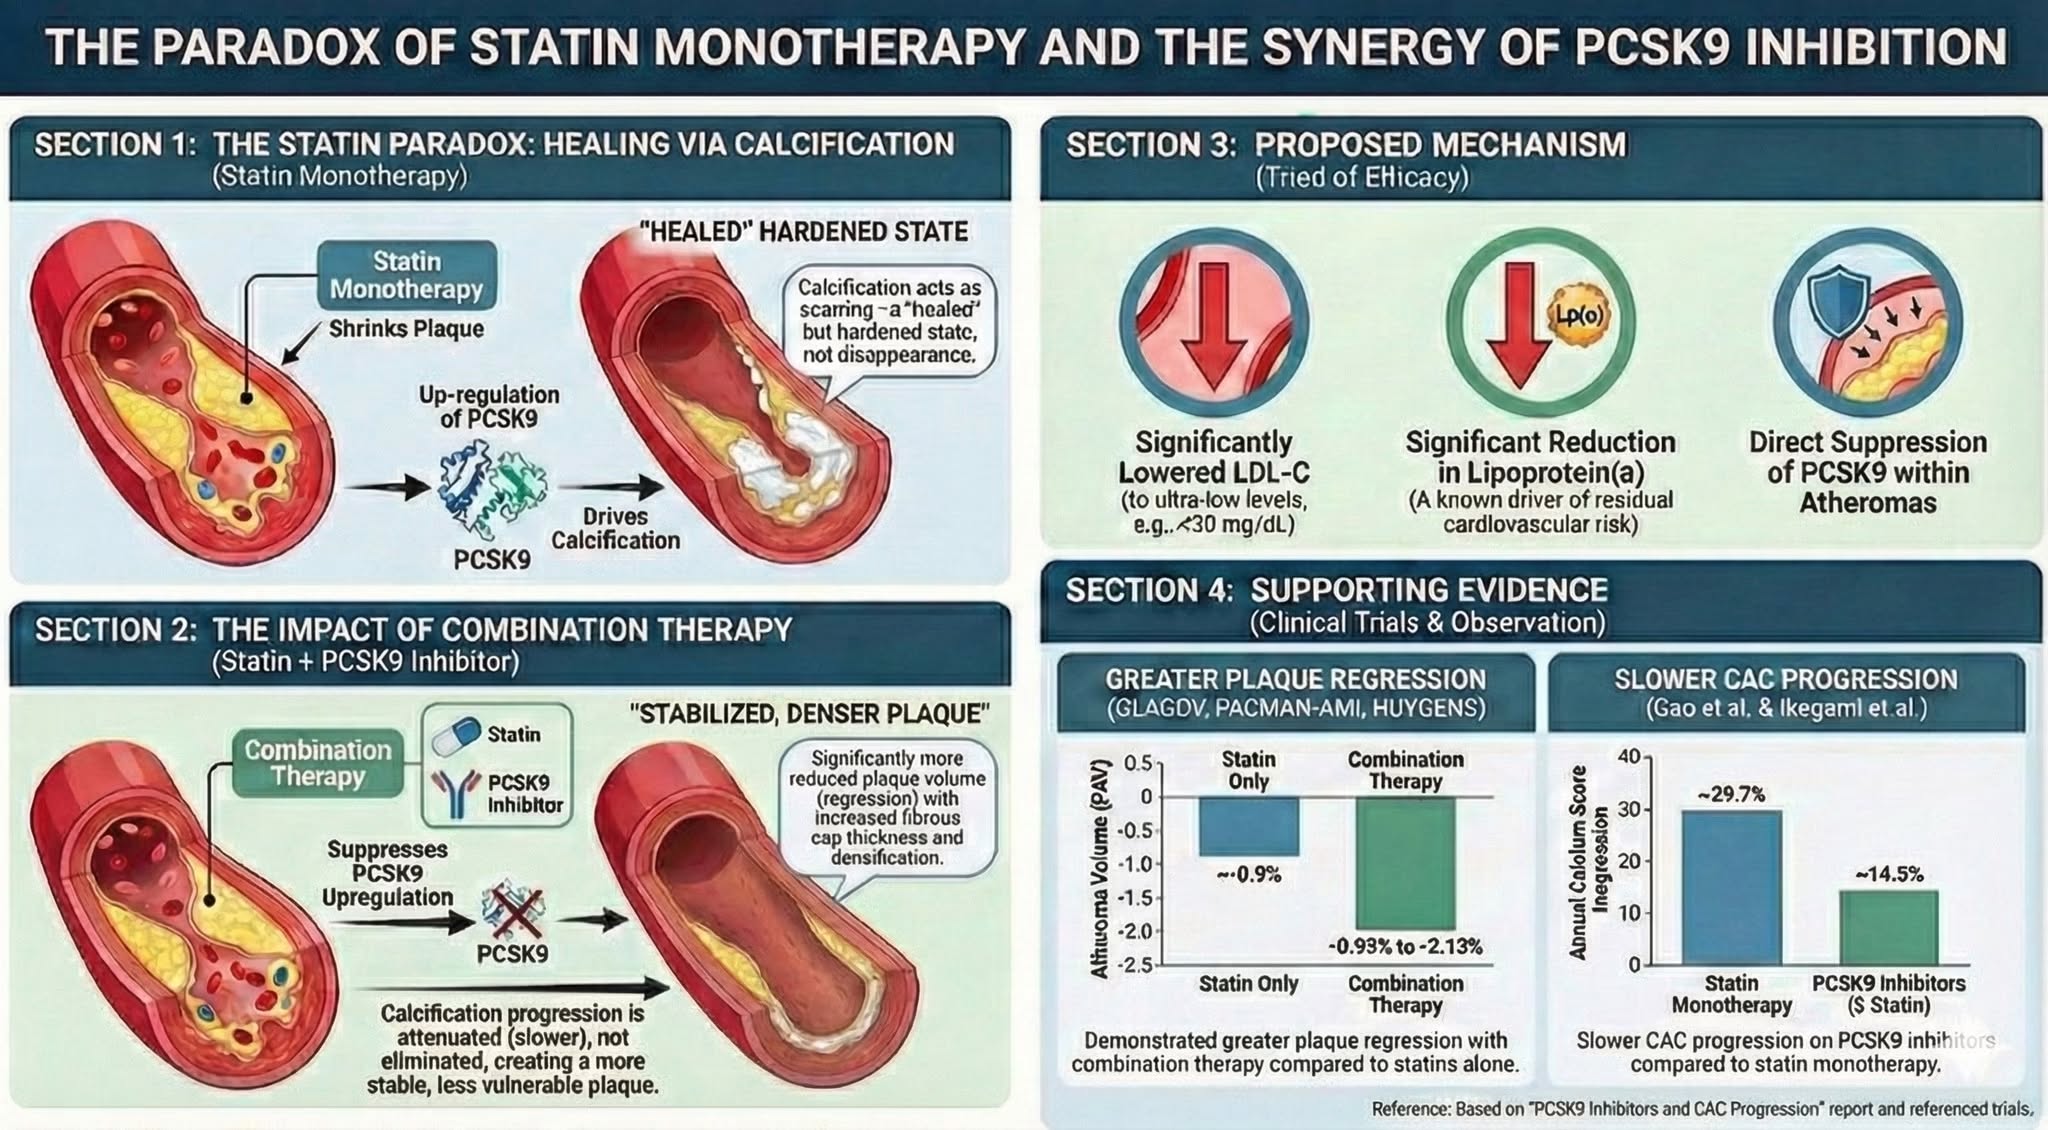
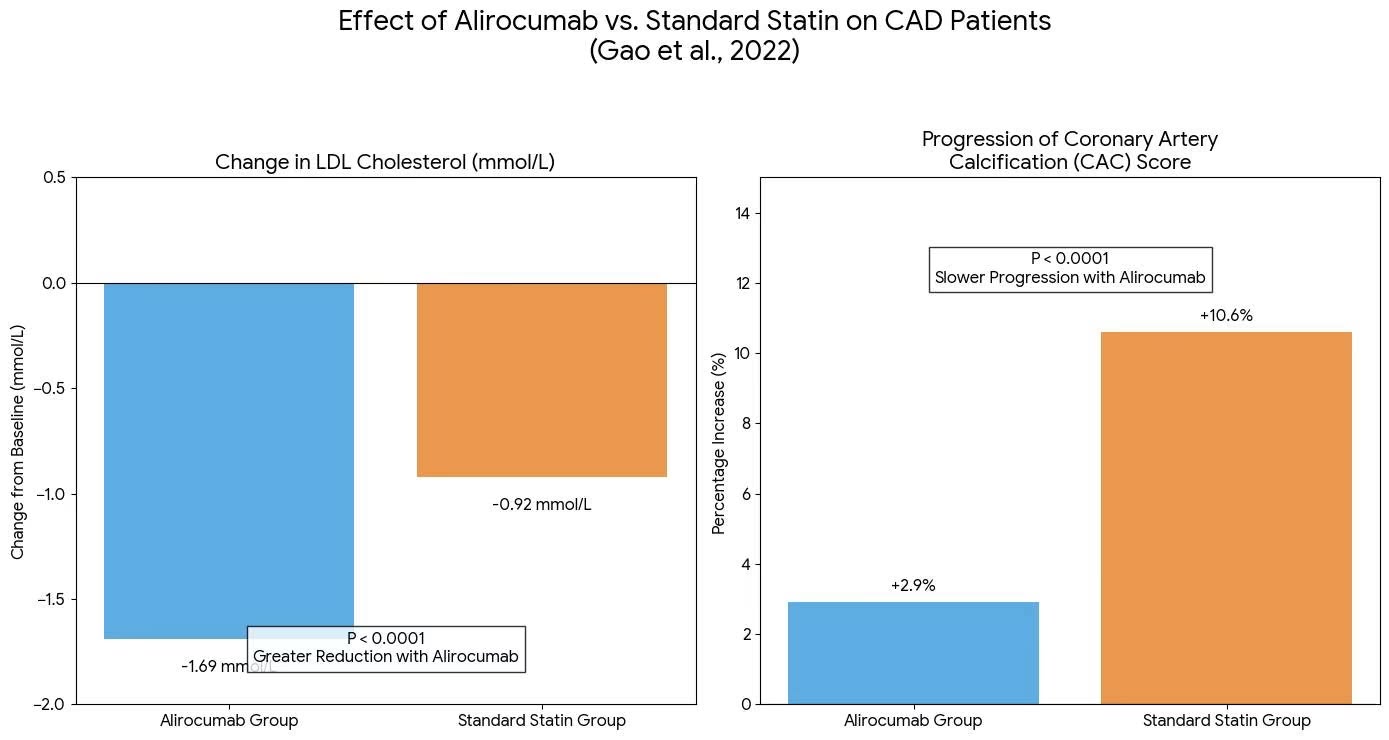
Explains the 'statin paradox' (statins reduce events and plaque but raise coronary calcium as plaque densifies) and argues PCSK9 inhibitors regress plaque without a calcific surge. Cites GLAGOV (evolocumab, LDL 36.6 mg/dL, PAV -0.95% vs +0.05%), PACMAN-AMI (alirocumab triple regression) and Gao 2022 (CAC +2.9% vs +10.6%).
Summarises a 2022 RCT in CAD patients on moderate statins: alirocumab 75 mg every 2 weeks for 18 months limited CAC progression, with Lp(a) change correlating with CAC change. A retrospective study (Ikegami) found about half the annual CAC progression with PCSK9 inhibitor plus statin; studies are small and larger trials are needed.
Explains that the Agatston score is not true calcium volume: it multiplies area by a stepwise density factor (1-4), so slightly denser plaque can jump a category and raise the score. Statins turn soft lipid-rich plaque into stable calcified plaque, so a rising CAC on treatment can reflect stabilization rather than failure.
Evidence review concluding statins reduce events and soft plaque but do not slow Agatston CAC progression, and that long-term cohorts show calcification accelerating without plateau, interpreted as plaque repair into stable scar. Trials: St. Francis (CAC unchanged, events down 33%), SALTIRE (progression 26% vs 18%) and BELLES (similar progression, ~11-14%).