Fact-checking things you will hear from influencers pushing keto/carnivore diets to prevent and treat heart disease
- It is true that LDL-P is a better marker of CVD risk than LDL-C.
ApoB is the best marker of all, and it includes LDL-P as a subset. So ApoB is the best test that you can get to measure lipids.
↪ LDL-C vs LDL-P vs ApoB: particle number predicts risk better than cholesterol content
- LDL-C usually tracks LDL-P and ApoB pretty well. So most people with high LDL-C will also have high LDL-P and ApoB. They usually go together. A significant discordance is uncommon, but can happen.
↪ Video: why ApoB is a better CVD risk marker than LDL-C and what discordance means
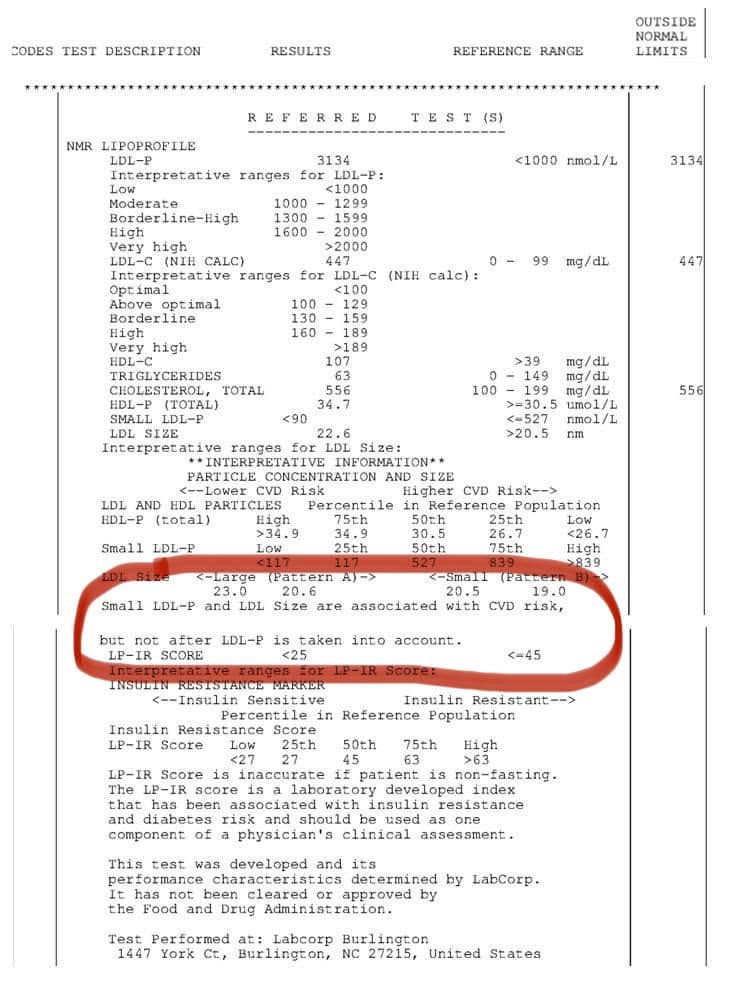
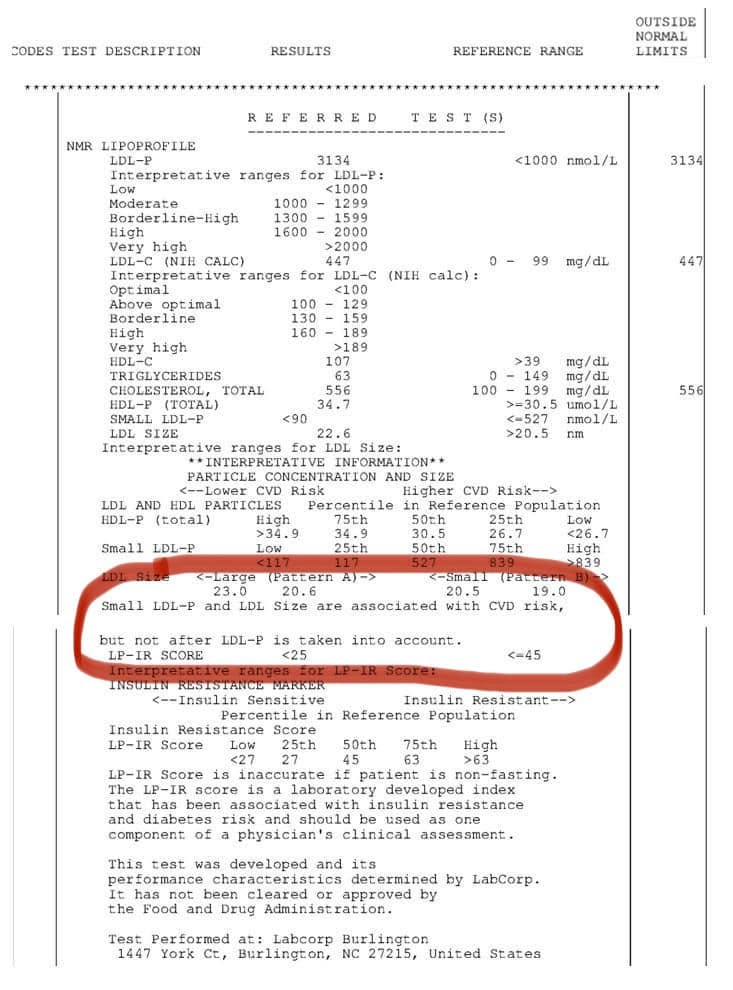
- Many studies have shown that particle size does not matter once you properly account for total number of particles. If your ApoB or LDL-P is high then having lots of large fluffy LDL particles and few small ones is not going to protect you. That is just plain wrong. All that matters is the total number of particles regardless of size (as measured by ApoB or LDL-P).
↪ LDL particle size does not predict CVD risk once particle number or ApoB is accounted for
- Most saturated fats strongly raise both LDL-P, ApoB, and LDL-C. (Not all, but most.)
- The studies that show that saturated fats as a whole do not raise risk of CVD used the standard American diet (or similar standard western diets) as the comparison. When you compare against healthier foods and diets, the vast majority of high quality studies show saturated fat raises risk for CVD.
(This is why standard guidance from the American Heart Association and similar organizations worldwide is to replace excess saturated fat with healthier sources of calories.)
↪ Saturated fat 'no harm' studies usually compare with the Western diet, not healthy foods
- Many studies show that HDL does not directly protect you against heart disease. It is just a crude proxy for insulin resistance and metabolic syndrome, which are both causal. So the focus should be on reversing the insulin resistance and the metabolic syndrome, not on raising HDL per se. If you do that, then HDL will automatically go up on its own.
↪ Low HDL matters mainly through insulin resistance; raising HDL itself failed in trials
↪ HDL and ApoA-I raising therapies repeatedly failed, so HDL is probably not directly causal
↪ Why insulin resistance lowers HDL, and why improving insulin sensitivity beats chasing HDL
↪ TG/HDL ratio tracks visceral fat; clearing liver and pancreas fat improves it
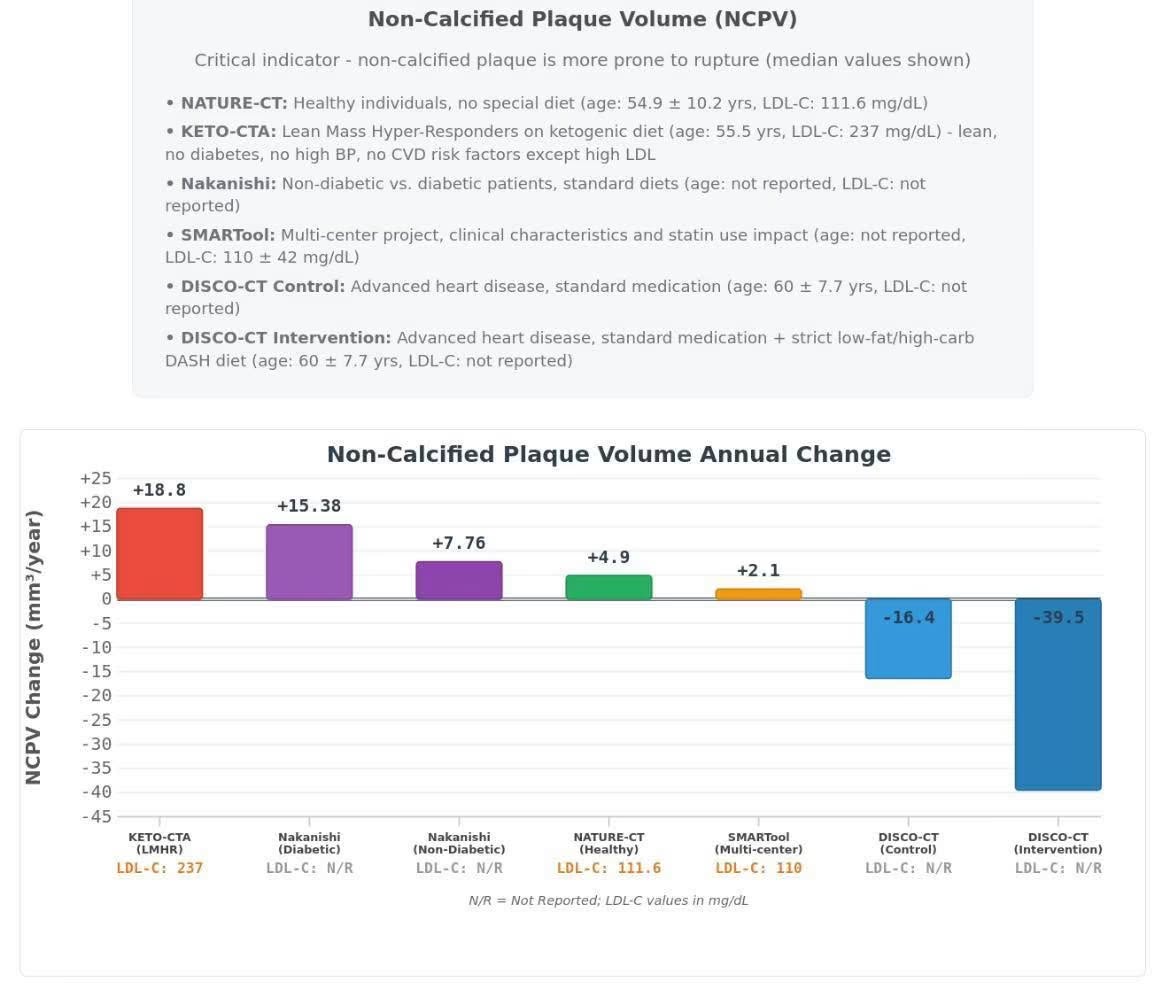
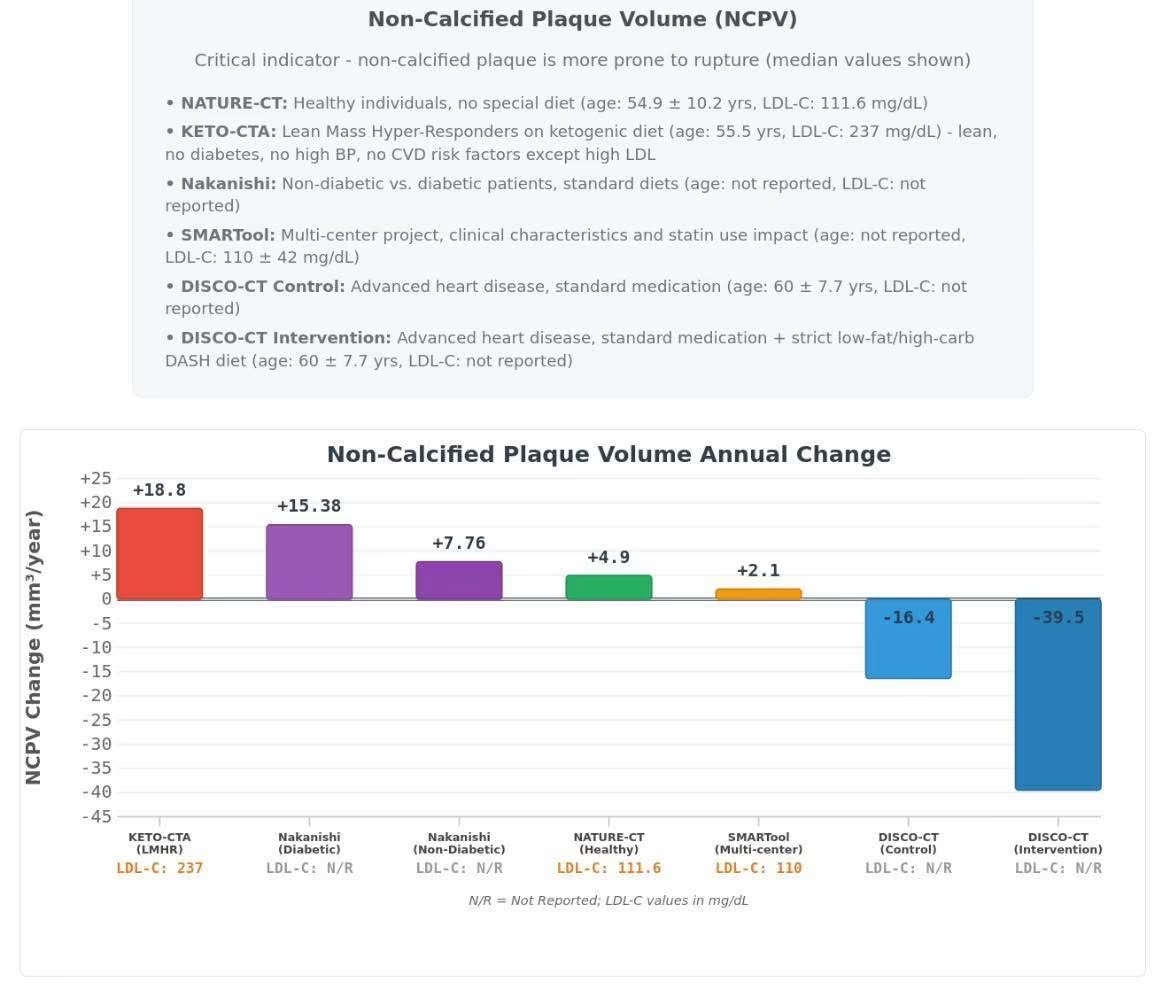
- It’s a lie that very high LDL is safe on a keto/carnivore diet, even if you are lean and metabolically healthy with low TG and high HDL. The Keto-CTA (LMHR) prospective cohort study directly tested this hypothesis, and it showed progression of soft plaque 3.8x faster than people eating the standard American diet with more normal LDL.
facebook.com/share/v/1Bk27CWaFE
↪ Keto-CTA extrapolation: LMHRs with CAC over 100 hit 'severe plaque' (PAV >15%) in ~3 years
————-
#ketoHD #carnivoreHD #apobHD #ldlpHD #ldlcHD #ldlHD #particlesizeHD #saturatedfatHD #hdlHD #tghdlratioHD #ketoctaHD #lmhrHD #ketoctasummaryHD