HD-OPM Archive
Hashtags

#lmhr

33 posts

Colchicine 0.5 mg cut plaque volume by over 1% in one year on CT angiography (Budoff)

May 11, 2025 · Louis Nervegna ♥ 20 · 💬 37 ↩ 9 Plaque, CAC & CT angiography

Louis highlights a Budoff-led CCTA trial in which low-dose colchicine reduced percent atheroma volume by over 1% in a year, with lower CRP and a slowing of calcified plaque. He contrasts this with the Keto-CTA study, where PAV rose 0.8% on a keto diet. Budoff notes it was a small study but supports colchicine in chronic stable coronary disease.

Keto-CTA (LMHR): very high LDL keto dieters with plaque kept progressing despite lean

Apr 07, 2025 · Louis Nervegna ♥ 14 · 💬 23 ↩ 1 Low-carb, keto & carnivore

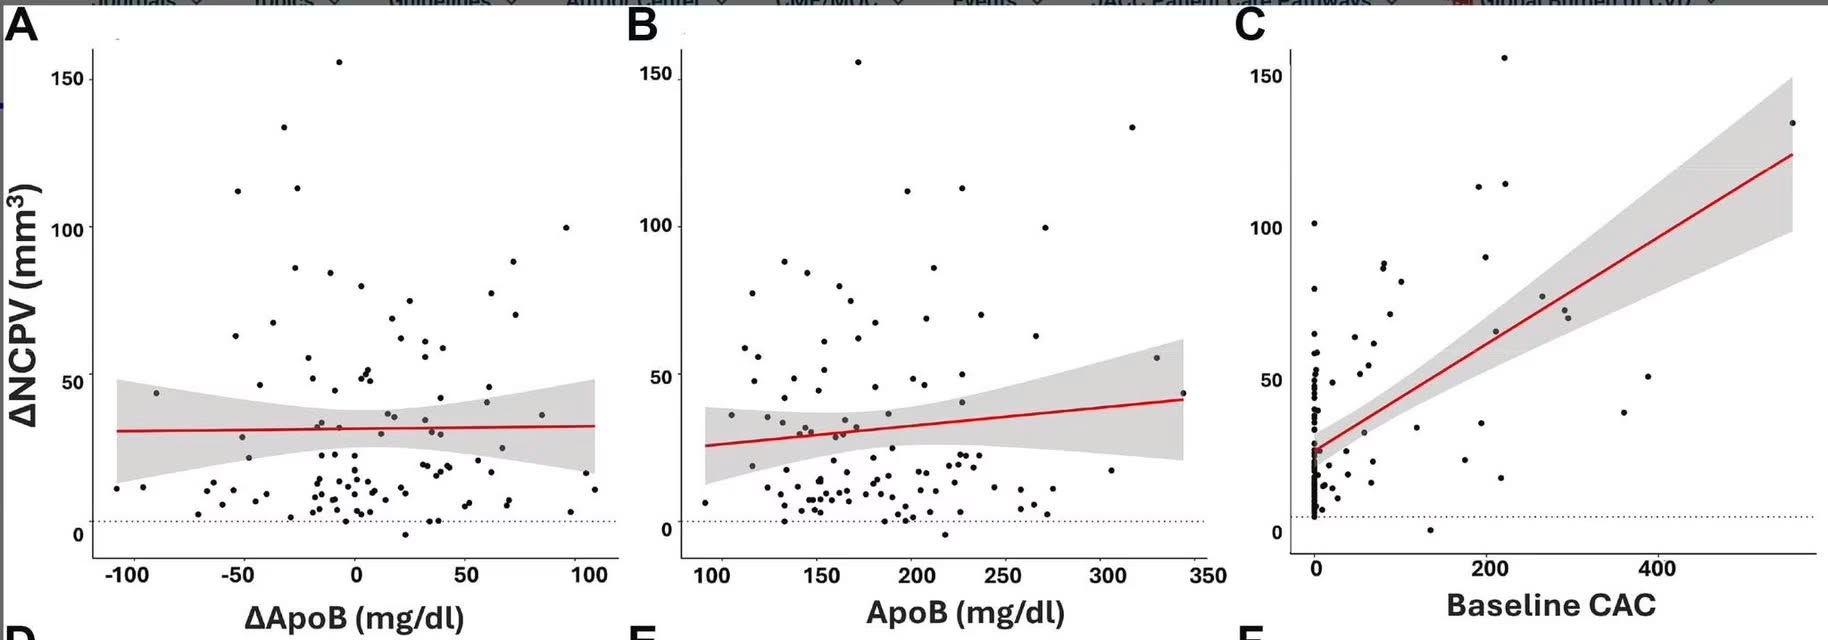
Louis summarizes the newly published one-year prospective Keto-CTA study of lean, metabolically healthy people on keto with very high LDL (mean 254 mg/dL). Those with baseline plaque progressed significantly at similar rates regardless of how high the LDL was, while those with zero plaque were unlikely to develop it within a year. There was no low-LDL comparison group.

Keto-CTA: LMHR group's 0.8% plaque volume rise exceeded that of typical Western cohorts

Apr 08, 2025 · Louis Nervegna ♥ 18 · 💬 14 Plaque, CAC & CT angiography

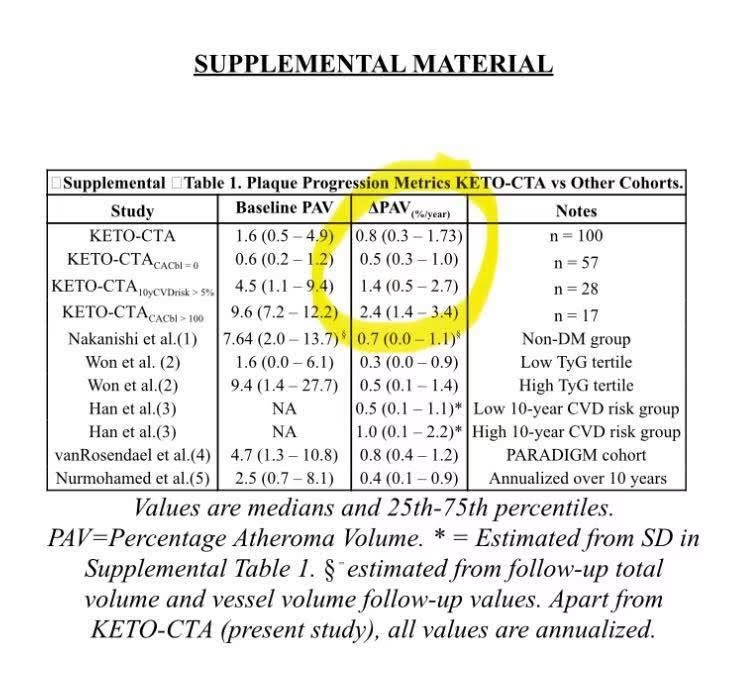
Louis expresses disappointment in the LMHR prospective cohort study, in which lean, metabolically healthy keto dieters with very high LDL had total plaque volume rise 0.8% in a year. He cites the paper's supplemental table, which he says shows other Western cohorts progressing less, and notes that no participant showed NCPV regression and that those with the most baseline plaque progressed the most.

Budoff recommends statins, aspirin and BP control for keto dieters with CT-detected plaque

Apr 14, 2025 · Louis Nervegna ♥ 14 · 💬 15 Low-carb, keto & carnivore

Louis cites a video in which Keto-CTA principal investigator Matthew Budoff recommends statins, low-dose aspirin and tight blood pressure control for patients on keto diets with significant plaque on CT angiography, and CT scans for his ketogenic patients. He says the statin is to treat plaque, since statins slow plaque progression even at low LDL.

Why the LMHR phenotype happens: starvation-like physiology in lean keto dieters

Jan 25, 2024 · Louis Nervegna ♥ 10 · 💬 11 ↩ 9 Low-carb, keto & carnivore

Louis proposes that the lean mass hyper-responder (LMHR) pattern, with extremely high LDL-C on keto/carnivore diets, reflects an ancient starvation response described in calorie-restriction literature. With near-zero body fat and no carbohydrate, the body acts as if starving, raising circulating LDL to deliver fat as fuel, lowering leptin, LDL receptors and thyroid and sex hormones. He links a trial showing fasting raised LDL and ApoB in healthy non-obese people, and cautions that overdoing restriction is the danger. This is a hypothesis, not proof of harm or safety.

Nicola Guess: Keto-CTA plaque rose ~20 mm3 in 1 year vs ~13 mm3 over 3 years in PARADIGM

Apr 12, 2025 · Louis Nervegna ♥ 7 · 💬 8 Plaque, CAC & CT angiography

Louis shares Dr. Nicola Guess's critique of the Keto-CTA study: the abstract omitted the registered primary outcome (non-calcified plaque volume), but the figure suggests a rise of ~20 mm3 in one year in lean keto dieters. In PARADIGM, high-risk people on Western diets rose ~13 mm3 over three years (about 17 mm3 with metabolic syndrome). With no control group, the comparison suggests accelerated soft plaque growth.

Co-author of LMHR study protocol says the design could not detect plaque progression

Dec 10, 2023 · Louis Nervegna ♥ 4 · 💬 17 Low-carb, keto & carnivore

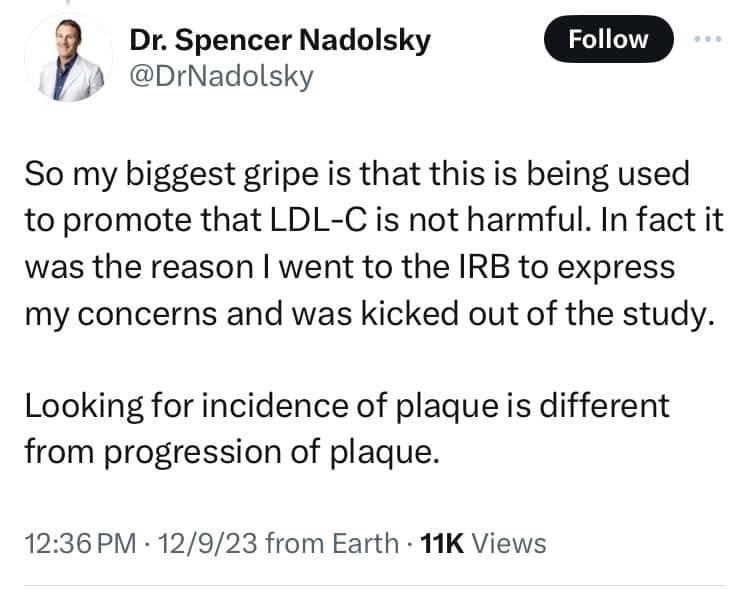
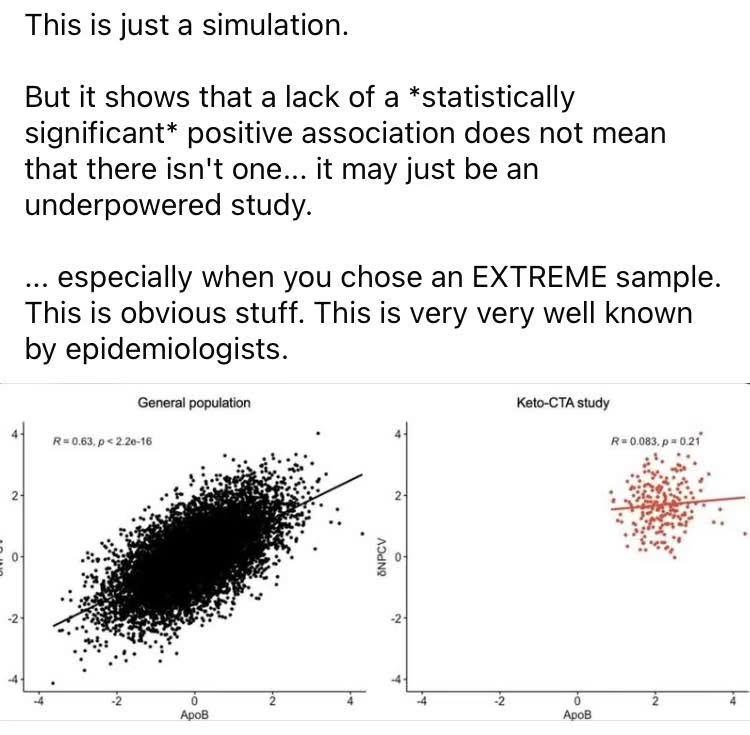
Louis paraphrases Dr. Spencer Nadolsky, who helped write the LMHR (keto hypercholesterolemia) study protocol, saying it enrolled only extremely healthy people with no diabetes, prediabetes, atherosclerosis, smoking, overweight or high hs-CRP and perfect blood pressure. Because soft plaque takes years to form even with very high LDL, little progression was likely after one year; enrolling people with existing atherosclerosis would have been more informative. The study's absence of progression should therefore not be read as proof of safety.

Keto-CTA (LMHR): plaque volume rose 25-100% in one year across CAC and risk subgroups

Apr 09, 2025 · Louis Nervegna ♥ 10 · 💬 6 ↩ 2 Plaque, CAC & CT angiography

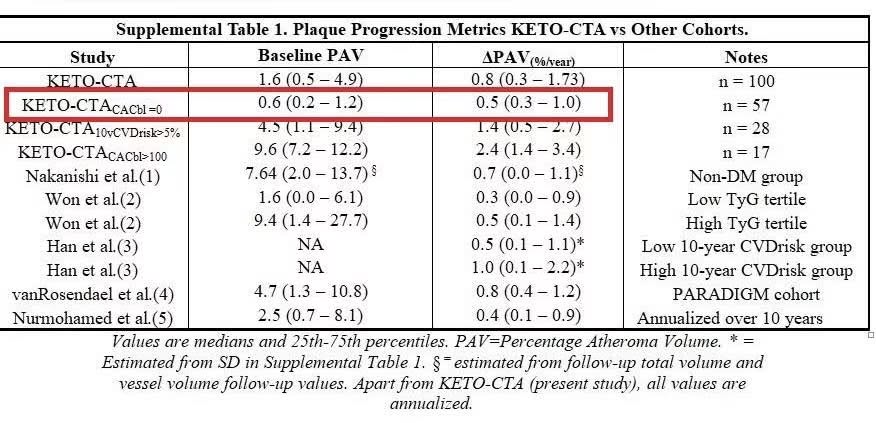
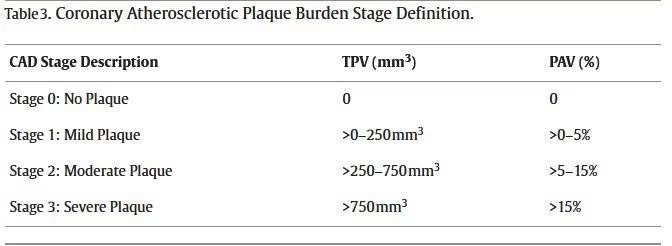
Louis walks through a table from the Keto-CTA (LMHR) paper showing percent atheroma volume (PAV) changes after one year in lean, metabolically healthy people on keto with average LDL 254 mg/dL. Plaque progressed in every subgroup, with the largest relative increase among those who started with zero CAC. He also explains what PAV measures.

Why LMHR happens: starvation-like physiology in very lean people on keto raises LDL

Jul 23, 2024 · Louis Nervegna ♥ 14 · 💬 4 LDL, ApoB & lipid panel

Reposting his earlier explanation, Louis argues that the lean mass hyper-responder phenotype reflects an old starvation response: with near-zero body fat, no carbohydrate and constant ketosis, the body raises circulating LDL to deliver fat as fuel, while lowering thyroid function and sex hormones. He links to a paper showing fasting increases total cholesterol, LDL-C and apoB in healthy nonobese humans.

Nick Norwitz's eight statements on ApoB, keto, LMHR and the J-shaped curve

Jul 23, 2024 · Louis Nervegna ♥ 10 · 💬 5 ↩ 8 LDL, ApoB & lipid panel

The poster paraphrases the final hour of a Nick Norwitz interview: ApoB is causal and necessary for atherosclerosis but not alone sufficient; lowering it lowers risk; the J-shaped LDL mortality curve disappears after correcting for confounding and reverse causality. In LMHR, a distinct physiology may change absolute risk and the benefit of lowering ApoB is still unknown.

LMHR cross-sectional study critique: Miami Heart comparison group was sicker by design

Sep 01, 2024 · Louis Nervegna ♥ 8 · 💬 6 LDL, ApoB & lipid panel

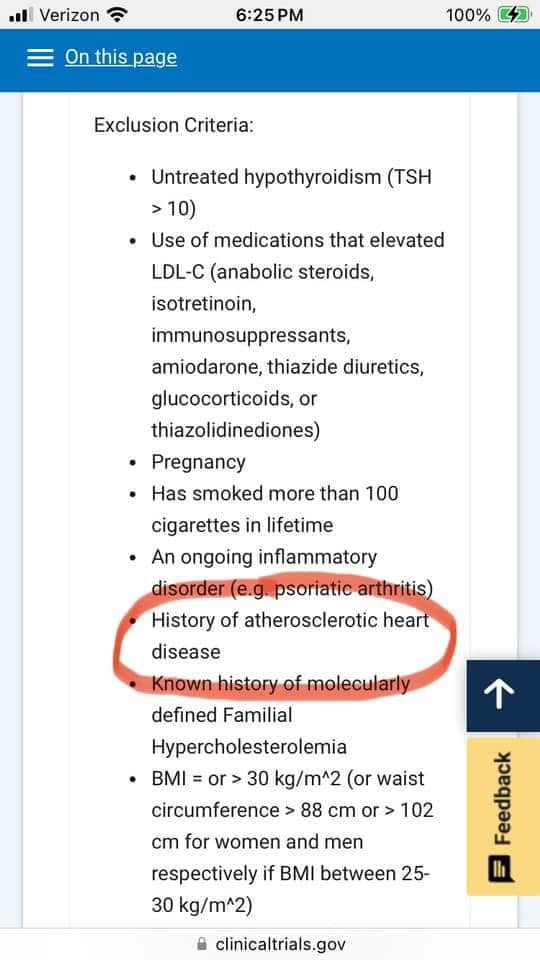
Louis compared official trial-registry exclusion criteria for the LMHR cross-sectional CT-angiogram study and the Miami Heart Study comparison cohort. LMHR excluded anyone with any atherosclerotic history, smokers, obesity, inflammatory disorders and familial hypercholesterolemia, whereas Miami excluded only advanced cases. He argues this creates selection bias because a healthy group cannot be matched to an unhealthy one.

Keto-CTA plaque progression vs plaque regression on Repatha in Budoff's other study

Apr 09, 2025 · Louis Nervegna ♥ 8 · 💬 2 Plaque, CAC & CT angiography

Louis compares non-calcified plaque volume (NCPV) changes in the Keto-CTA (LMHR) study with a second Matthew Budoff study in higher-risk people whose LDL was lowered to about 30 mg/dL with the PCSK9 inhibitor Repatha. The lean, healthy keto group with LDL 254 mg/dL progressed, while the hypertensive, higher-risk Repatha group mostly showed major regression. He also notes that uL and mm^3 are the same unit when comparing NCPV across studies.

Keto-CTA hyper-responders progressed soft plaque 3.8x faster than Nature-CT controls

Apr 18, 2025 · Louis Nervegna ♥ 5 · 💬 1 Plaque, CAC & CT angiography

Louis compares Keto-CTA (keto diet, LMHR) with the Nature-CT study, both from Budoff's UCLA group using CCTA and Cleerly software, with similar age (~55), no diabetes and no statins. After one year non-calcified plaque volume rose 18.8 mm3 in LMHR versus 4.9 mm3 in the Nature-CT standard-diet group. Budoff reportedly agrees it is a good comparison and plans a paper comparing them.

Letter to JACC: Keto-CTA omitted pre-specified outcome, a 43% rise in non-calcified plaque

Apr 21, 2025 · Louis Nervegna ♥ 4 · 💬 1 Plaque, CAC & CT angiography

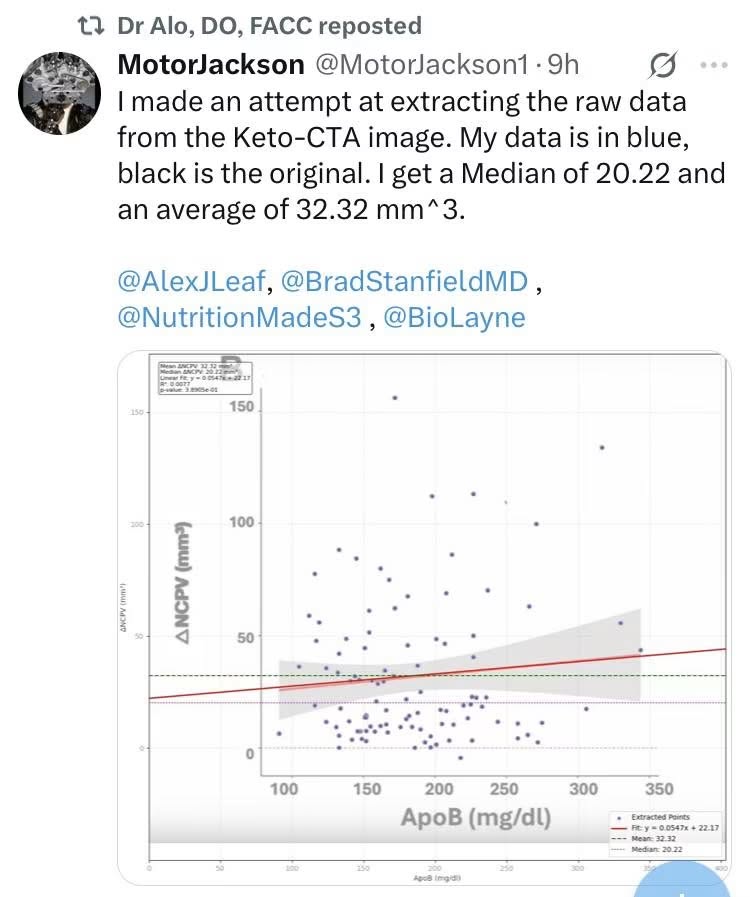
Louis shares a letter to the editor critiquing the Keto-CTA study of lean mass hyper-responders. It argues the primary outcome (non-calcified plaque volume) was not reported in the paper, but the lead author later shared a median increase of 18.8 mm3 (~43%), several-fold above normal annual progression and in contrast to regression seen in DISCO-CT. The 0.8% rise in percent atheroma volume also exceeds typical annual change in PARADIGM.

Keto-CTA plaque growth matched diabetics' and far exceeded high-risk statin-treated groups

Apr 16, 2025 · Louis Nervegna ♥ 4 · 💬 1 Plaque, CAC & CT angiography

Louis quotes an analysis of the Keto-CTA trial putting its plaque progression in context: median non-calcified plaque rose 18.8 mm3 in one year, comparable to type 2 diabetics (~17.4 mm3/yr), about triple PARADIGM metabolically normal people, and nearly 3x SMARTool high-risk non-statin users (6.4 mm3/yr). PAV rose 0.8% overall and 2.4% in those with CAC over 100.

Keto-CTA omitted its primary plaque outcome: median NCPV rose 18.8 mm3, 2.5x forecast

Apr 13, 2025 · Louis Nervegna ♥ 6 Plaque, CAC & CT angiography

Louis quotes Alex Leaf's critique: the Keto-CTA paper barely mentioned non-calcified plaque volume (NCPV), the primary outcome, saying only 'most participants presented with stable NCPV'. The lead author later gave a median increase of 18.8 mm3, over 2.5x the 7 mm3 predicted, comparable to metabolic syndrome over 3 years or type 2 diabetes per year, and nearly 3x SMARTool high-risk non-statin users.

Keto-CTA vs DISCO-CT: plaque progression on keto in LMHR versus DASH diet plus statins

Oct 25, 2026 · Louis Nervegna ♥ 3 Low-carb, keto & carnivore

A comparison of the KETO-CTA and DISCO-CT trials. The original 2025 JACC Advances KETO-CTA paper in lean mass hyper-responders was retracted over concerns about the Cleerly plaque software. It reported non-calcified plaque progression of 18.8 mm3 in a year versus about 5 mm3 typical of unmedicated Western populations, and re-analysis with HeartFlow and QAngio gave different values.