Everything you need to know about triglycerides and TG/HDL
TG/HDL is the ratio of triglycerides divided by HDL.
TG/HDL mainly functions as an indirect marker of insulin sensitivity and metabolic health. It tends to track with visceral fat (particularly fat in the liver) which is the main cause of insulin resistance. Losing visceral fat is the most effective way to lower triglycerides and raise HDL:
↪ Simple metabolic health markers: waist-to-height ratio, adiponectin and TG/HDL ratio
↪ TG/HDL ratio tracks visceral fat; clearing liver and pancreas fat improves it
↪ Liver fat is the biggest driver of insulin resistance in most people, per a Harvard expert
↪ Stanford's Gardner: insulin resistance and visceral fat cause high triglycerides
↪ Liver fat as low as 1.85% is linked to insulin resistance (Yale)
↪ Green Mediterranean diet with walnuts cut liver fat about 39% in an 18-month RCT
The second most effective way to lower triglycerides and raise HDL is to stop eating refined starch, refined sugar, and white potatoes:
↪ Yale: type 2 diabetes can be reversed, according to Gerald Shulman
↪ Stanford's Gardner: insulin resistance and visceral fat cause high triglycerides
↪ Willett: refined starch and sugar (~40% of US calories) drive heart disease and diabetes
↪ Harvard: white potatoes act like refined starch, tied to weight gain and diabetes
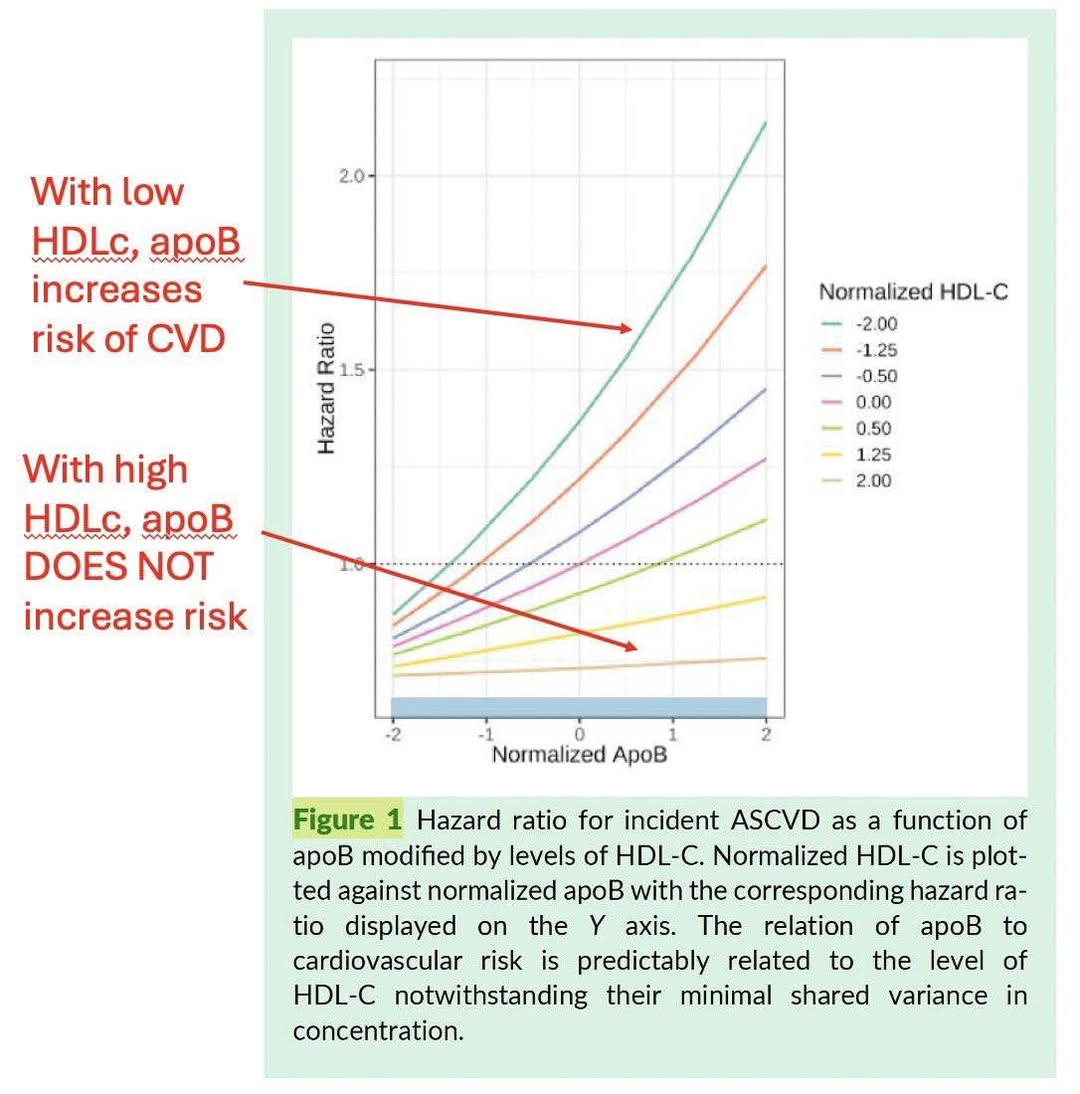
Insulin resistance is an independent risk factor from LDL. What this means is that both are important. They are both causal in heart disease. You ideally want to optimize both insulin sensitivity (as measured by TG/HDL) and LDL. This video discusses this further and goes through the studies showing that insulin resistance and LDL are independent risk factors:
↪ Interview: insulin resistance and LDL/ApoB are both independent causes of heart disease
In addition to being indirect markers for insulin resistance, high triglycerides are directly causal in CVD by themselves because they are carried by VLDL particles that are ApoB tagged. This ApoB tag makes VLDL directly atherogenic.
↪ VLDL cholesterol (triglycerides / 5) may be more atherogenic than LDL
However, it is important to point out that trials testing whether lowering triglycerides with drugs reduces risk for hard endpoints like heart attacks and strokes have been mostly disappointing, except when triglycerides were above 400 mg/dL to start.
Low HDL appears to be an indirect marker of insulin resistance, as opposed to a direct cause of CVD.
↪ Why insulin resistance lowers HDL, and why improving insulin sensitivity beats chasing HDL
The best way to raise HDL is to get rid of the underlying insulin resistance which is causing it to be low in the first place.
↪ Low HDL matters mainly through insulin resistance; raising HDL itself failed in trials
Many studies have shown that low HDL by itself is not directly causal in heart disease. Every single large trial testing an intervention to raise HDL by itself (without also improving insulin sensitivity) has failed to reduce heart attacks and strokes. So raising HDL without simultaneously improving insulin sensitivity is useless for preventing CVD. If you have low HDL (e.g. for genetic reasons) but good insulin sensitivity, then you likely have nothing to worry about.
↪ HDL and ApoA-I raising therapies repeatedly failed, so HDL is probably not directly causal
↪ CSL112 ApoA-I infusion failed in phase 3 AEGIS-II, supporting HDL as marker not cause
If you are specifically interested in TG/HDL in people with the LMHR phenotype and how it relates to high LDL, then these posts provide some explanation:
↪ Nick Norwitz's eight statements on ApoB, keto, LMHR and the J-shaped curve
↪ Why the LMHR phenotype happens: starvation-like physiology in lean keto dieters
↪ Interview: insulin resistance and LDL/ApoB are both independent causes of heart disease