Beyond Statins: The Shared Link Between LDL Reduction and Diabetes
This post was written in collaboration with Gemeni AI.
For decades, the small increase in new-onset type 2 diabetes observed during intensive lipid-lowering therapy was regarded primarily as an off-target side effect of statin pharmacology.
However, a growing body of evidence from human genetics, Mendelian randomization, and cross-class clinical trials indicates a more systemic biological phenomenon: The mechanism driving cardiovascular protection through the clearance of low-density lipoprotein (LDL) particles may be intrinsically coupled with subtle metabolic trade-offs in glucose homeostasis.
The Genetic Foundation: Target-Mediated Metabolic Effects
The paradigm shift away from a statin-centric model began with large-scale human genetic studies. Naturally occurring genetic variants that mimic the pharmacological inhibition of key targets in the cholesterol biosynthesis and clearance pathways display consistent, dosage-dependent associations with modestly elevated glycemic markers and modestly increased risk for type 2 diabetes.
- HMGCR Variations: Loss-of-function polymorphisms in the HMGCR gene (the molecular target of statins) mirror the therapeutic effect of statin therapy. These variants correlate directly with lower plasma LDL cholesterol alongside modestly elevated fasting glucose, slightly altered body composition/weight gain, and a modestly increased incidence of type 2 diabetes.
- NPC1L1 Inhibitors: Genetic proxies for Niemann-Pick C1-Like 1 (NPC1L1) inhibition—the pathway targeted by ezetimibe—demonstrate an equivalent glycemic penalty. Individuals carrying lifetime lower-expression variants display a proportional modest increase in diabetes risk per unit of LDL cholesterol lowered.
- PCSK9 Variants: Naturally occurring loss-of-function mutations in PCSK9, which lead to lifetime downregulation of circulating LDL via maximum cell-surface LDL receptor expression, similarly exhibit modestly higher fasting plasma glucose levels. This effect seems to be driven by hyper-expression of LDL receptors on pancreatic beta cells, causing cellular cholesterol overload and blunted insulin secretion.
- The Inverted FH Model: Conversely, patients with heterozygous Familial Hypercholesterolemia (FH)—whose genetic mutations impair LDL receptor function and elevate circulating LDL—present with a modestly lower prevalence of type 2 diabetes compared to non-affected relatives.
This natural biological model confirms that impaired clearance of LDL particles may modestly protect against diabetes development, while efficient cellular clearance may modestly predispose to it.
Comparative Pharmacotherapy and Clinical Manifestations
Comparing clinical trial outcomes across distinct pharmaceutical classes reveals how these genetic signals manifest in therapeutic practice:
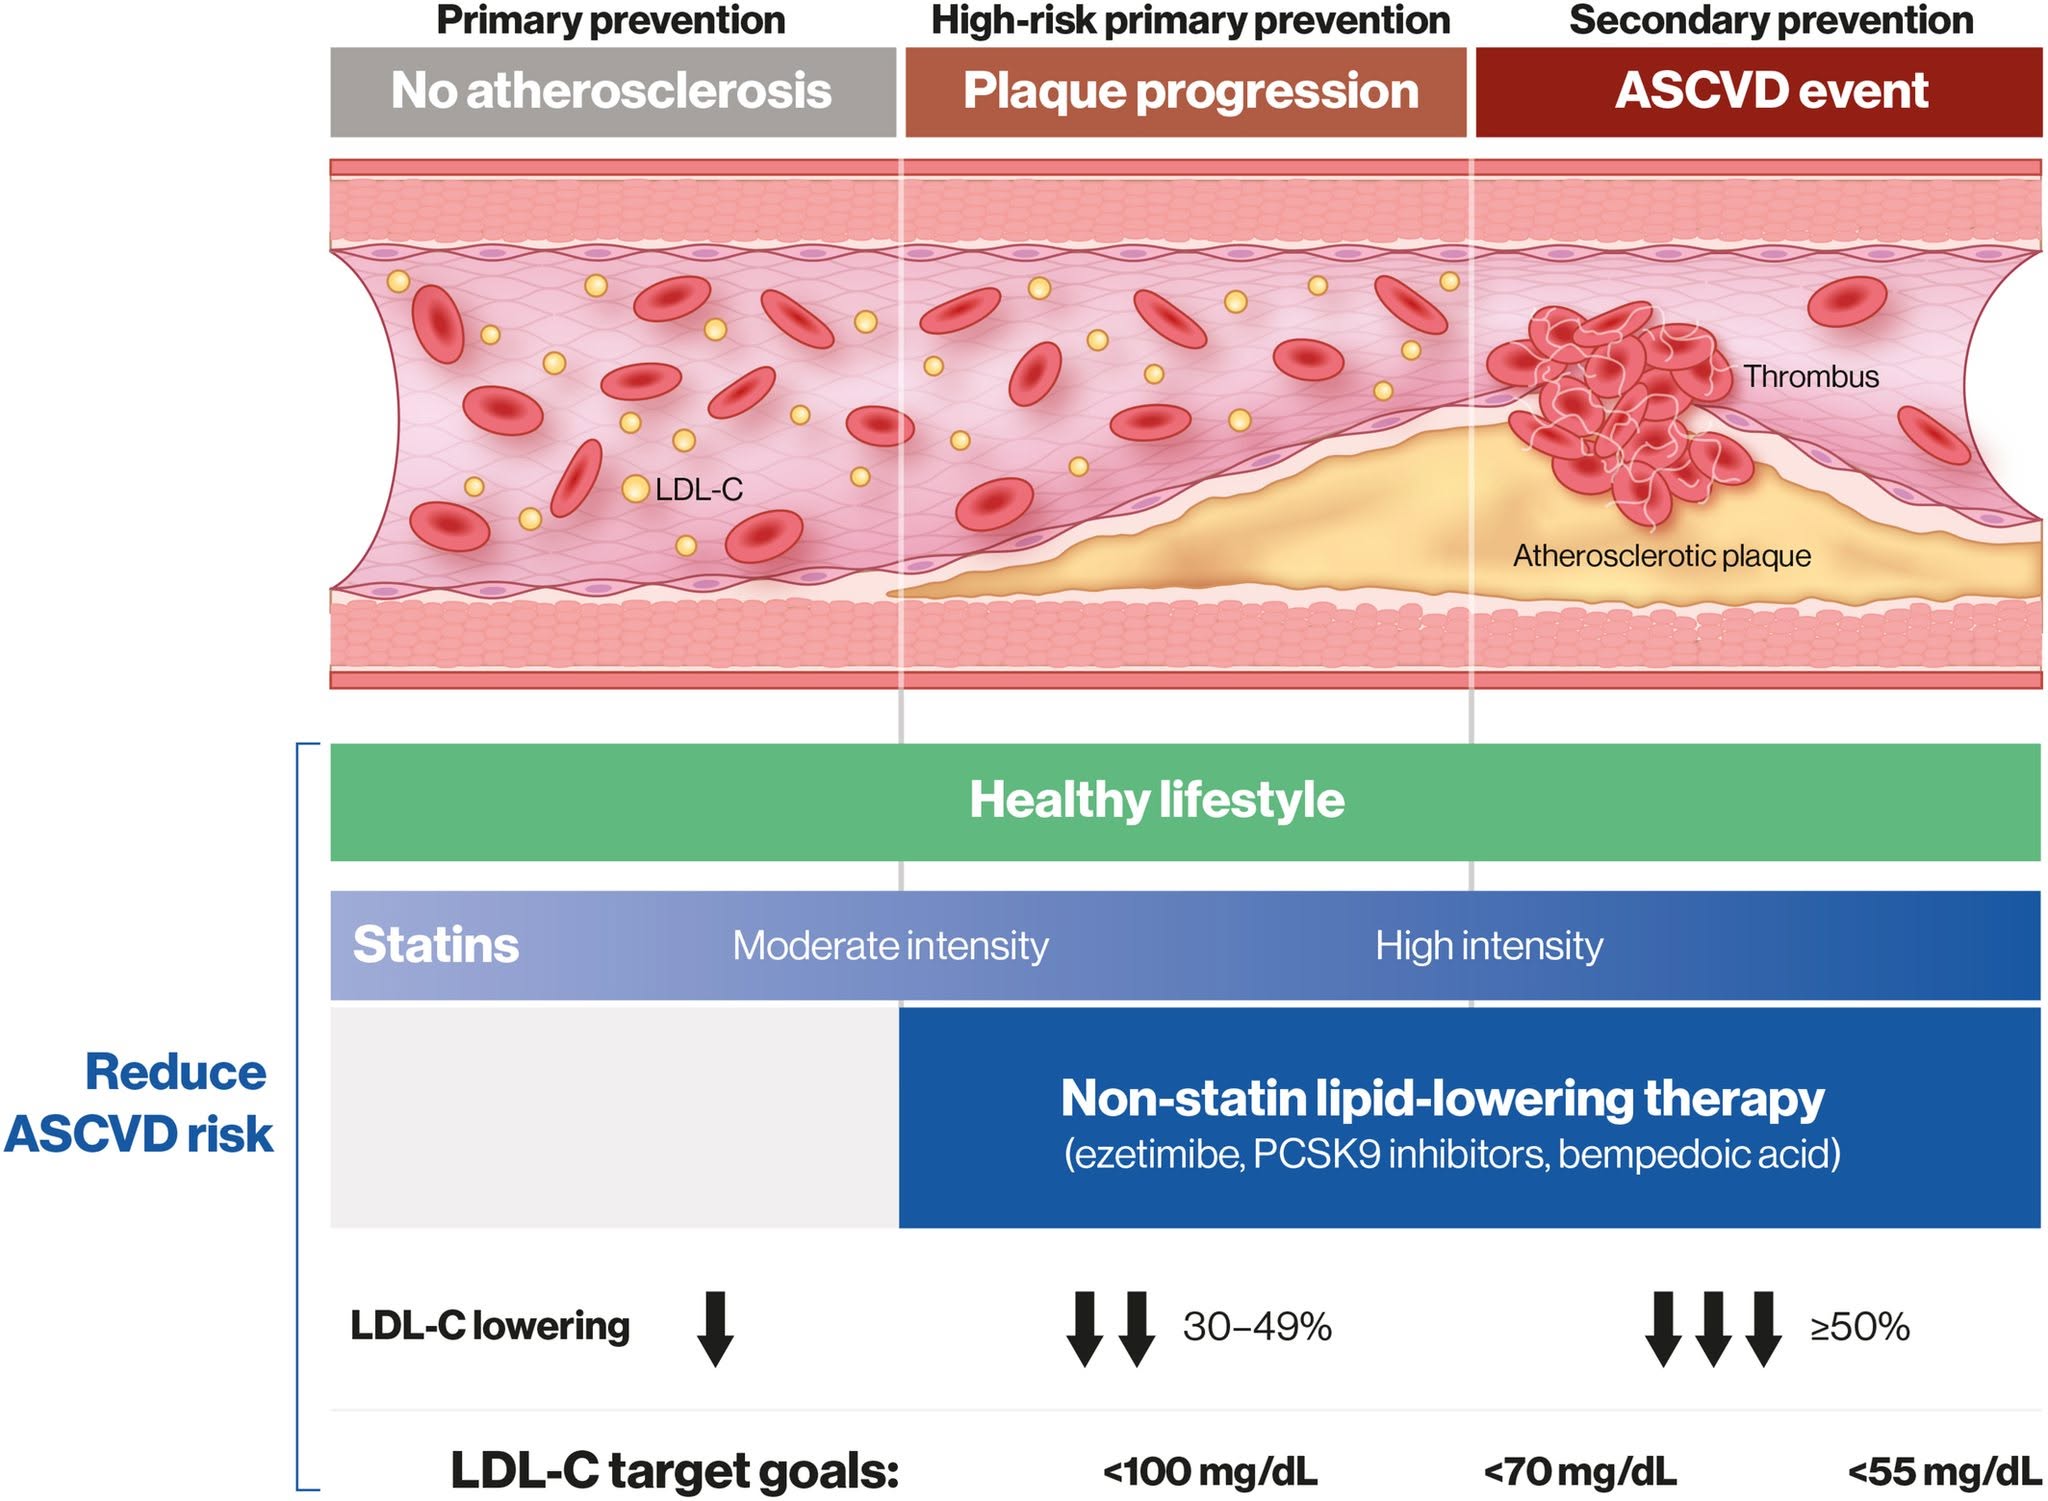
- Statins (HMG-CoA Reductase): Inhibits hepatic cholesterol synthesis and upregulates the LDL receptor (LDLR). Shows a dose-dependent increase in incident diabetes (~9–12% relative risk increase in high-intensity trials), concentrated primarily in individuals with preexisting metabolic risk factors.
- Ezetimibe (NPC1L1): Blocks intestinal cholesterol absorption and upregulates hepatic LDLR. Monotherapy yields neutral-to-slight negative glycemic shifts in trials lasting a few years, though genetic Mendelian randomization studies confirm a shared long-term risk signal with HMGCR.
- PCSK9 Inhibitors (PCSK9 Protein): Prevents LDLR degradation, maximizing cell-surface LDLR expression. Short-to-medium-term clinical trials (2–3 years) remain largely neutral for glycemic outcomes, though long-term genetic models demonstrate an elevated type 2 diabetes signal. However, this long term effect is considerably weaker than that seen with HMGCR variants
- Bempedoic Acid (ATP Citrate Lyase / ACLY): Suppresses hepatic cholesterol synthesis upstream of HMG-CoA. Serves as a notable exception to the trend, demonstrating reductions in new-onset diabetes and HbA1c.
While bempedoic acid lowers LDL through the same upstream pathway as statins, its clinical metabolic benefits in humans are driven by a dual mechanism. In addition to suppressing hepatic lipogenesis via ACLY inhibition, bempedoic acid functions as a direct activator of AMP-activated protein kinase (AMPK). This AMPK activation suppresses hepatic gluconeogenesis and improves insulin sensitivity, effectively counteracting the glycemic disruption typically seen with systemic LDLR upregulation.
Biological Mechanisms Underlying Glucose Dysregulation
While precise physiological pathways remain an active area of investigation, three primary mechanisms explain why increasing cellular uptake of LDL particles affects glucose handling:
- Pancreatic Beta-Cell Stress: Upregulation of cell-surface LDLR increases the uptake of cholesterol into pancreatic islet cells. Excessive intracellular cholesterol alters membrane properties, induces endoplasmic reticulum stress, and impairs insulin granule exocytosis, directly blunting glucose-stimulated insulin secretion without requiring overt cell death.
- Hepatic Metabolic Alterations: Because the liver accounts for roughly 70–80% of systemic LDLR expression and LDL clearance, heavy uptake of LDL primarily impacts hepatic tissue. Hypothesized pathways suggest that intracellular lipid accumulation may alter cell membrane fluidity and lipid raft dynamics, subtly interfering with downstream insulin receptor signaling and altering hepatic glucose output.
- Peripheral Insulin Resistance & Adipose Flux: Altering systemic LDL availability changes the flux of circulating lipids to peripheral tissues. This shift modifies systemic lipid partitioning and adipose tissue storage, subtly exacerbating peripheral insulin resistance in skeletal muscle and adipose beds.
Synthesis and Clinical Reality
The connection between reduced LDL cholesterol and modestly increased diabetes risk may represent an underlying biological trade-off rather than a drug-specific flaw. The primary mechanism for clearing LDL from the blood—increasing cell-surface LDL receptor expression—leads to subtle disruptions in intracellular cholesterol balance and glucose regulation, particularly within pancreatic islet cells.
Crucially, this metabolic trade-off does not undermine the clinical utility of LDL-lowering therapies. Across all major outcome trials, the absolute reduction in major adverse cardiovascular events (such as myocardial infarction, stroke, and vascular mortality) vastly outweighs the absolute risk associated with the modest rise in new-onset diabetes or fasting blood glucose.
#statinsdiabetesHD #ldldiabetesHD #ezetimibeHD #pcsk9HD #statinsHD #bempedoicacidHD #diabetesHD